Related Experiment Video
Updated: Jun 2, 2026
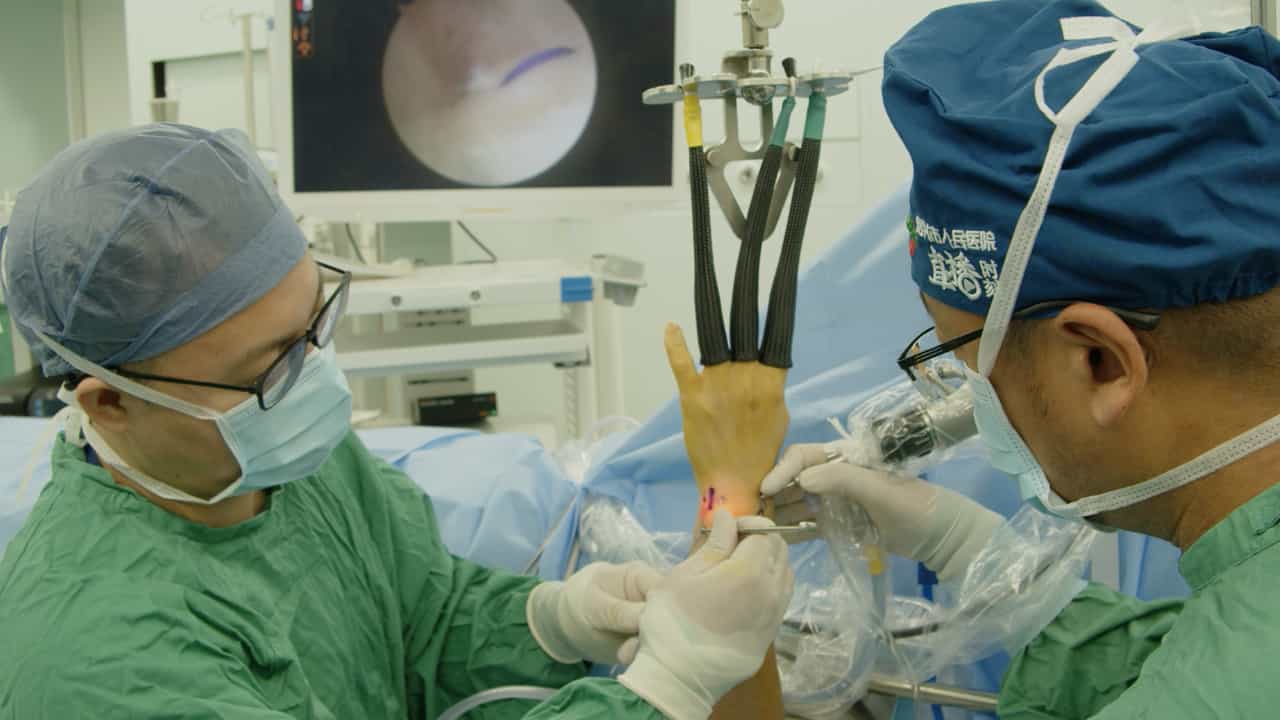

Novel Triple-Loop Technique for Suturing TFCC Injuries without Transosseous Tunnel
Published on: May 23, 2025
Short-term outcomes following reconstruction or direct repair of the ulnar collateral ligament
Sashrik Sribhashyam1, Grayson M Talaski2, Shahabeddin Yazdanpanah3
1Virginia Commonwealth University School of Medicine, Richmond, VA 23298, USA.

Introduction:
Medial ulnar collateral ligament (UCL) injuries substantially impair athletic performance due to pain, instability, and diminished throwing capabilities. While UCL reconstruction is the primary surgical treatment due to its reliable restoration of stability and high return-to-play rates, direct UCL repair has re-emerged as an alternative in select cases. For the purposes of this study, both procedures are collectively referred to as UCL reconstruction/repair (ULCR). The long rehabilitation period and complications such as ulnar neuropathy and stiffness remain concerns. Existing literature emphasizes long-term outcomes, leaving a large gap concerning short-term complication rates. To address this gap, the present study evaluates the predictive variables associated with adult UCLR 30-day postoperative complications, potentially refining surgical planning and improving patient outcomes.
Methods:
The American College of Surgeons National Surgical Quality Improvement Program was queried for Current Procedural Terminology (CPT) codes 24345 and 24346, excluding codes related to ulnar nerve neurolysis or transposition (CPT 64718). The primary outcome was any adverse event (AAE) within 30 days. Secondary outcomes were specific medical and surgical complications. Descriptive analysis for both 24345 and 24346 alone were included. Multivariable logistic regression examined the independent effect of select comorbidities, age, body mass index (BMI), operative time, and length of stay (LOS) on AAE. An operative time threshold analysis was also performed to look for inflection points that increased risk.
Results:
A total of 464 adult UCLR patients met the inclusion criteria with a median age of 33 years [21-56] and a median BMI of 26.6 kg/m2 [24.2-31.6]. Thirty-day complications were low, with an AAE rate of 2.4%, a surgical site infection rate of 1.1%, a return to the operating room rate of 0.9%, and a mortality rate of 0.2%. Extended LOS occurred in 8.4% of patients but was not counted as a complication. No studied demographic-, comorbidity-, or surgery-related metrics were associated with higher risks of experiencing AAE. An operative time cut-off of 78.7 minutes did not reach statistical significance (p = 0.196).
Conclusion:
In a 2010-2023 National Surgical Quality Improvement Program (NSQIP) cohort of 464 UCLRs, 30-day morbidity remained very low, and multivariable analysis showed no independent predictors. These data reinforce prior registry work showing similarly low event rates, helping to confirm UCLR as a safe outpatient procedure. Future longitudinal studies are necessary to clarify whether this short-term low-risk profile translates into long-term durable and functional success.
Level Of Evidence:
Level III.