Related Experiment Video
Updated: Jun 2, 2026


Dual-Dye Optical Mapping of Hearts from RyR2R2474S Knock-In Mice of Catecholaminergic Polymorphic Ventricular Tachycardia
Published on: December 22, 2023
Severe Arrhythmia Complicating Takotsubo Cardiomyopathy Revealing an Underlying Pheochromocytoma: A Case Report
Meryem Tabat1, Zineb El Jaouhari1, Abdnacer Drighil2
1Cardiology, Centre Hospitalier Universitaire (CHU) Ibn Rochd, Casablanca, MAR.

Abstract:
Pheochromocytoma is a rare catecholamine-secreting tumor that can cause major cardiovascular complications, including acute heart failure, arrhythmias, and stress-induced cardiomyopathy. Takotsubo syndrome (TTS) is an acute non-ischemic cardiomyopathy characterized by transient left ventricular systolic dysfunction without obstructive coronary artery disease, often mimicking acute coronary syndrome. Catecholamine excess plays a central role in its pathophysiology, leading to myocardial stunning, hemodynamic instability, and arrhythmias. The association between pheochromocytoma and TTS is uncommon and frequently associated with severe clinical presentations. We report the case of a 52-year-old woman with poorly controlled hypertension treated with a calcium channel blocker, who presented with chest pain, dyspnea, and palpitations. On admission, blood pressure was 178/122 mmHg, and heart rate was 102 bpm. The patient described recurrent episodes of headache and palpitations occurring two to three times monthly and lasting 30 to 60 minutes, suggesting secondary hypertension. Electrocardiography showed 1 mm ST-segment elevation in the anterior leads without reciprocal changes and a prolonged QTc interval (480 ms). Peak high-sensitivity troponin reached 1880 ng/L (reference <35 ng/L), while brain natriuretic peptide (BNP) was 450 pg/mL (reference <125 pg/mL). Transthoracic echocardiography revealed a left ventricular ejection fraction of 45% with apical akinesia and basal hyperkinesia, consistent with Takotsubo syndrome. Left ventriculography confirmed typical apical ballooning, and coronary angiography showed no obstructive coronary artery disease. During hospitalization, the patient developed rapid atrial fibrillation with hemodynamic instability, requiring electrical cardioversion and amiodarone therapy. Labile blood pressure and paroxysmal symptoms raised suspicion of catecholamine excess, subsequently confirmed by elevated plasma and urinary metanephrines. Abdominal CT identified a 30 × 25 × 28 mm left adrenal mass with attenuation >10 HU and intense heterogeneous contrast enhancement, highly suggestive of pheochromocytoma. Preoperative treatment with phenoxybenzamine was progressively titrated to achieve hemodynamic stabilization before surgical resection. After surgery, left ventricular systolic function completely recovered, with ejection fraction improving to 58%. At the sixth-week follow-up, plasma and urinary metanephrines had normalized, confirming complete biochemical remission and successful tumor removal. Blood pressure also normalized postoperatively. This case highlights the importance of considering pheochromocytoma in patients with Takotsubo syndrome complicated by severe arrhythmias or labile hypertension, as early diagnosis may improve management and prognosis.

Related Concept Videos
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:16
ECG Interpretation of Arrhythmias I: Sinus Arrhythmias
Types of Arrhythmias
Sinus Node Arrhythmias
Sinus Bradycardia: Originating from the sinoatrial (SA) node, sinus bradycardia involves slower impulses, resulting in a heart rate of less than 60 beats per minute (bpm). Causes include sleep, vagal stimulation, beta-blockers, hypothyroidism, and...
 01:17
Increased pulse rate
Many factors can elevate the risk of developing tachycardia. These include advanced age, a family history of arrhythmias, and an...
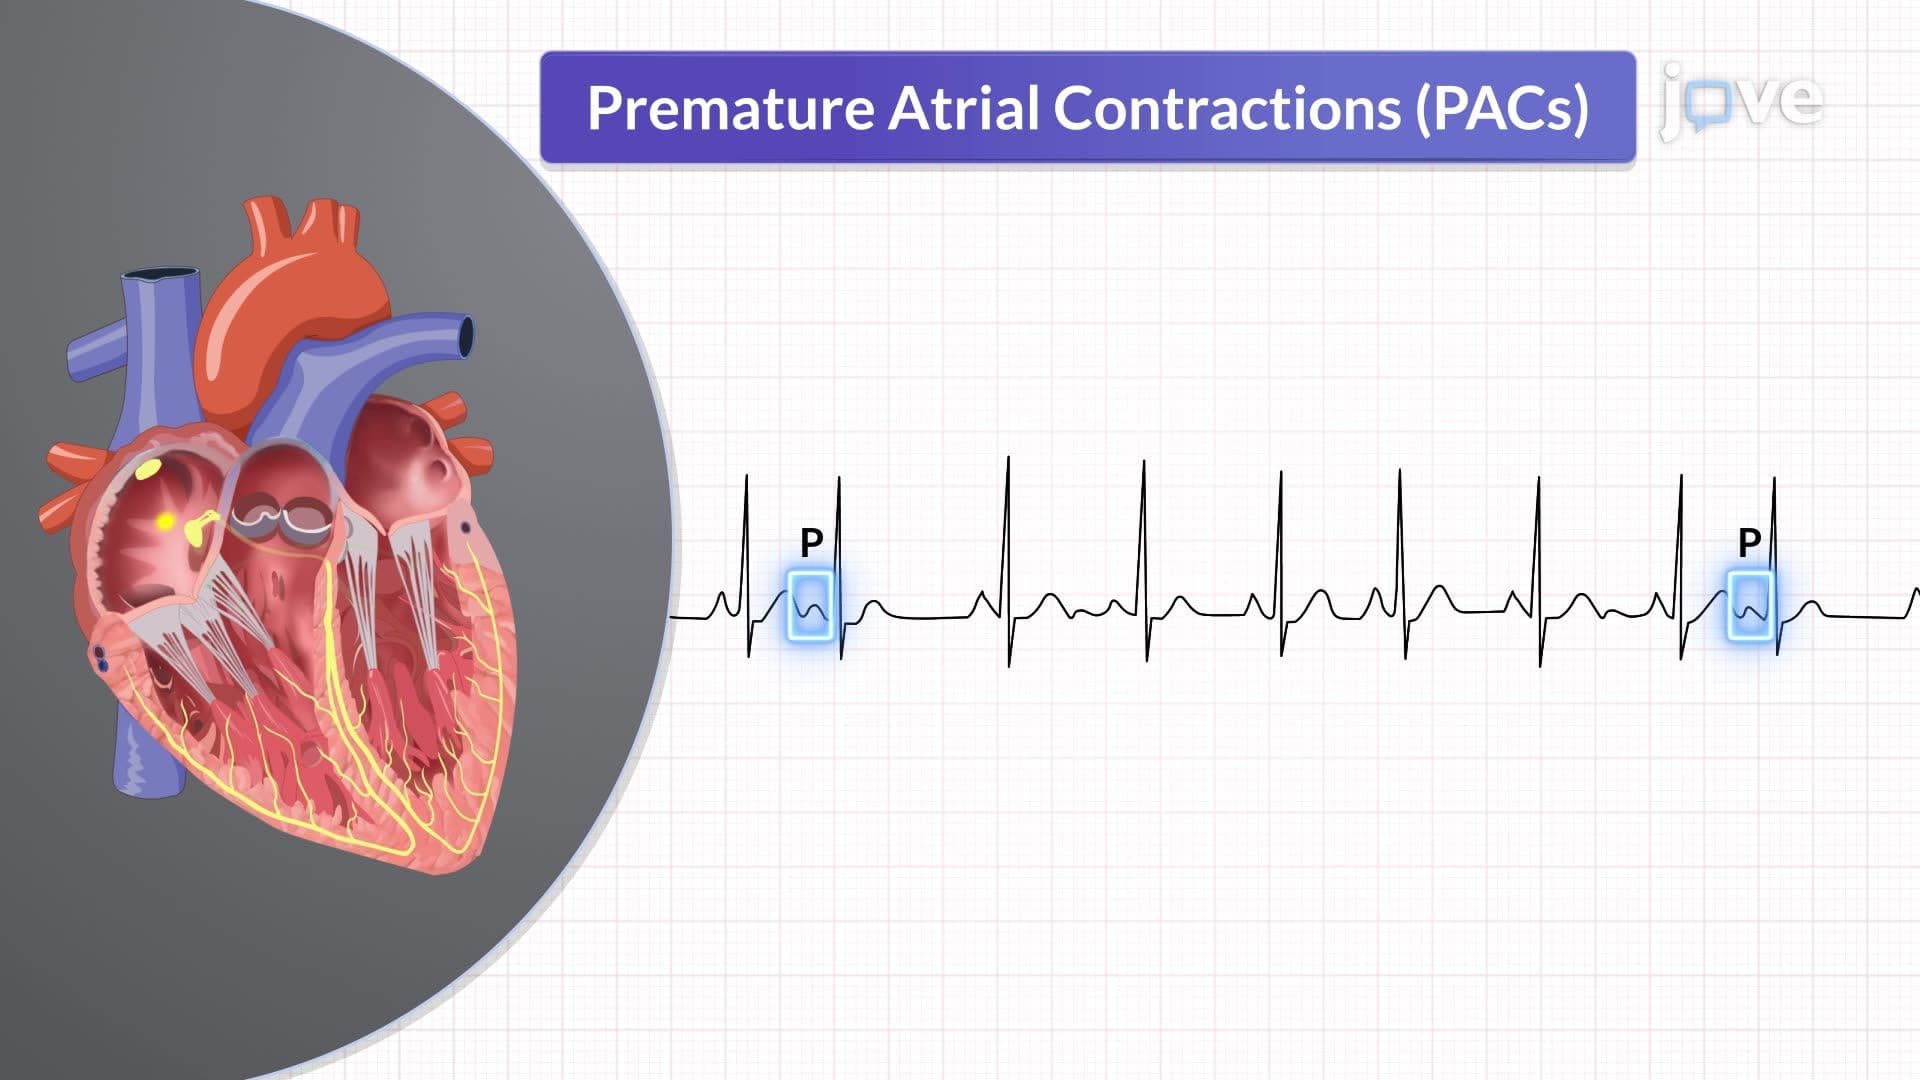 01:29
Dysrhythmias III: Characteristics of Dysrhythmias