Related Experiment Video
Updated: Jun 2, 2026
Ultrasonographic Evaluation of Salivary Glands for Sjogren's Syndrome: Diagnostic and Monitoring Insights
Published on: October 13, 2023
Distal Renal Tubular Acidosis as a Renal Manifestation of Sjögren's Syndrome: A Case Report
Sangya Sharma1, Aariez Khalid2, Guillermo A Herrera3
1Internal Medicine, University of South Alabama, Mobile, USA.

Abstract:
Distal renal tubular acidosis (dRTA) is a rare but recognized renal complication of Sjögren's syndrome (SS), often resulting from autoimmune-mediated damage to acid-base transporters in the distal nephron. It commonly presents with electrolyte abnormalities including hypokalemia and metabolic acidosis. A 47-year-old woman with chronic kidney disease presented with recurrent hypokalemia, mild proteinuria, and sicca symptoms. Workup revealed non-anion gap metabolic acidosis, a positive urine anion gap, and renal potassium wasting consistent with dRTA. Autoimmune testing showed a high-titer ANA (1:1280) and elevated SSA (>8.0), confirming SS. Renal biopsy revealed mild interstitial fibrosis and glomerulosclerosis without evidence of tubulointerstitial nephritis or immune complex deposition. This finding supports prior evidence that SS-associated dRTA may occur secondary to functional tubular defects involving distal nephron transporters, even in the absence of overt inflammatory histologic changes. Acid-base disturbances improved with potassium and bicarbonate supplementation. This case highlights that significant tubular dysfunction in SS may occur despite minimal or absent histologic evidence of tubulointerstitial nephritis. dRTA in SS may result from autoimmune targeting of distal nephron transporters such as H⁺-ATPase and anion exchanger 1. Early recognition and supportive treatment are essential to prevent complications including nephrolithiasis, progressive kidney dysfunction, and life-threatening hypokalemia. SS should be considered in patients presenting with unexplained dRTA, and timely correction of electrolyte abnormalities is critical to optimizing outcomes.
Related Concept Videos
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:29
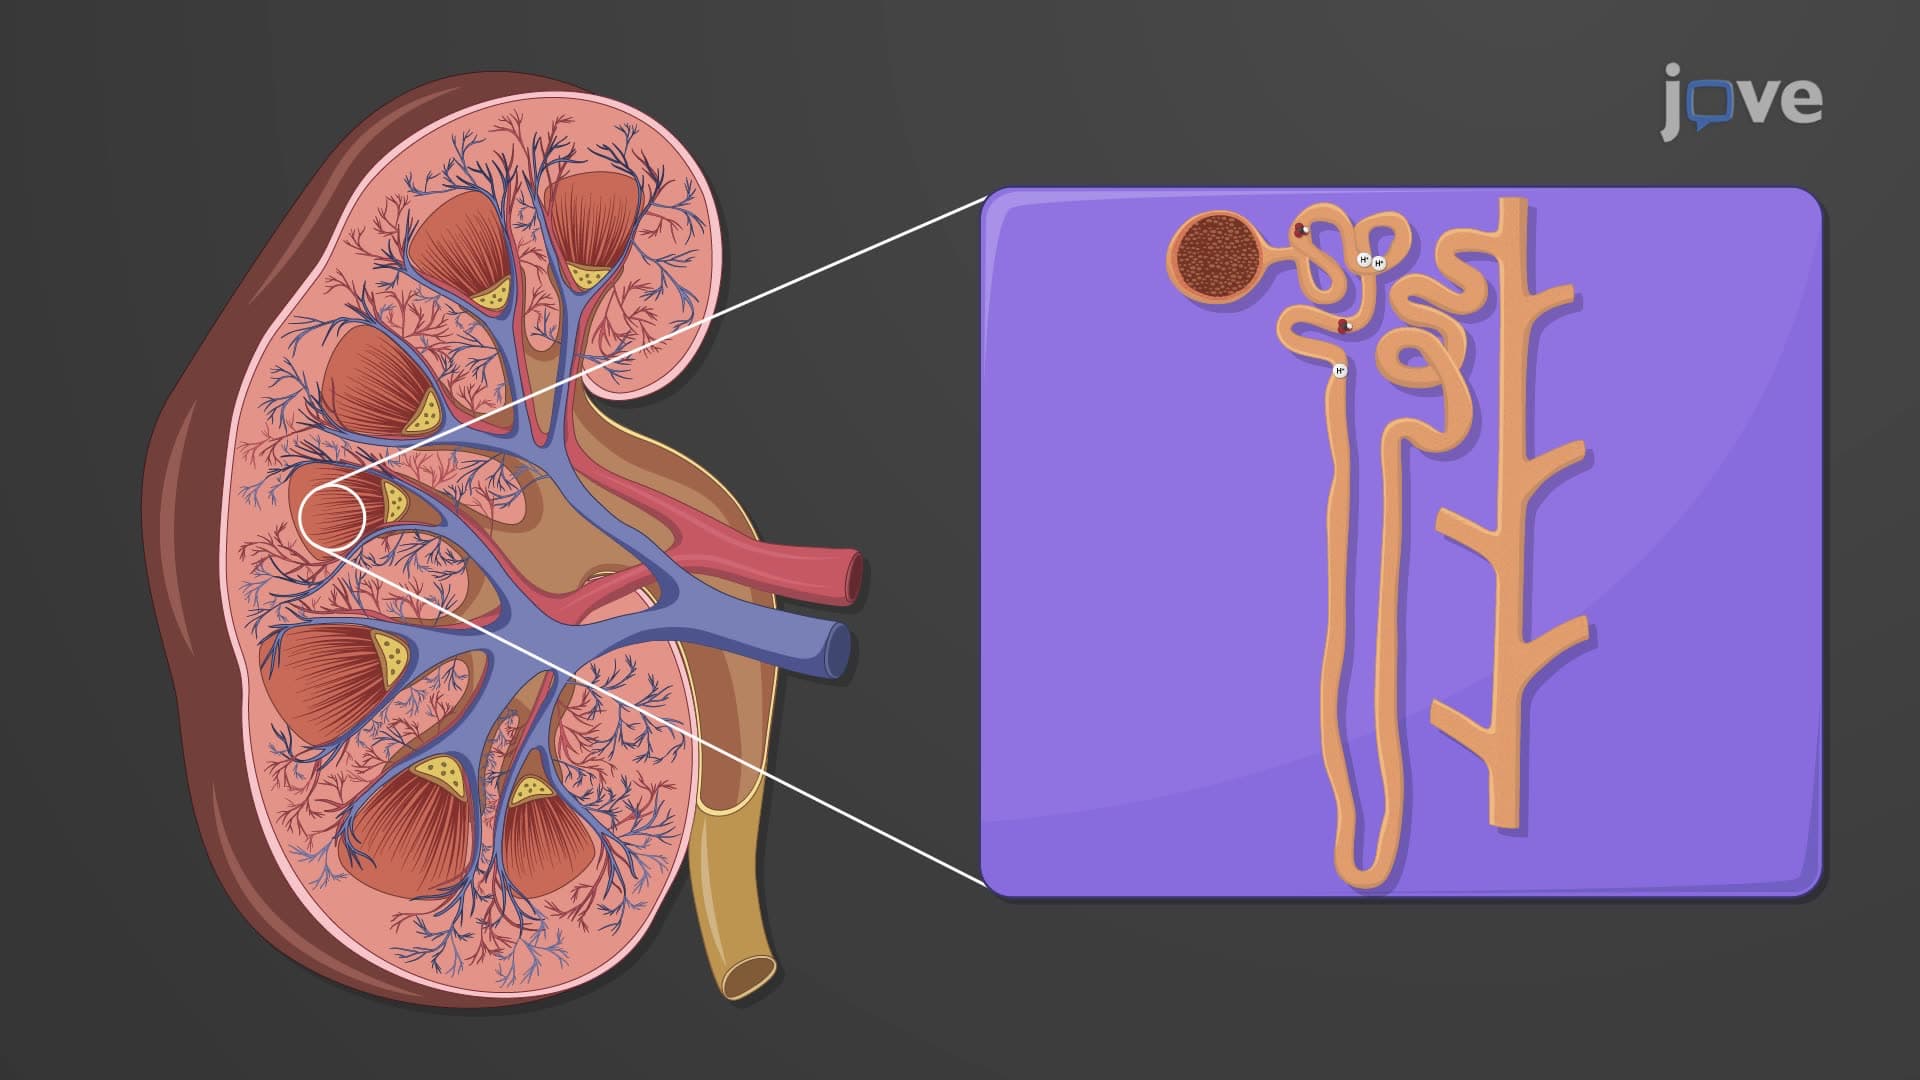
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:28
Renal Drug Excretion: Tubular Secretion
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations