Related Experiment Video
Updated: Jun 3, 2026
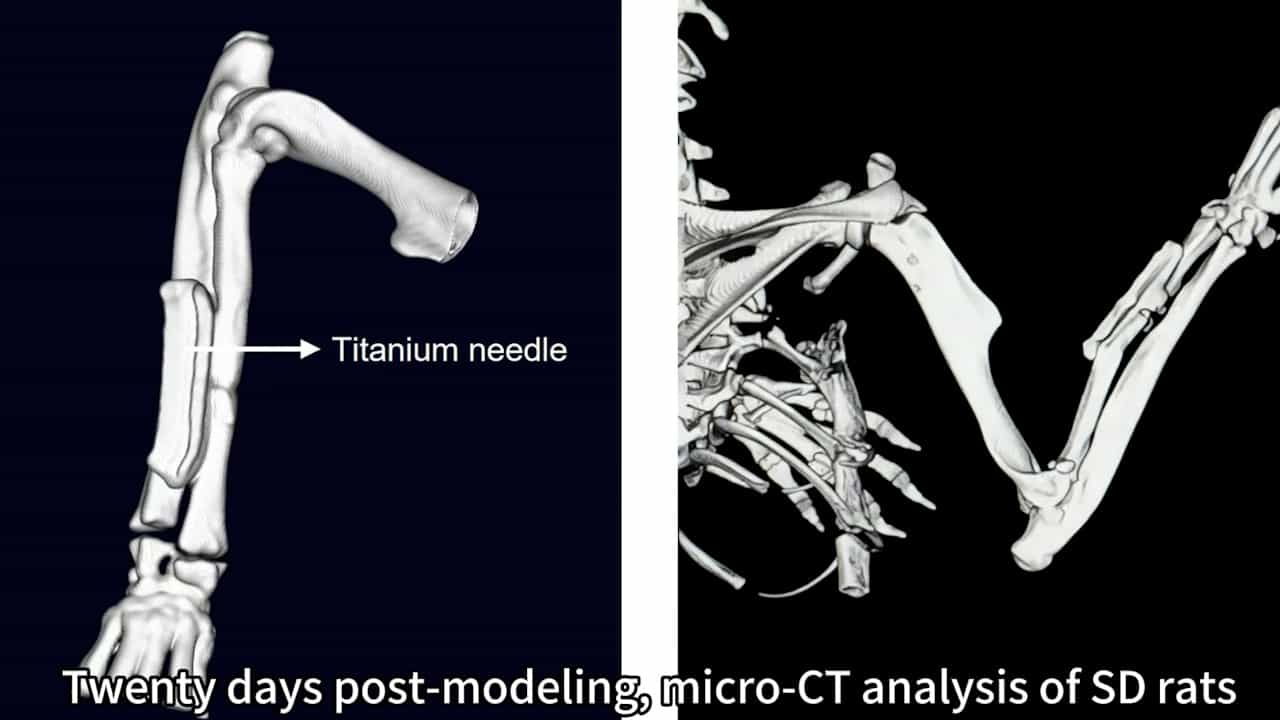

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Effectiveness and Outcomes of Cast Immobilization in Adults With Scaphoid Waist Fractures Compared With Surgical
Safwan Alghwail1, Ayman Saad2, Abdulrahman K Balbaid3
1Department of Orthopedic Surgery, Faculty of Medicine, Misurata Medical Center, Misurata University, Misurata, LBY.

Abstract:
The optimal management of acute, minimally displaced, or undisplaced scaphoid waist fractures is a clinical equipoise. Although cast immobilization is effective, it requires prolonged wrist restriction. Early surgical fixation aims to expedite recovery but introduces operative risks and incurs higher costs. This systematic review and meta-analysis synthesizes contemporary, high-quality evidence comparing the effectiveness of these two management strategies. Following the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines, a systematic search of PubMed, MEDLINE, Embase, Scopus, and Cochrane Central Register of Controlled Trials (CENTRAL) was conducted for randomized controlled trials (RCTs) and prospective comparative cohorts published since January 2013. We included studies comparing early surgical fixation versus cast immobilization in adults with acute, minimally displaced (≤ 2 mm) scaphoid waist fractures. The primary outcomes were radiological non-union incidence and time to union. Secondary outcomes included functional scores, complication rates, and return to work. A random-effects meta-analysis was performed using a restricted maximum likelihood (REML) estimator with Hartung-Knapp-Sidik-Jonkman (HKSJ) adjustments. The risk of bias was assessed using the Cochrane Risk of Bias 2 (RoB 2) and Risk of Bias in Non-randomized Studies - of Interventions (ROBINS-I) tools. The certainty of the evidence was graded using the Grading of Recommendations Assessment, Development, and Evaluation (GRADE) framework. The protocol was registered with the International Prospective Register of Systematic Reviews (PROSPERO) (CRD420261324973). Four RCT cohorts comprising 559 patients met the inclusion criteria. Surgical fixation was associated with a significantly lower risk of non-union than cast immobilization (risk ratio (RR) 0.35; 95% confidence interval (CI), 0.15 to 0.82; I² = 0%). The pooled non-union rate in the cast immobilization arm was 6% (95% CI, 0.00-0.45). The mean difference in the time to radiographic union favored surgery by -3.85 weeks, but this finding was imprecise and not statistically significant (95% CI, -21.60 to 13.90). High-certainty evidence from the largest included trial demonstrated no significant difference in long-term patient-reported functional outcomes (Patient-Rated Wrist Evaluation (PRWE)) at one or five years. The certainty of evidence for non-union and time to union was graded as moderate and downgraded for imprecision. Early surgical fixation reduces the relative risk of non-union in minimally displaced scaphoid waist fractures. However, given the high absolute union rate achievable with conservative management (94%) and the absence of demonstrable long-term functional benefit, the evidence supports initial cast immobilization as a highly effective and appropriate first-line management strategy for these patients. This approach maximizes fracture union while minimizing patient exposure to unnecessary surgical risks and healthcare expenses. Operative intervention should be reserved for cases of confirmed non-union or specific patient-related circumstances.
More Related Videos
 15:11
Surgical Fixation of Sternal Fractures: Preoperative Planning and a Safe Surgical Technique Using Locked Titanium Plates and Depth Limited Drilling
Published on: January 5, 2015
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: