Related Experiment Video
Updated: Jun 4, 2026


Non-Intubated Video-Assisted Thoracoscopic Surgery
Published on: May 26, 2023
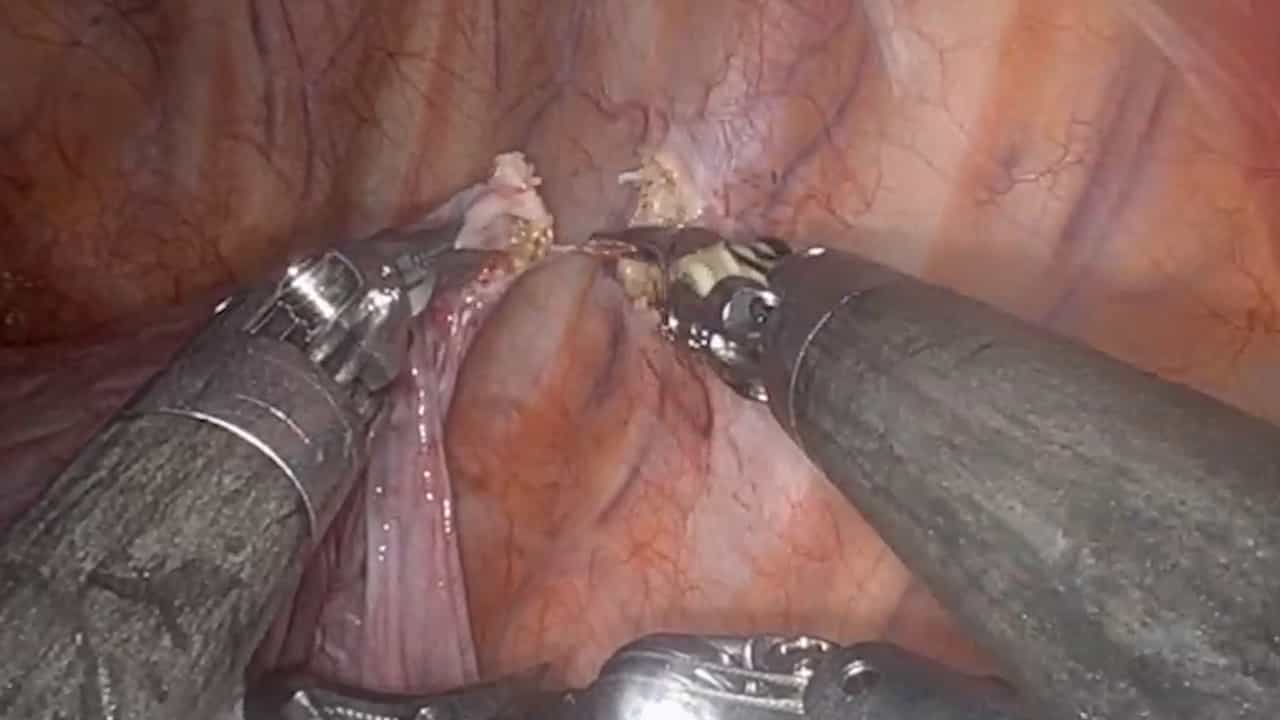
Micro-incision uniportal video-assisted thoracoscopic surgery for primary spontaneous pneumothorax in an adolescent:
Takuya Kohama1, Masayuki Tanahashi1, Maiko Yoshida1
1Division of Thoracic Surgery, Respiratory Disease Center, Seirei Mikatahara General Hospital, Hamamatsu, Japan.

Background:
Primary spontaneous pneumothorax (PSP) commonly affects adolescents and young adults, with recurrence reaching 30%. While uniportal video-assisted thoracoscopic surgery (U-VATS) has improved cosmetic outcomes and reduced access trauma, micro-incision access (<2 cm) introduces significant technical constraints, particularly regarding triangulation and instrument crowding. This report describes the successful management of an adolescent PSP case using a 1.8-cm U-VATS bullectomy, specifically addressing the technical challenges of ultra-small access through targeted ergonomic refinements.
Case Description:
A 15-year-old male with recurrent-risk apical bullae underwent U-VATS bullectomy via a 1.8-cm incision. To overcome the limited working corridor, two specific intraoperative refinements were employed: (I) a traction-suture technique to stabilize fragile lung parenchyma and guide the stapler trajectory; and (II) staple-line pre-compression with atraumatic forceps to ensure precise stapler alignment and secure closure. Resection was completed using a slim articulating stapler, followed by staple-line reinforcement with polyglycolic acid (PGA) sheets and fibrin glue. Enhanced recovery protocols, including early chest tube removal (4 hours postoperatively), facilitated discharge on postoperative day (POD) 1. The patient remained asymptomatic and recurrence-free at the 1-month follow-up.
Conclusions:
This case suggests that micro-incision U-VATS bullectomy is technically feasible when supported by ergonomic refinements such as traction suturing and pre-compression. These techniques may compensate for the inherent loss of triangulation in ultra-small access, though their broader clinical efficacy and safety profiles require further validation in larger patient cohorts.

Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques