Related Experiment Video
Updated: Jun 4, 2026
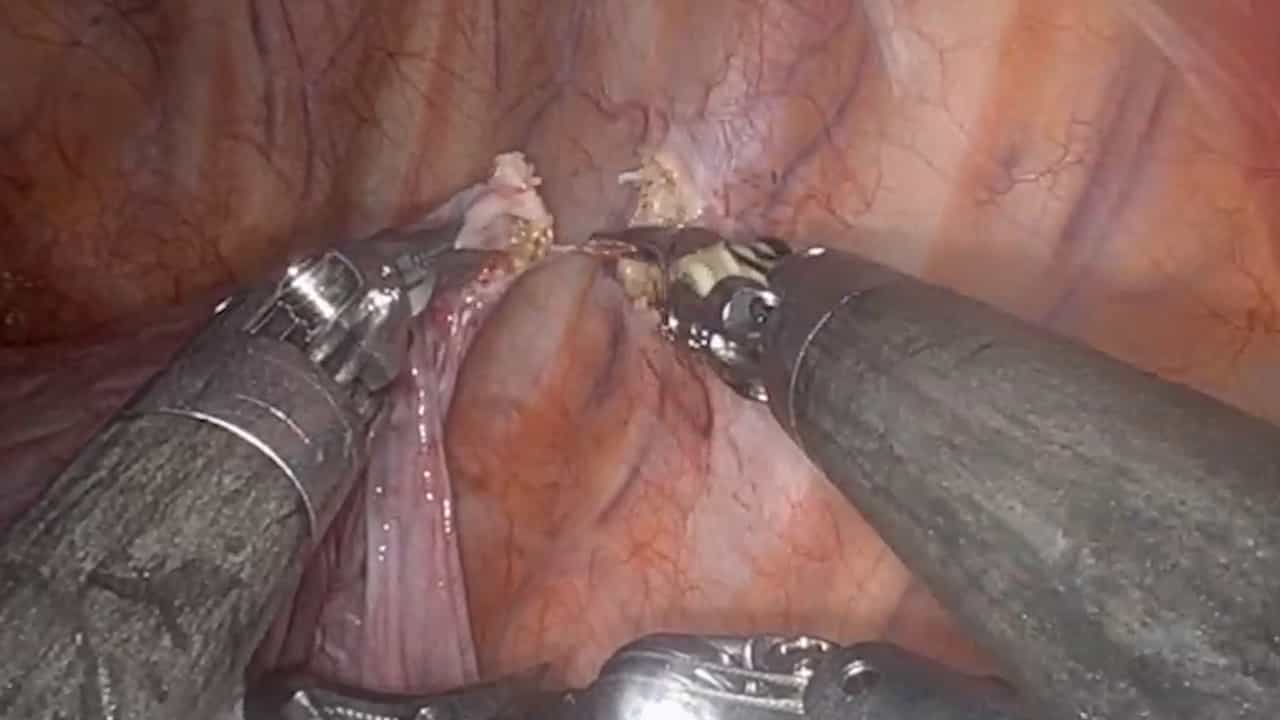
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Techniques of double-sleeve lobectomy for lung cancer: a narrative review of clinical practice
Fatemeh H Nameghi1,2, Giuseppe Aresu1, Adam Peryt1
1Division of Thoracic Surgery, Department of Cardiothoracic Surgery, Royal Papworth Hospital, Cambridge, UK.

Background And Objective:
Double sleeve (DS) lobectomy is a specialised lung-sparing operation which can be offered to patients with centrally located tumours, which can avoid pneumonectomy. The technique is historically performed via thoracotomy, but video-assisted thoracic surgery (VATS) and robotic-assisted thoracic surgery (RATS) are gaining traction as minimally invasive alternatives. There are currently no reviews of these techniques. We aim to provide a narrative review of the techniques of DS lobectomy for lung cancer.
Methods:
We searched MEDLINE and PubMed for the following Medical Subject Headings (MeSH) terms: "sleeve", "lobectomy OR resection", "lung OR cancer OR NSCLC OR tumour", "VATS, RATS, thoracotomy, open OR minimally invasive", and limited the review to all English language studies published between 1946 and 23rd October 2024 only.
Key Content And Findings:
In total, our automatic search criteria found 173 papers discussing sleeve lobectomies/resections. After manual sorting, 36 studies in total described DS operations using varied terminology, including "tangential sleeve resection with circumferential anastomosis, extended sleeve resection, sleeve resection with pulmonary angioplasty, complex sleeve resections", and most commonly "DS". Of these 36 studies, 12 (n=233) described DS resections exclusively, while the rest discussed both single and DS resections. Our review found that current literature reports little difference in long-term overall survival (OS) between single and DS operations. Surgical approach (particularly thoracotomy vs. VATS) does not appear to be a determinant of survival in DS operations. Thoracoscopic techniques may offer shorter postoperative hospital stays and less postoperative pain. In experienced units, the oncological outcomes of DS are at least equivalent to single sleeve resections and pneumonectomy, with preservation of more lung and less postoperative complications.
Conclusions:
Thoracotomy remains the most used approach in DS lobectomies; VATS may offer shorter post-operative stays than the thoracotomy approach. RATS is currently too infrequently performed to make overarching conclusions, but short-term perioperative outcomes in single-centre reports are promising. We hope that this review provides a novel and comprehensive review of evolving trends in current surgical practices of DS operations to assist clinical decision making for maximum patient benefit.