Related Experiment Video
Updated: Jun 4, 2026


Comprehensive Endovascular and Open Surgical Management of Cerebral Arteriovenous Malformations
Published on: October 20, 2017
Microsurgical resection of quadrigeminal cavernoma and preservation of developmental venous anomaly through a
Siddharth Srinivasan1, Vishnu Suresh1, Mithun Sattur1
1Department of Neurosurgery, University of Nebraska Medical Center, Omaha, Nebraska, United States.

Background:
Quadrigeminal cavernomas are rare midbrain cavernous malformations with potential for recurrent hemorrhage, aqueductal compression, hydrocephalus, brainstem dysfunction, and death. Surgical management is complicated when a developmental venous anomaly (DVA) is associated with the lesion, as injury to this venous drainage can result in brainstem infarction. Therefore, treatment must balance definitive lesion control with meticulous preservation of the DVA.
Case Description:
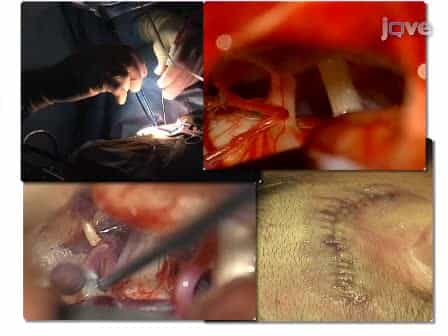
A 26-year-old man presented with an episode of acute headache and was found on magnetic resonance imaging to have a right dorsolateral quadrigeminal cavernoma (9.4 × 9.5 mm), with associated hemorrhage, triventricular hydrocephalus, and a DVA draining into the vein of Galen complex. Endoscopic third ventriculostomy was initially performed to temporize hydrocephalus, and he was discharged without deficit. Five months later, he re-presented with recurrent headache. Repeat imaging demonstrated interval lesion enlargement, rehemorrhage, and recurrent hydrocephalus. An external ventricular drain was placed. Given the patient's young age, recurrent hemorrhage, lesion growth, and ongoing obstructive hydrocephalus, definitive microsurgical resection under neuromonitoring was recommended. A subtemporal approach through the supratrochlear corridor using the lateral mesencephalic safe entry zone was selected to optimize access while preserving the vein of Labbe. Gross-total resection was achieved without neurological deficit, with preservation of the DVA and restoration of aqueductal patency.
Conlcusion:
Quadrigeminal cavernomas with associated DVA require individualized operative planning because the DVA commonly drains into the deep venous system or the vein of Galen complex. In selected patients, the subtemporal supratrochlear route provides effective access for safe resection and minimizes neurological morbidity.