Related Experiment Video
Updated: Jun 4, 2026

Murine Model of Leukemia Relapse to Induction Chemotherapy for Acute Lymphoblastic Leukemia
Published on: October 17, 2025
Computed tomography-derived sarcopenia, enteral nutritional support, and febrile neutropenia burden in children with
Şule Çalışkan Kamış1, Burak Kamış2, Metin Çil1
1Department of Pediatric Hematology and Oncology, Adana Faculty of Medicine, Adana City Training and Research Hospital, University of Health Sciences, Adana, Türkiye.

Insights
Computed tomography-derived sarcopenia is common in children with acute lymphoblastic leukemia but not linked to outcomes. Enteral nutritional support indicates clinical vulnerability, not a cause of febrile neutropenia.
Area of Science:
- Pediatric Oncology
- Radiology
- Nutritional Support
Background:
- Febrile neutropenia (FN) is a significant concern in pediatric acute lymphoblastic leukemia (ALL) treatment.
- Assessing patient vulnerability, including sarcopenia and nutritional status, is crucial for managing FN.
- Computed tomography (CT) can assess muscle mass, potentially identifying sarcopenia.
Purpose of the Study:
- To evaluate the association between CT-derived sarcopenia and enteral nutritional support with FN burden, hospital stay, and mortality in pediatric ALL patients.
- To determine if sarcopenia is an independent risk factor for adverse outcomes in this population.
Main Methods:
- Retrospective cohort study of 100 children (3-17 years) with ALL.
- Collected data on FN episodes, duration, severity, hospital stay, nutritional support, and mortality.
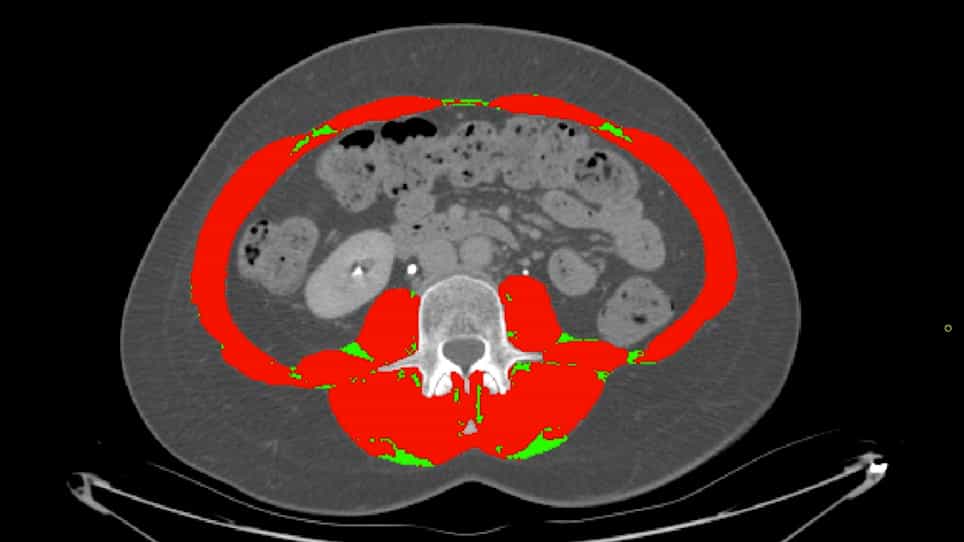
- Sarcopenia assessed using CT scans (L4-L5 level psoas muscle area) in 50 patients, defined as z-score < -2.
Main Results:
- 80% of the imaged subgroup (40/50) had sarcopenia.
- Sarcopenia was not significantly associated with FN frequency, severity, mortality, or hospital stay.
- Enteral nutritional support was linked to higher FN burden in unadjusted analysis, but this association was not significant in adjusted analysis and is considered a marker of severity.
Conclusions:
- CT-derived sarcopenia is prevalent in pediatric ALL but not independently linked to FN burden or hospital stay.
- Enteral nutritional support should be viewed as an indicator of clinical vulnerability, not a direct cause of FN.
- Further research may explore interventions targeting muscle health in pediatric ALL.
Objective:
This study aimed to evaluate computed tomography-derived sarcopenia and enteral nutritional support in relation to febrile neutropenia burden, hospital stay, and mortality in children receiving treatment for acute lymphoblastic leukemia.
Materials And Methods:
This retrospective single-center cohort included 100 children aged 3-17 years with acute lymphoblastic leukemia treated between April 2020 and March 2024. Clinical data on febrile neutropenia episodes, neutropenia duration, severe neutropenia, hospital stay, enteral nutritional support, and febrile neutropenia-related mortality were collected from hospital records. Sarcopenia analysis was restricted to 50 patients with clinically indicated computed tomography images suitable for total psoas muscle area measurement. Total psoas muscle area was measured at the L4-L5 level. Sarcopenia was defined as a total psoas muscle area z-score < -2 according to age- and sex-specific reference values.
Results:
The median number of febrile neutropenia episodes was 6.5, ranging from 1 to 19. Febrile neutropenia-related mortality was observed in 17 patients. Forty-five patients received enteral nutritional support. Enteral nutritional support was associated with higher febrile neutropenia burden in unadjusted analysis; however, this was not interpreted as causal because enteral feeding may reflect underlying clinical severity. Among the 50 patients with total psoas muscle area data, 40 patients, corresponding to 80% of the imaged subgroup, were sarcopenic. Sarcopenia was not significantly associated with febrile neutropenia frequency, severe neutropenia, mortality, or hospital stay. In exploratory adjusted analysis, enteral nutritional support showed a borderline but non-significant association with febrile neutropenia frequency (IRR: 1.16, 95% CI: 1.00-1.36, p = 0.052).
Conclusion:
Computed tomography-derived sarcopenia was common among imaged children with acute lymphoblastic leukemia but was not independently associated with febrile neutropenia burden or hospital stay. Enteral nutritional support should be interpreted as a marker of clinical vulnerability rather than a causal determinant of febrile neutropenia.