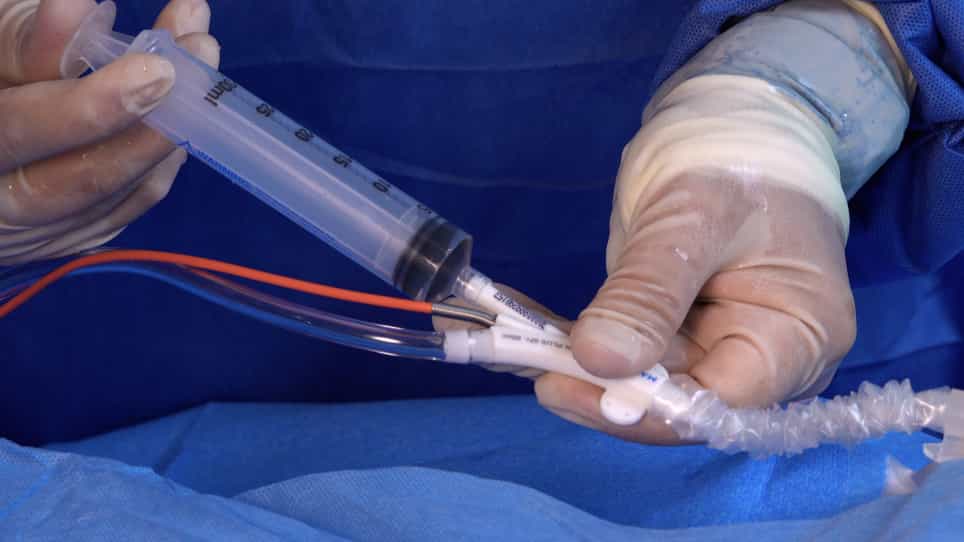
Related Experiment Video
Updated: Jun 4, 2026

Utilizing Percutaneous Ventricular Assist Devices in Acute Myocardial Infarction Complicated by Cardiogenic Shock
Published on: June 12, 2021
Comparative outcomes of intra-aortic balloon pump versus impella in non-myocardial infarction cardiogenic shock: A
Omar Khalil1, Arwa Saed Aldien1, Peng Cai2
1Department of Internal Medicine, Virginia Commonwealth University, Richmond, VA.

Insights
High-flow Impella 5.0/LD/5.5 devices improved survival and advanced therapy rates in non-myocardial infarction cardiogenic shock (non-MI CS) patients compared to intra-aortic balloon pumps (IABPs). Low-flow Impella 2.5/CP devices showed worse outcomes than IABPs.
Area of Science:
- Cardiology
- Mechanical Circulatory Support
- Critical Care Medicine
Background:
- Cardiogenic shock (CS) management often involves mechanical support devices.
- Intra-aortic balloon pumps (IABPs) and percutaneous left ventricular assist devices (pLVADs, Impella) are commonly used.
- Evidence for non-myocardial infarction (non-MI) CS, especially with newer Impella models, is limited.
Purpose of the Study:
- To compare the outcomes of IABP versus various Impella devices in patients with non-MI CS.
- To evaluate the effectiveness of different Impella models (2.5/CP vs. 5.0/LD/5.5) in non-MI CS.
Main Methods:
- Retrospective analysis of National Inpatient Sample (NIS) data from 2016-2022.
- Inclusion of patients diagnosed with non-MI CS who received IABP, Impella 2.5/CP, or Impella 5.0/LD/5.5.
- Comparison of in-hospital mortality, rates of orthotopic heart transplant (OHT) and durable left ventricular assist device (LVAD) implantation, transfusion requirements, length of stay, and hospital charges.
Main Results:
- Impella 5.0/LD/5.5 use was linked to lower mortality (8.2% vs. 14.9%), higher OHT (27.6% vs. 11.7%) and LVAD rates (45.1% vs. 15.6%) compared to IABP, but with longer stays and higher charges.
- Impella 2.5/CP use was associated with higher mortality (39.6% vs. 23.6%) and lower OHT/LVAD rates than IABP, alongside shorter stays and lower charges.
- Significant differences (P<0.05) were observed across all compared outcomes between device groups.
Conclusions:
- In non-MI CS, high-flow Impella 5.0/LD/5.5 devices demonstrated improved survival and advanced therapy rates over IABP.
- Low-flow Impella 2.5/CP devices were associated with worse outcomes than IABP in non-MI CS.
- While Impella 5.0/LD/5.5 offered benefits, it also resulted in increased resource utilization, including transfusion needs and hospitalization duration.
Background:
Intra-aortic balloon pumps (IABPs) and percutaneous left ventricular assist devices (pLVADs; Impella) are used to stabilize patients with cardiogenic shock (CS). While recent evidence supports their usefulness in myocardial infarction (MI)-related CS, data on non-MI CS, particularly regarding newer Impella models, remain limited. We compared outcomes associated with IABP versus various Impella devices in non-MI CS.
Methods:
We retrospectively analyzed National Inpatient Sample (NIS) data from 2016 to 2022 to identify patients with non-MI CS who received IABP, Impella 2.5/CP, or Impella 5.0/LD/5.5. Outcomes explored were in-hospital mortality, rates of orthotopic heart transplant (OHT) and durable left ventricular assist device (LVAD) implantation, blood transfusion requirements, length of stay, and total hospital charges.
Results:
Among patients with non-MI CS, Impella 5.0/LD/5.5 use was associated with lower in-hospital mortality (8.2% vs 14.9%, P=0.006), higher rates of OHT (27.6% vs 11.7%, P<0.001) and LVAD implantation (45.1% vs 15.6%, P<0.001), longer hospital stays (40.4 vs 23.5 d, P<0.001), greater transfusion requirements (21.8% vs 13.5%, P=0.004), and higher total charges ($1350,236 vs $653,962, P<0.001) than IABP. In contrast, Impella 2.5/CP use was associated with greater in-hospital mortality (39.6% vs 23.6%, P<0.001), lower rates of OHT and LVAD implantation, shorter hospital stays (11.2 vs 17.5d, P<0.001), and lower total charges ($416,416 vs $486,318, P<0.001) than IABP.
Conclusions:
In non-MI CS, the high-flow Impella 5.0/LD/5.5, but not the low-flow Impella 2.5/CP, was associated with better survival and higher rates of advanced therapies than IABP, albeit at the expense of greater transfusion requirements, longer hospitalization, and greater resource utilization.