Related Experiment Video
Updated: Jun 5, 2026
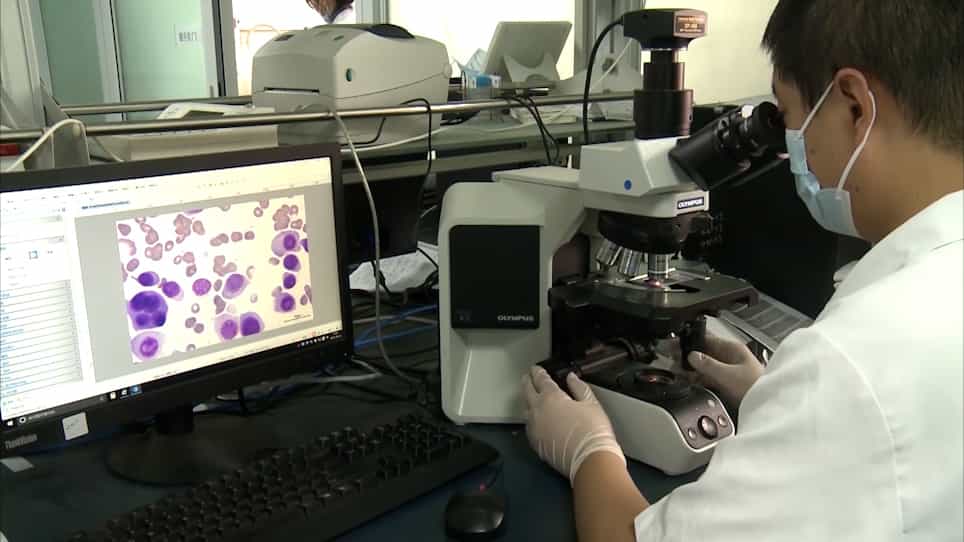

Interphase Fluorescence in situ Hybridization of Bone Marrow Smears of Multiple Myeloma
Published on: April 15, 2022
Distinct clinical, molecular, and treatment response profiles in primary and secondary myelofibrosis: a single-center
Wenya Liu1,2, Yue Ren1, Yingao Liang1
1Department of Hematology, Tianjin Medical University General Hospital, Tianjin, China.

Background:
Myelofibrosis (MF) includes primary myelofibrosis (PMF) and secondary myelofibrosis (SMF) evolving from essential thrombocythemia (ET) or polycythemia vera (PV). The clinical and molecular heterogeneity of MF remains incompletely characterized in real-world cohorts.
Methods:
We retrospectively analyzed 56 patients with MF treated at a single center, including 33 with PMF and 23 with SMF (ET-MF or PV-MF). Clinical characteristics, laboratory parameters, bone marrow pathology, cytogenetic and molecular findings, treatment strategies, and follow-up outcomes were evaluated.
Results:
PMF patients demonstrated a predominantly cytopenic phenotype, characterized by more severe anemia and lower platelet counts, whereas SMF patients showed a more proliferative profile with higher leukocyte and platelet counts. Bone marrow examination revealed typical megakaryocytic atypia and reticulin fibrosis in both groups, while PMF exhibited more heterogeneous marrow cellularity. Mutational analysis showed that JAK2 was the most frequent driver mutation, followed by CALR and MPL, and approximately one-third of PMF cases were triple-negative. Among additional mutations, ASXL1 was the most common, followed by spliceosome-related genes such as SF3B1 and U2AF1. Patients harboring JAK2 mutations displayed higher hemoglobin levels, red blood cell counts, and neutrophil percentages compared with JAK2-wild type patients. Treatment strategies included supportive care, interferon, hydroxyurea, and ruxolitinib. During follow-up, most patients remained alive, although leukemic transformation occurred in a small proportion of PMF cases.
Conclusions:
PMF and SMF demonstrate distinct clinical phenotypes despite sharing bone marrow fibrosis as a common endpoint. The mutational landscape highlights the genetic heterogeneity of MF and underscores the importance of integrating clinical, pathological, and molecular information to improve disease characterization and guide individualized management.

