Related Experiment Video
Updated: Jun 5, 2026
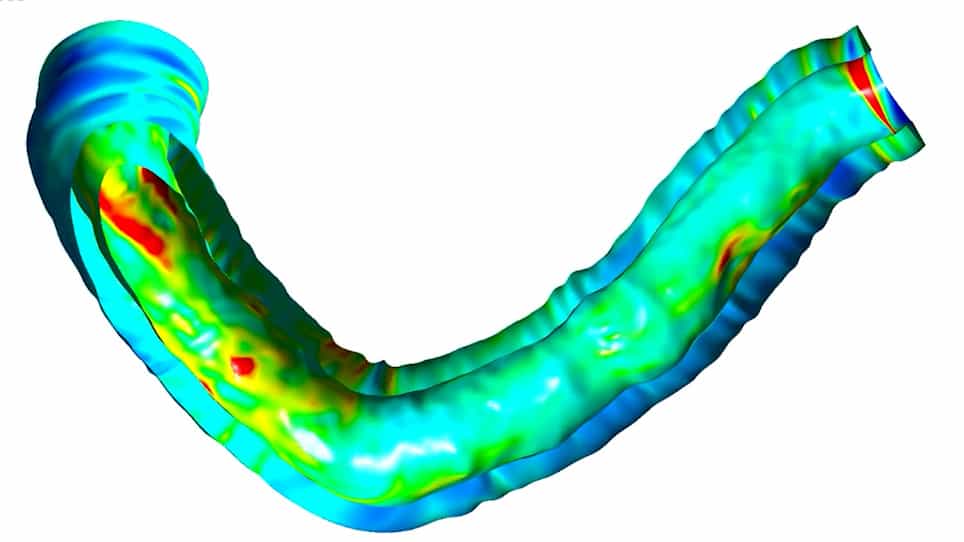

Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Long-Term Lesion Progression After Left Main Distal Bifurcation Stenting: Insights From Bifurcation Angle Variation
En Chen1,2,3, Danqing Hu4, Hong Zheng1,2,3
1Department of Cardiology, Fujian Medical University Union Hospital, Fujian Medical University, 350001 Fuzhou, Fujian, China.

Insights
Changes in the distal bifurcation angle (DBAC) after left main coronary bifurcation lesion stenting vary by strategy. Dual stenting leads to persistent DBAC narrowing and increased lesion progression, especially in the LCX.
Area of Science:
- Cardiovascular Medicine
- Interventional Cardiology
- Medical Imaging
Background:
- The clinical significance of dynamic changes in bifurcation angles after percutaneous coronary intervention (PCI) for left main coronary bifurcation lesions (LMCBLs) is not fully understood.
- Long-term evolution of these angles and their impact on lesion progression post-stenting require further investigation.
Purpose of the Study:
- To evaluate temporal changes in the bifurcation angle throughout the cardiac cycle (BAC) after PCI for LMCBLs.
- To assess the impact of these changes on lesion progression in patients undergoing single- or dual-stenting.
Main Methods:
- Quantified proximal (PBAC) and distal (DBAC) bifurcation angles throughout the cardiac cycle using 2D quantitative coronary angiography.
- Measurements were taken pre-procedure, immediately post-procedure, and at long-term follow-up.
- Lesion progression was assessed by the increase in diameter stenosis percentage (iDS%) from post-procedure to follow-up.
Main Results:
- The distal bifurcation angle (DBAC) narrowed post-stenting but rebounded in the single-stenting group during follow-up.
- In contrast, the DBAC remained narrowed in the dual-stenting group.
- Lesion progression was more pronounced in dual-stented patients, particularly in the left circumflex (LCX) vessel, with pre-procedural PBAC correlating with LCX progression.
Conclusions:
- The proximal bifurcation angle (PBAC) remains stable over time and across stenting strategies.
- The distal bifurcation angle (DBAC) decreases post-stenting, with differential recovery based on stenting strategy.
- Pre-procedural PBAC is an independent risk marker for future LCX progression in patients with dual-stented LMCBLs.
Background:
The clinical impact of changes in the bifurcation angle throughout the cardiac cycle (BAC) after percutaneous coronary intervention (PCI) for left main coronary bifurcation lesions (LMCBLs) remains controversial, and the associated long-term evolution post-stenting remains unknown. Therefore, this study aimed to evaluate temporal changes in the BAC and the related impact on lesion progression in patients undergoing single- or dual-stenting.
Methods:
Proximal (PBAC) and distal (DBAC) bifurcation angles were quantified throughout the cardiac cycle using two-dimensional quantitative coronary angiography at optimal views before the procedure, immediately after, and at long-term follow-up. These measurements represented the absolute difference between the end-diastolic and end-systolic angles for the left main (LM) to the left circumflex (LCX) and for the left anterior descending (LAD) to the LCX. Lesion progression was assessed from increases in diameter stenosis percentage (iDS%) from post-procedure to follow-up.
Results:
A total of 284 patients underwent single-stenting (LM-LAD), and 84 underwent dual stenting (LM-LAD-LCX). Changes in the PBAC were unaffected by interventional strategies or time. The DBAC was narrowed post-stenting in all patients, but rebounded to pre-procedural levels during follow-up in the single-stenting group. In contrast, the DBAC remained at post-procedural levels in the dual-stenting group. Lesion progression was more pronounced in patients with dual stenting, particularly in the LCX. The pre-procedural PBAC correlated linearly with the iDS%-LCX metric in the dual stenting.
Conclusions:
The PBAC remained stable over time and across strategies, whereas the DBAC decreased post-stenting. During follow-up, the DBAC rebounded in the single-stenting group but remained low in the dual-stenting group. The pre-procedural PBAC represents an independent anatomical risk marker for future LCX progression in patients with dual-stented LMCBLs.

