Mammography screening in Tennessee: a tract-level spatial analysis of geographic and socioeconomic disparities
Related Experiment Video
Updated: Jun 5, 2026
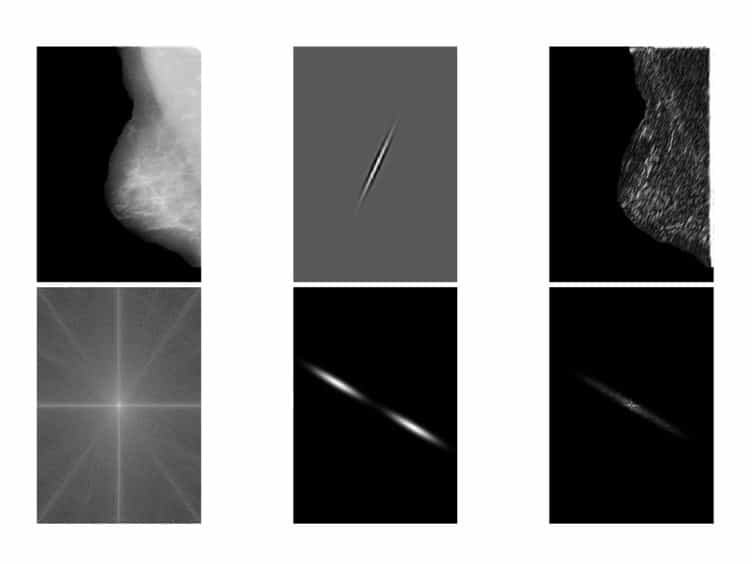
Detection of Architectural Distortion in Prior Mammograms via Analysis of Oriented Patterns
Published on: August 30, 2013
Sima Namin1, Jonathan S Wall2, R Eric Heidel3
1Office of Research Support, University of Tennessee Health Science Center, 1924 Alcoa Highway, Knoxville, TN, 37920, USA. namin.sima@gmail.com.

Purpose:
Despite improvements in early detection, Tennessee ranks among the top ten states for breast cancer mortality among women. Mammography screening and early diagnosis are critical to reducing mortality, yet access and uptake vary widely across the State. We tested whether access to diagnostic services affected screening in the State.
Methods:
We merged CDC PLACES estimates of screening among women aged 50-74 with geocoded FDA-certified mammography facilities to derive drive-time categories. Tract covariates included education, poverty, insurance, race/ethnicity, primary care provider density, urban/rural status, and Appalachian designation. We mapped hot/cold spots using Getis-Ord Gi* and fit four nested beta-regression models: geography only, socioeconomic only, combined, and combined plus log-provider density.
Results:
Median screening prevalence was 74.8%. Hotspots clustered around Memphis, Nashville, and Knoxville; cold spots in Central Appalachian and western floodplain tracts. Geography explained ~ 23% of between-tract variation (pseudo-R2 = 0.238); socioeconomic covariates ~ 61% (0.607). In combined models, drive-time and Appalachian effects attenuated. Urban tracts screened 0.72 percentage points (pp) higher than rural, and each 1-pp rise in adults without a high-school diploma predicted - 0.13 pp.
Conclusion:
Urbanicity and education were the primary drivers of mammography screening disparities in Tennessee. To improve early diagnosis and outcomes, interventions should prioritize educational outreach, poverty reduction, insurance expansion, and improved geographic access, via mobile units or telehealth, targeting remote cold-spot tracts.