Related Experiment Video
Updated: Jun 5, 2026

Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
Quantitative analysis of colon-lengthening techniques in laparoscopic low rectal cancer surgery with left colic
Yunjie Shi1, Jing Wu2, Minxin Gao2
1Department of Colorectal Surgery, The First Affiliated Hospital (Changhai Hospital), Naval Medical University, Shanghai, 200433, China. shiyunpengjie@126.com.

Purpose:
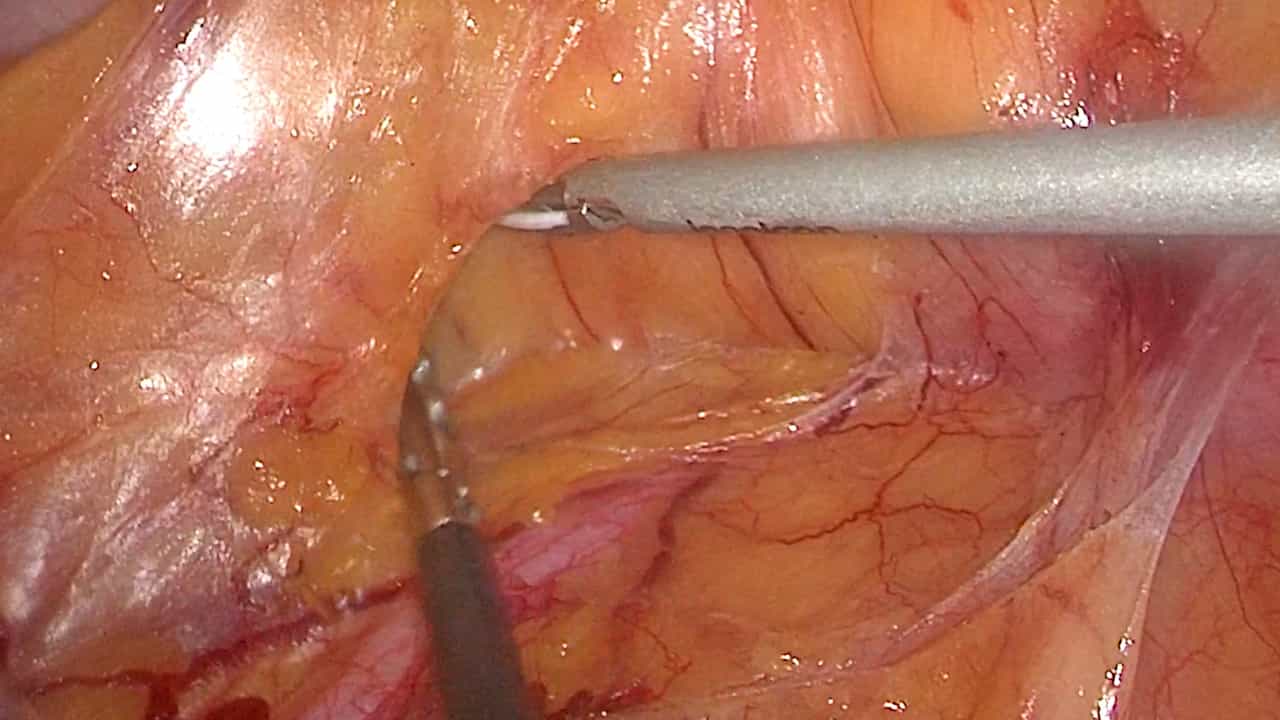
To quantify colonic lengthening achieved by complete splenic flexure mobilization (SFM) and high inferior mesenteric vein (IMV) ligation while preserving the left colic artery (LCA) in laparoscopic low rectal cancer surgery.
Methods:
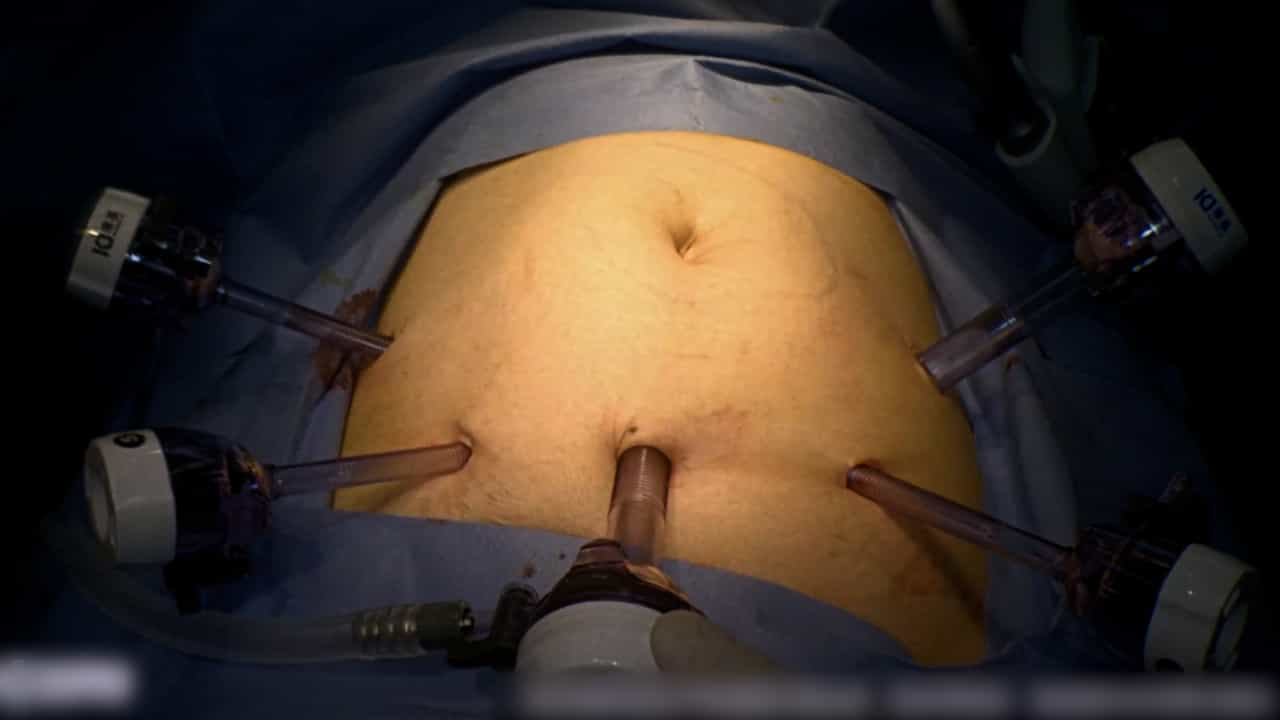
Standardized LCA-preserving anterior resection was performed on 18 fresh cadavers. The additional colonic length gained after each maneuver was measured under tension-free conditions. High inferior mesenteric artery (IMA) ligation, which sacrifices the LCA, was also measured as a reference comparator.
Results:
The mean baseline resection length was 10.4 ± 6.9 cm. Additional gains: 6.3 ± 1.7 cm after SFM and 14.4 ± 2.1 cm after high IMV ligation (maximum gain under LCA preservation). As a reference, high IMA ligation (without LCA preservation) provided a lengthening of 18.4 ± 1.7 cm. In malrotation (n = 2), IMV ligation yielded only 10.2-12.3 cm of mesenteric length. BMI correlated positively with the baseline length (r = 0.529, p = 0.023).
Conclusions:
Under LCA preservation, high IMV ligation provides the greatest lengthening (14.4 cm), although efficacy is reduced with malrotation. These data guide preoperative planning for tension-free anastomosis and adequate margin placement.