Related Experiment Video
Updated: Jun 8, 2026
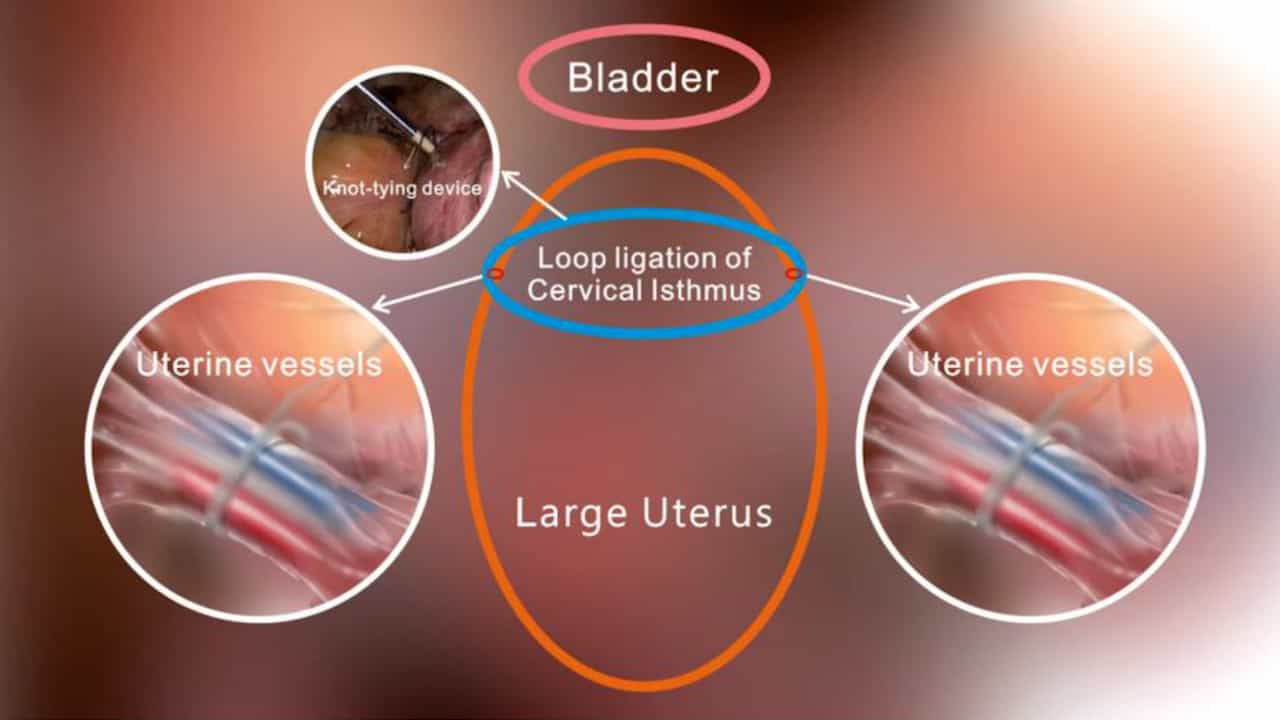

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Age-related patterns in hysterectomy: indications and surgical route selection in a three-year tertiary-center cohort
Havva Betül Bacak1, Enes Serhat Coșkun1
1From the Department of Obstetrics and Gynecology, Gaziosmanpaşa Training and Research Hospital, Istanbul, Türkiye.

Background:
Hysterectomy indications and surgical route selection may vary with age due to shifting case mix.
Objectives:
To describe age-stratified hysterectomy indications and routes and identify factors independently associated with route selection.
Design:
Retrospective chart review.
Settings:
Single-center, tertiary-care teaching and research hospital, Department of Obstetrics and Gynecology.
Methods:
Hysterectomies performed for benign or premalignant indications between 2022 and 2024 were identified and verified. Patients were grouped according to age [<50, 50-59, or ≥60 years]. Indications were assigned using PALM-COEIN and grouped clinically. Routes were categorized as open abdominal, laparoscopic/VNOTES, or vaginal. Comparisons used Kruskal-Wallis and chi-square tests. Multinomial and binary logistic regression adjusted for age group, parity, comorbidity, smoking, and prior pelvic/abdominal surgery.
Main Outcome Measures:
age-stratified hysterectomy route and age-stratified indications and predictors of minimally invasive versus open surgery.
Sample Size:
769 hysterectomies.
Results:
Primary indications differed significantly by age group (P<.001; Cramer's V=0.38): treatment-resistant abnormal uterine bleeding predominated in patients <50 and 50-59 years, whereas pelvic organ prolapse predominated in patients ≥60 years. Surgical route also varied by age (P<.001; Cramer's V=0.34): open abdominal hysterectomy decreased from 47.3% in patients <50 years to 15.3% in those ≥60 years, while vaginal hysterectomy increased from 4.0% to 52.6%. In multinomial regression, age ≥60 years was associated with higher odds of laparoscopic/VNOTES versus open surgery (aOR 1.97, 95% CI 1.08-3.61) and vaginal versus open surgery (adjusted odds ratio, aOR 21.60, 95% confidence interval, CI 10.02-46.60). In binary regression, age ≥60 years (aOR 4.18, 95% CI 2.41-7.26) and parity (aOR 1.18 per birth, 95% CI 1.06-1.32) favored minimally invasive surgery.
Conclusions:
Age-related indication shifts accompanied major route changes, with greater vaginal and minimally invasive use among older patients.
Limitations:
Single-center retrospective design; residual confounding by indication and uterine size; conversions and standardized complications were not analyzed; unmeasured clinical/surgeon factors.