Related Experiment Videos
Relationship between norepinephrine dose and outcome in septic shock: a retrospective study
Lorenzo Antonino Calabrò1, Marco Pasetto2,3, Stefano Zorzi2,4
1Department of Intensive Care, Hôpital Erasme, Université Libre de Bruxelles, 1070, Brussels, Belgium. l.calabro@hubruxelles.be.

Background:
High-dose norepinephrine (NE) is frequently required in septic shock, but the association of NE dose with outcome remains incompletely characterised. We aimed to evaluate the relationship between NE dosing, mortality and ischemic complications, and to identify clinically relevant NE dose ranges.
Methods:
This retrospective single-centre cohort study included adult patients (≥ 18 years) admitted to the Intensive Care Unit (ICU) between 2016 and 2022 with septic shock on admission, complete data on NE dosing and ICU mortality; patients receiving mechanical circulatory support were excluded. NE dosing variables (initial-dose, highest dose within 24 h, and peak ICU-dose) were collected. Adjusted optimal binning was used to identify NE peak-dose ranges associated with ICU and in-hospital mortality. Multivariable logistic regression was adjusted for age, APACHE II, and SOFA score, and time-dependent Cox models assessed associations with secondary ischemic outcomes.
Results:
A total of 506 patients were included. Median NE peak-dose was 0.5 [0.2-1.2] µg/kg*min. Four NE peak-dose ranges were identified: 0.05-0.6, 0.61-1.2, 1.2-3.0, and > 3.0 µg/kg*min. ICU and in-hospital mortality increased stepwise across these ranges, from 20.7 and 32.4% in the lowest group to 100% in patients receiving > 3.0 µg/kg*min. This association persisted after exclusion of patients with withdrawal of life-sustaining therapies. Adjusted odds ratios for ICU mortality were 1.88 [0.97-3.64] and 2.55 [1.38-5.57] in the 0.61-1.2 and 1.2-3.0 µg/kg*min groups, respectively. NE peak-dose showed fair discrimination for ICU mortality (AUROC of 0.75), with an optimal Youden threshold of 0.78 µg/kg*min. Most ischemic complications were infrequent and not dose dependent, except for myocardial ischemia and unexpected cardiac arrest, which were significantly associated with higher NE doses.
Conclusions:
In septic shock, increasing NE peak-doses are associated with a significant stepwise increase in ICU and in-hospital mortality across four distinct dose ranges. Ischemic complications are uncommon and largely independent of NE dose.
Related Concept Videos
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:28
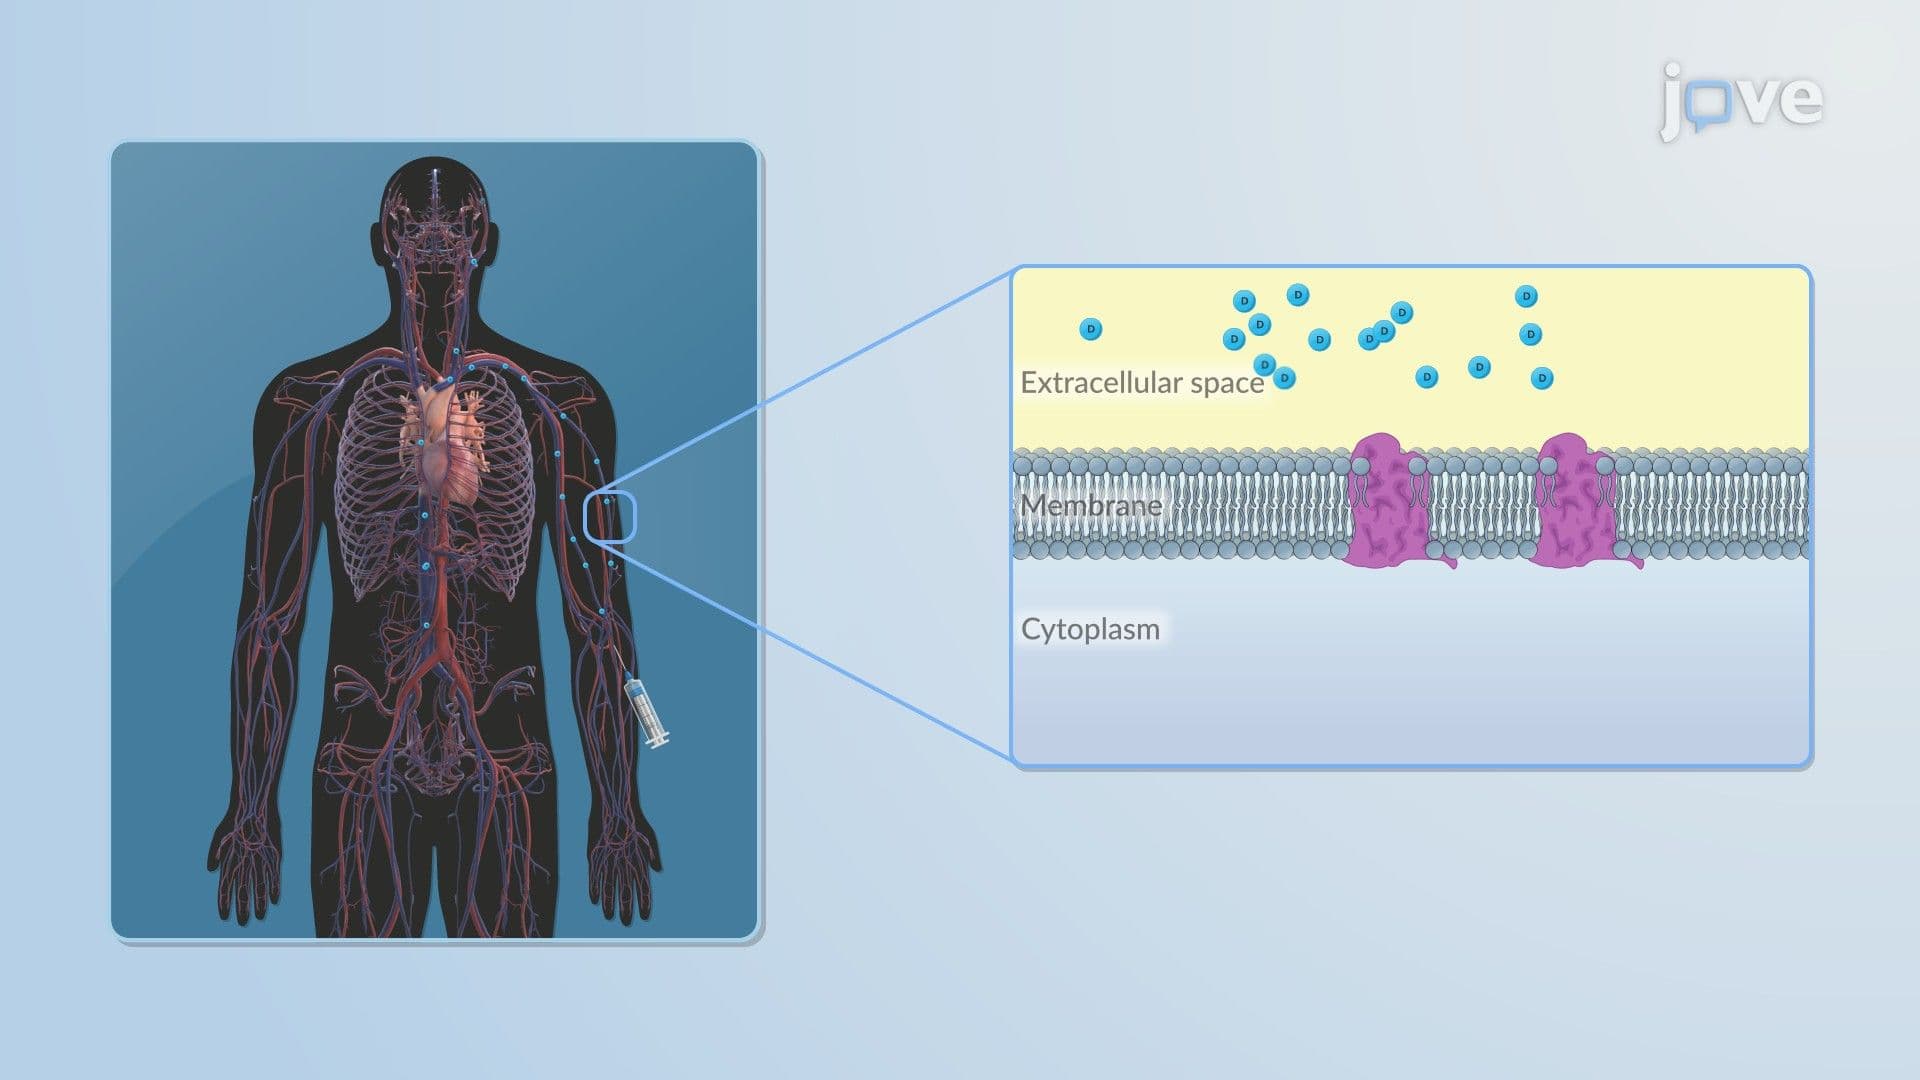
Pharmacokinetic–Pharmacodynamic Relationship: Dose to Pharmacological Effect
 01:23
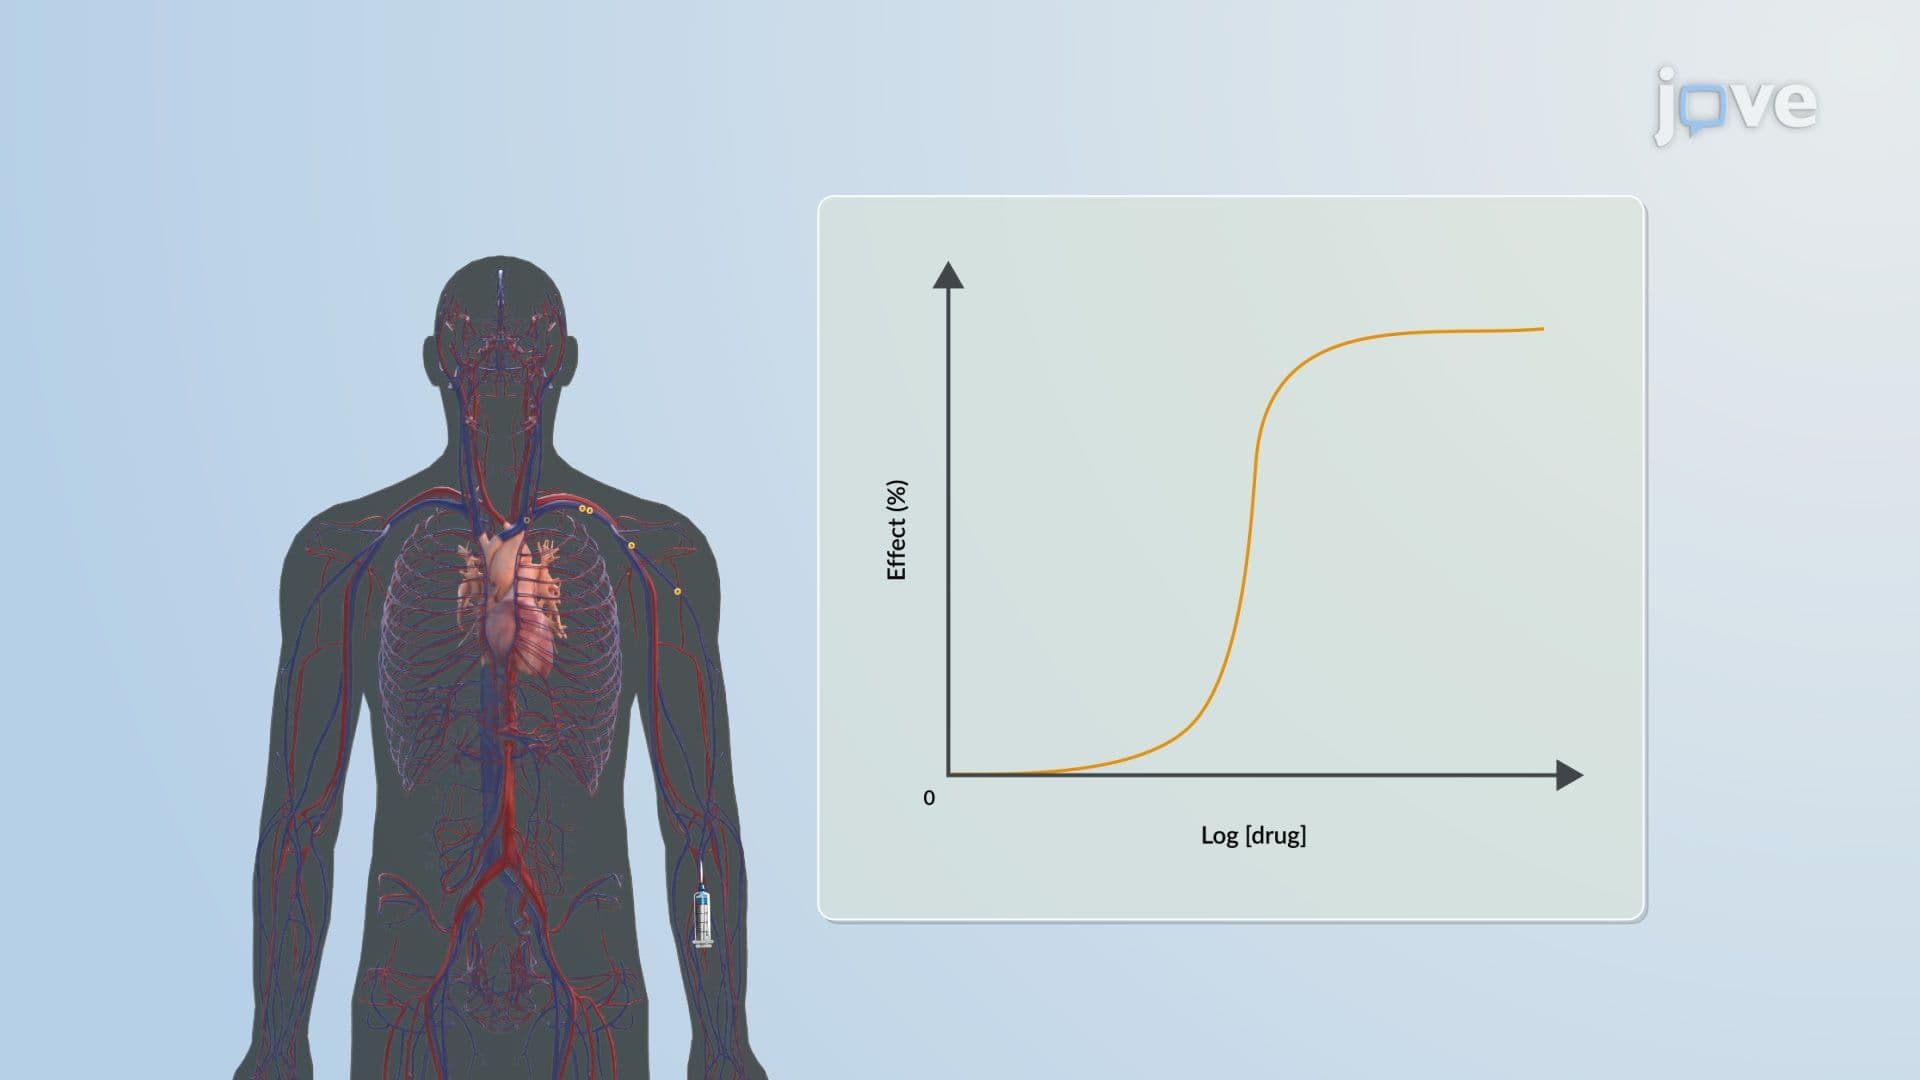
Pharmacokinetic–Pharmacodynamic Relationship: Intensity of Dose-Effect Relationship
 01:26
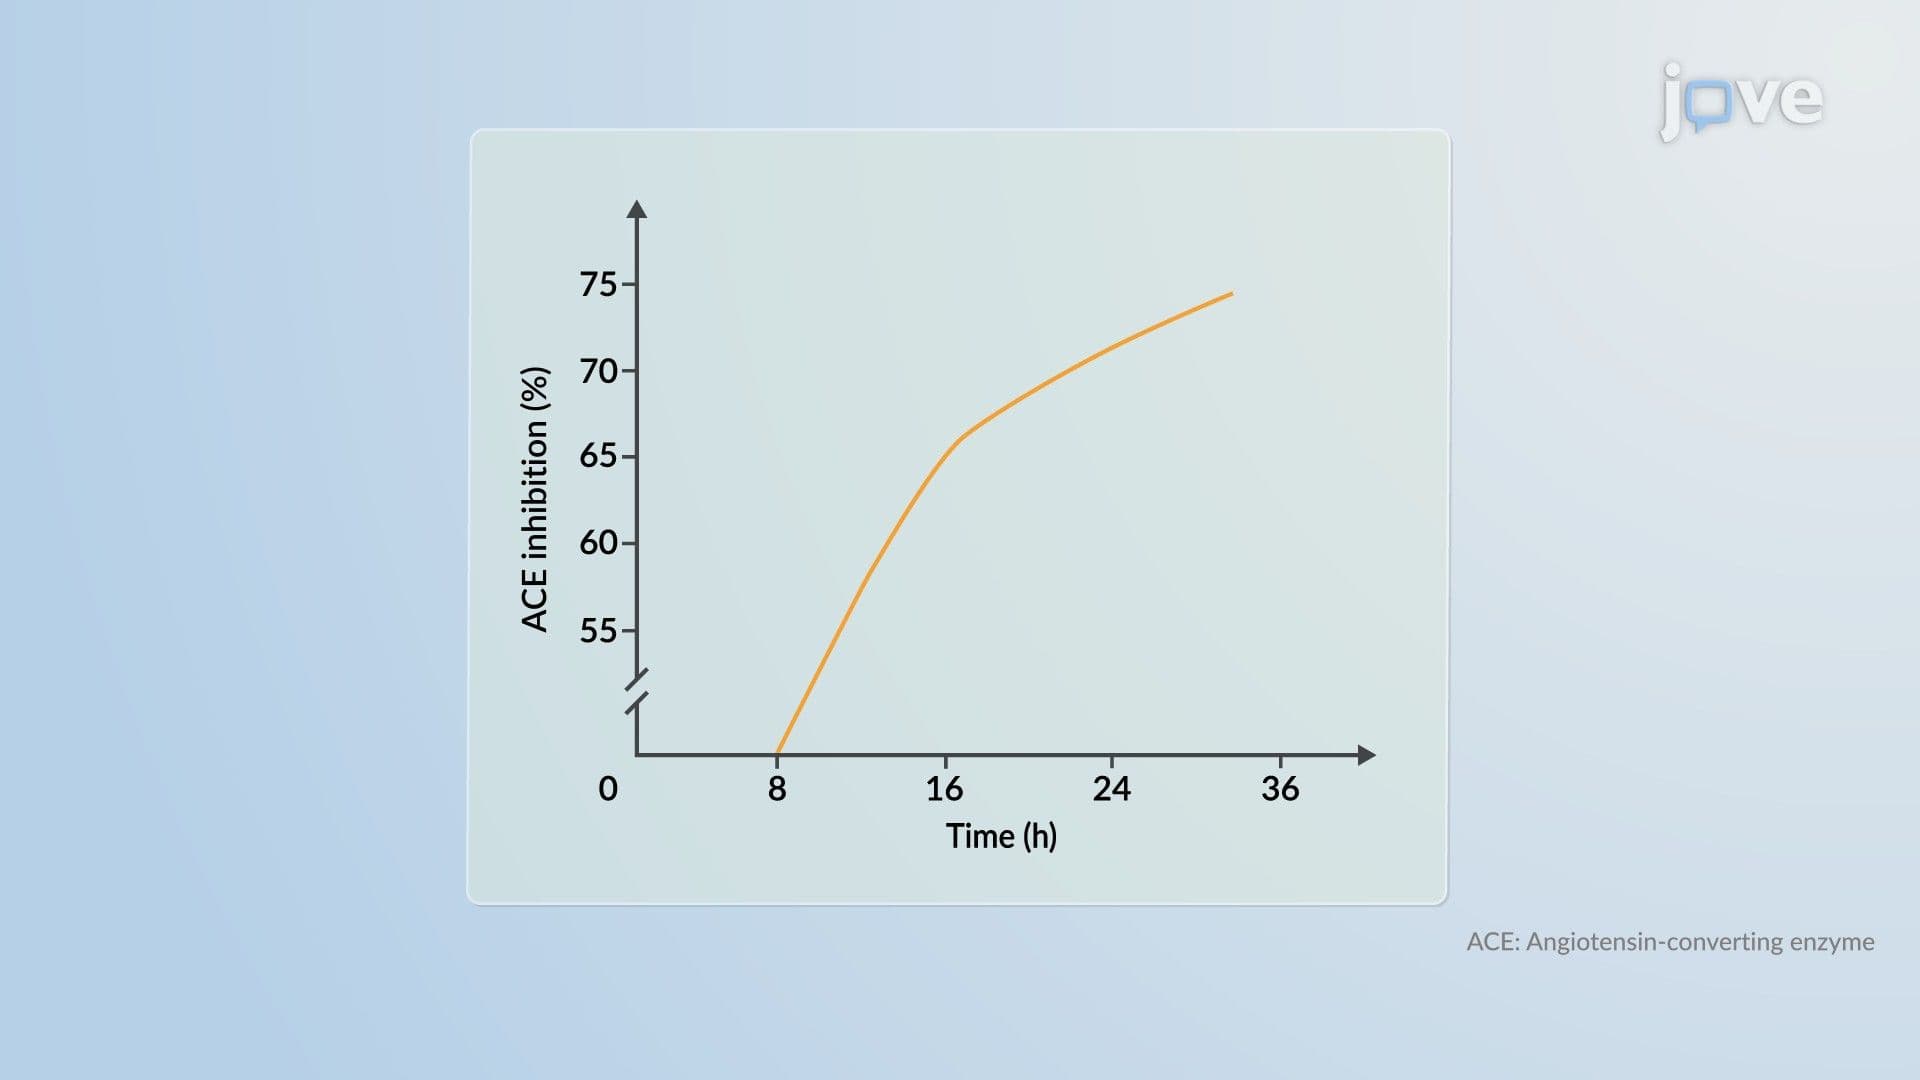
Pharmacokinetic–Pharmacodynamic Relationship: Exposure, Response and Effect
 01:03
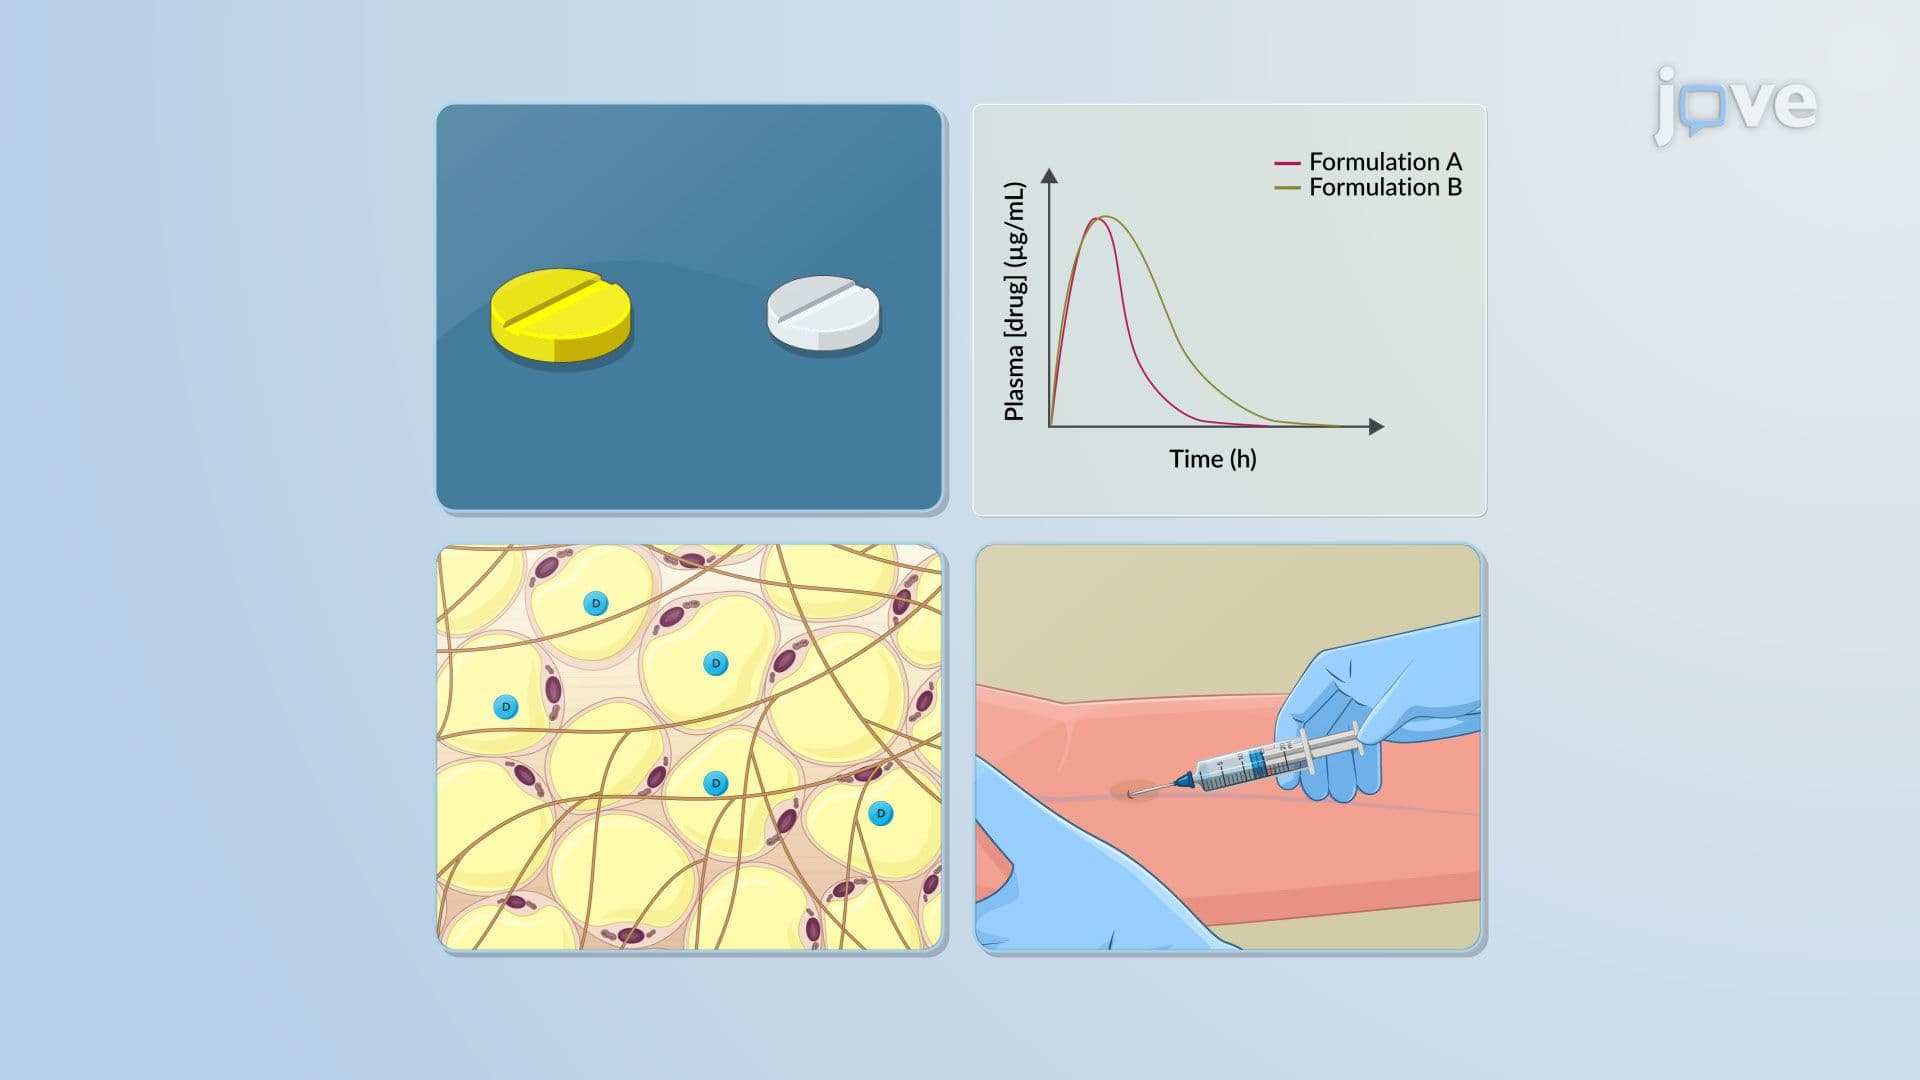
Dose-Response Relationship: Overview
 01:14
Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship