Related Experiment Videos
High-altitude cerebral edema and high-altitude pulmonary edema in a trekker with a decent ascent profile: a case
Suraj Bhatta1,2, Surya Prakash Joshi1,2,3, Suraj Shrestha1,2
1Himalayan Rescue Association, Kathmandu, Nepal.

Introduction And Importance:
High-altitude illness (HAI) comprises a spectrum of disorders, including acute mountain sickness (AMS), high-altitude pulmonary edema (HAPE), and high-altitude cerebral edema (HACE). Although gradual ascent is the most effective preventive strategy, severe complications such as HAPE and HACE can still occur in susceptible individuals despite recommended ascent profiles.
Case Presentation:
A 31-year-old male trekker in the Manang Valley (3350 m) developed HAPE and HACE despite gradual ascent and 6 days of acclimatization. He presented with severe headache, nausea, and shortness of breath. Examination showed cyanosis, SpO2 39%, respiratory rate 35, bilateral lung crackles, and positive cerebellar signs. Prompt treatment with oxygen, dexamethasone, acetazolamide, and nifedipine led to improvement. He was airlifted to a lower altitude and fully recovered.
Clinical Discussion:
Despite a gradual ascent and absence of comorbidities, the patient developed concurrent HAPE and HACE, illustrating that severe illness can occur even in low-risk profiles. This underscores the role of individual susceptibility and highlights the importance of maintaining a high index of suspicion in all high-altitude trekkers.
Conclusion:
This case illustrates that even with proper acclimatization and ascent, severe forms of HAI, such as HAPE and HACE, can occur. It underscores the role of individual vulnerability, possibly influenced by genetic and environmental factors, in the pathogenesis of altitude illness. Prompt recognition and early intervention are essential to prevent fatal outcomes.
Related Concept Videos
 01:18
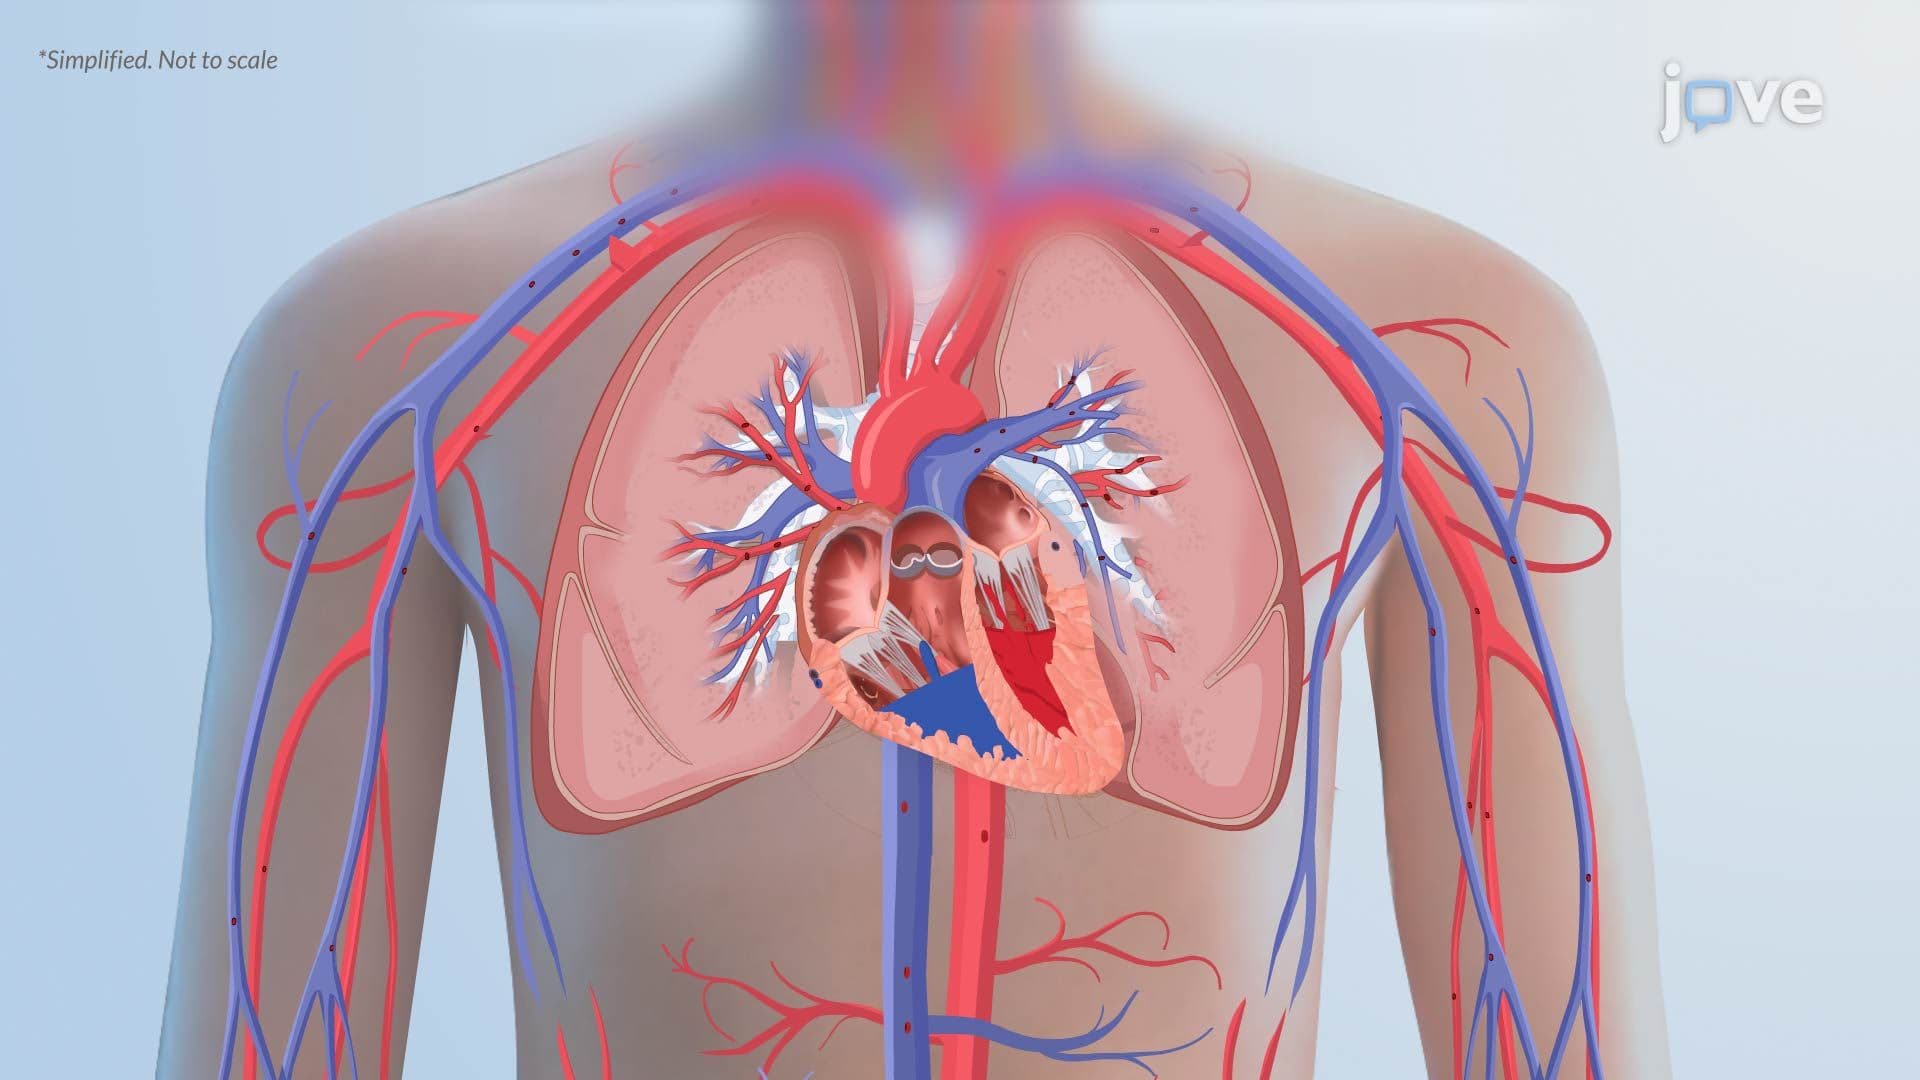
Pulmonary Edema II: Pathophysiology
 01:19
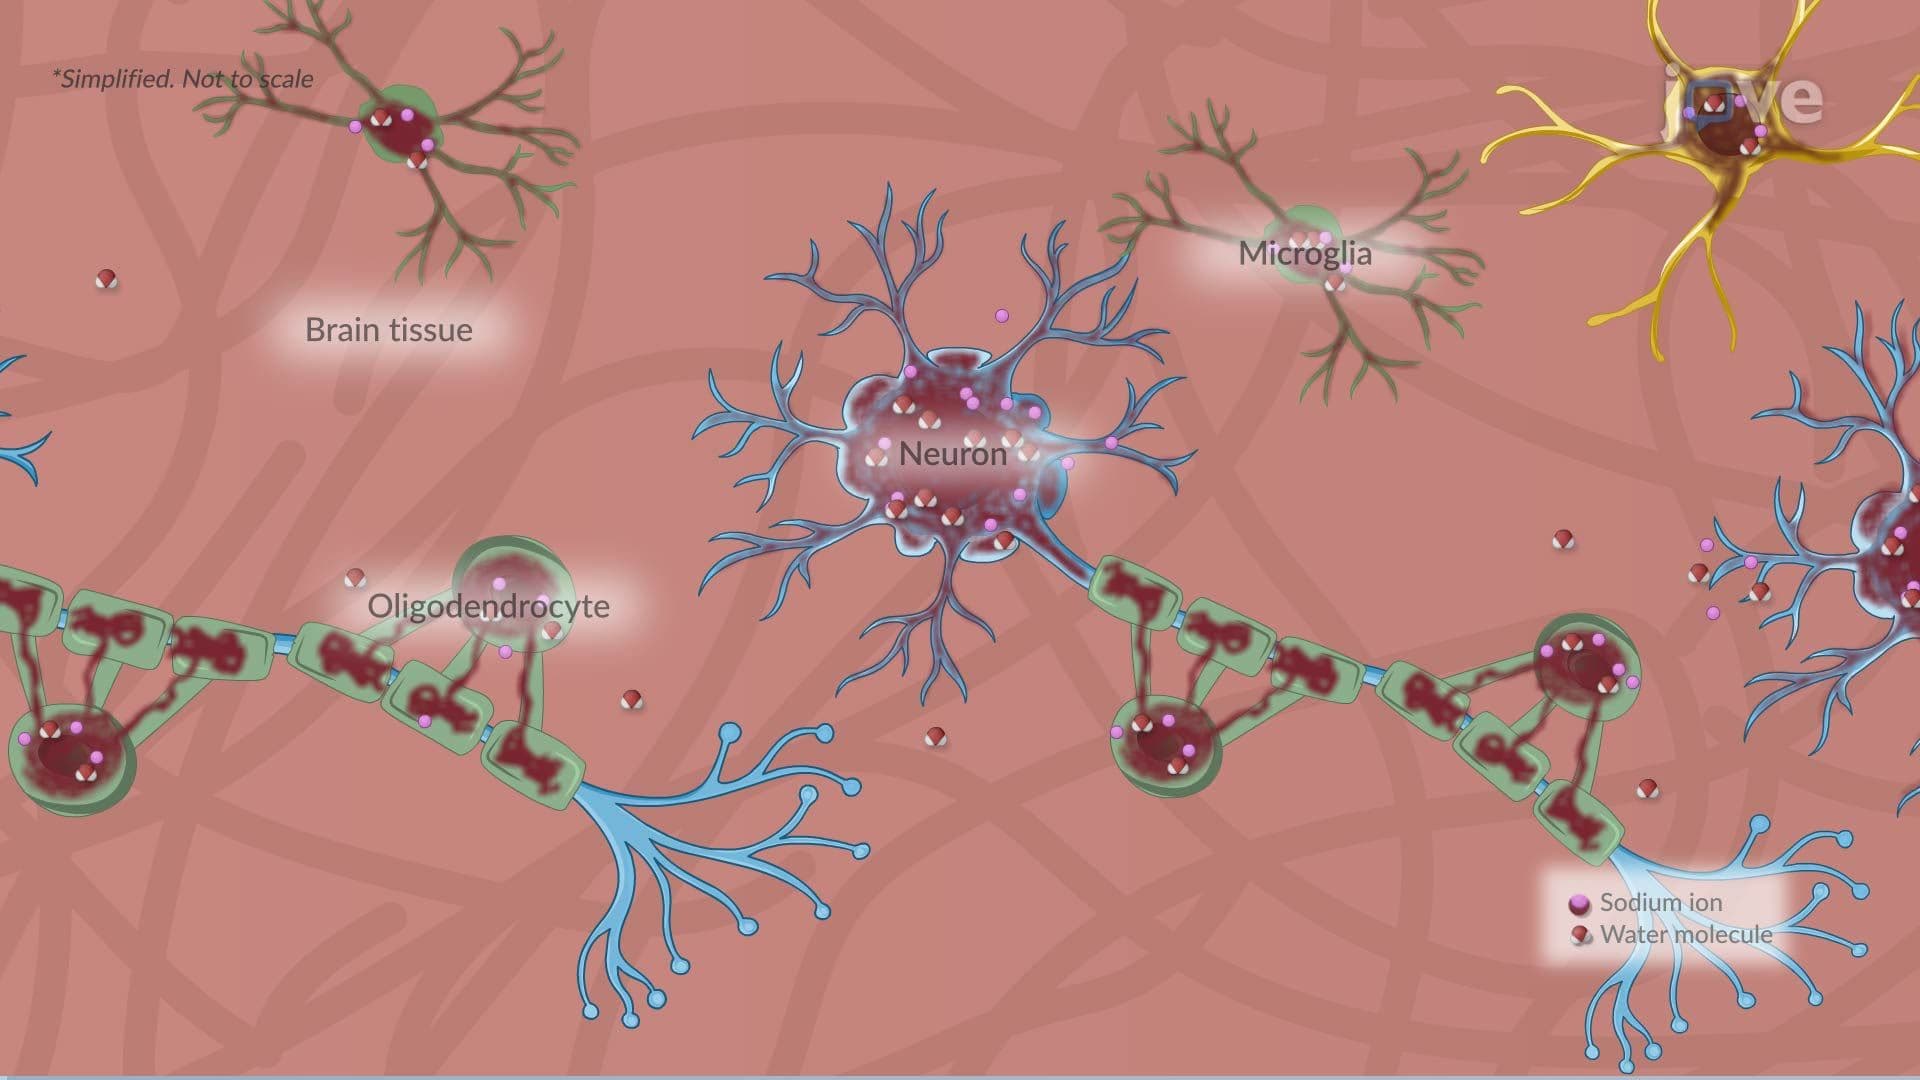
Cerebral Edema l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:14
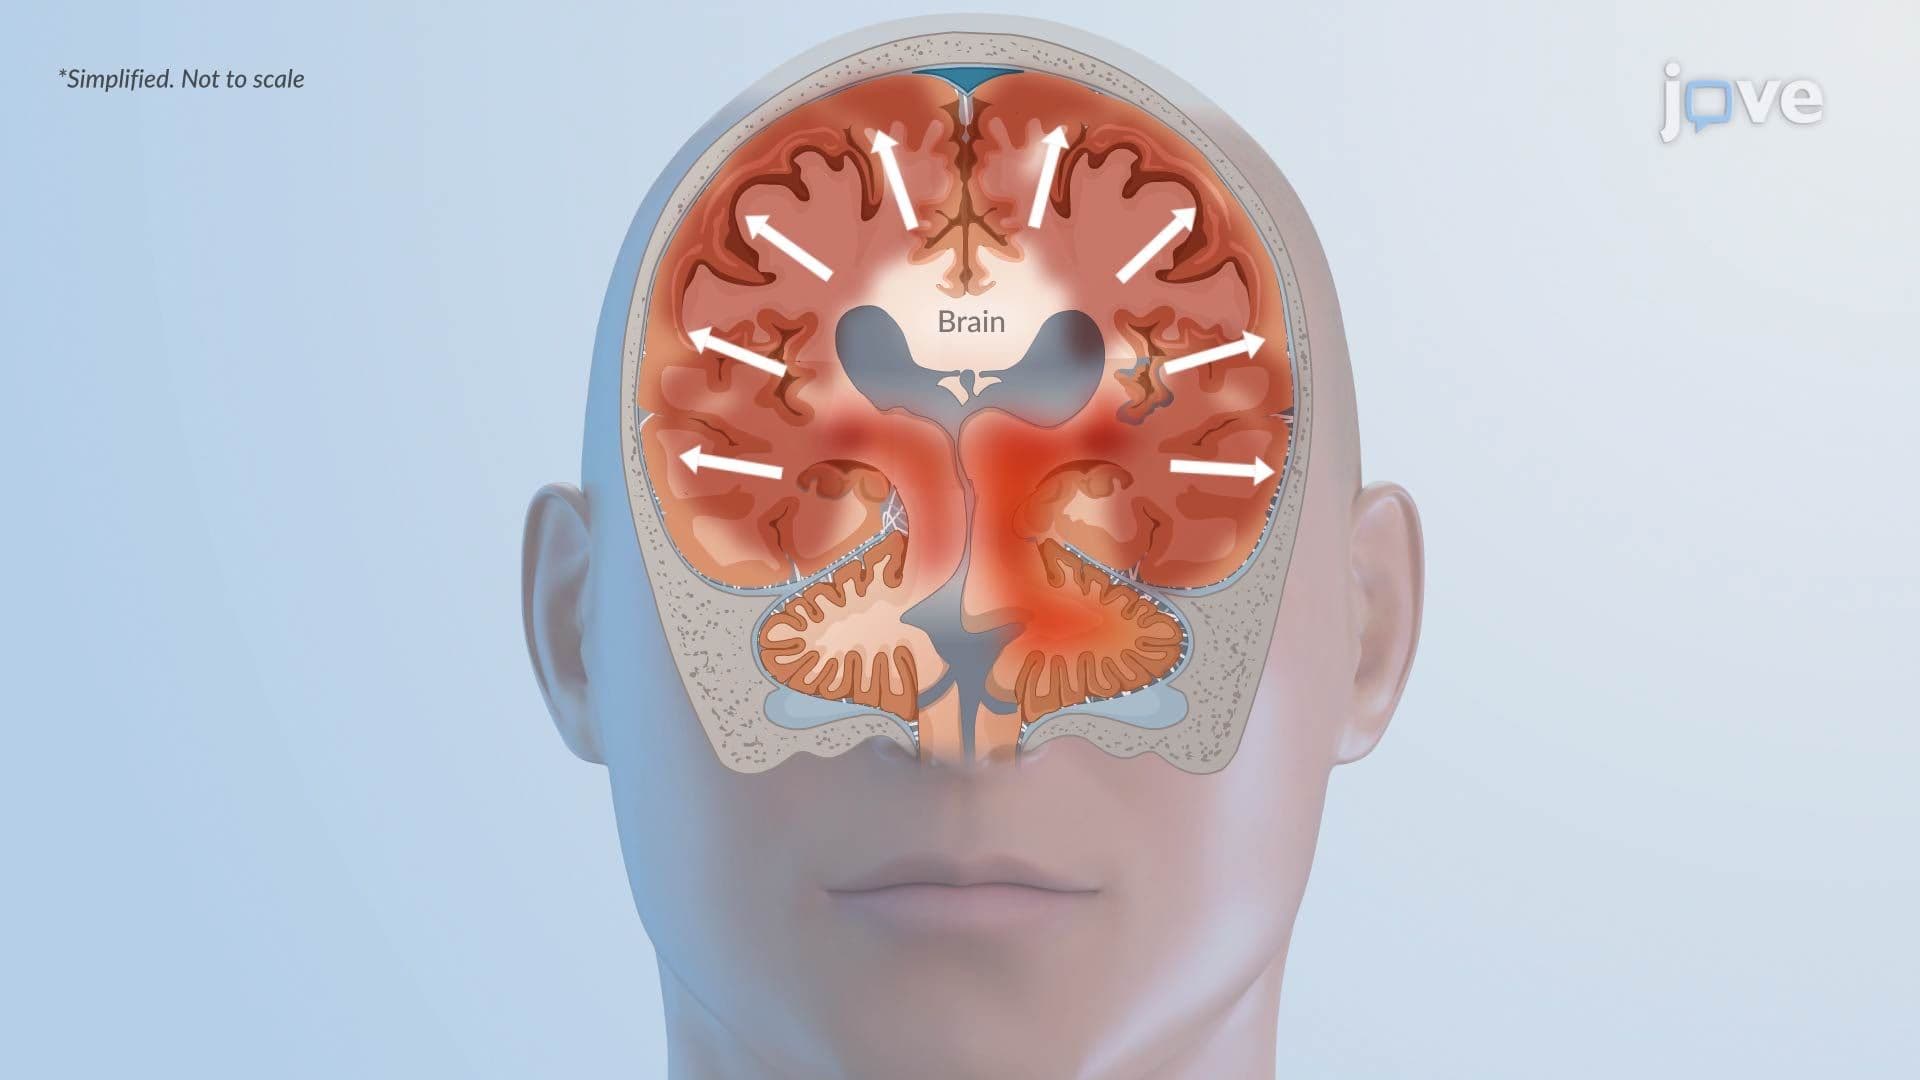
Increased Intracranial Pressure l: Introduction
 01:21
Cytotoxic Edema: Pathophysiology