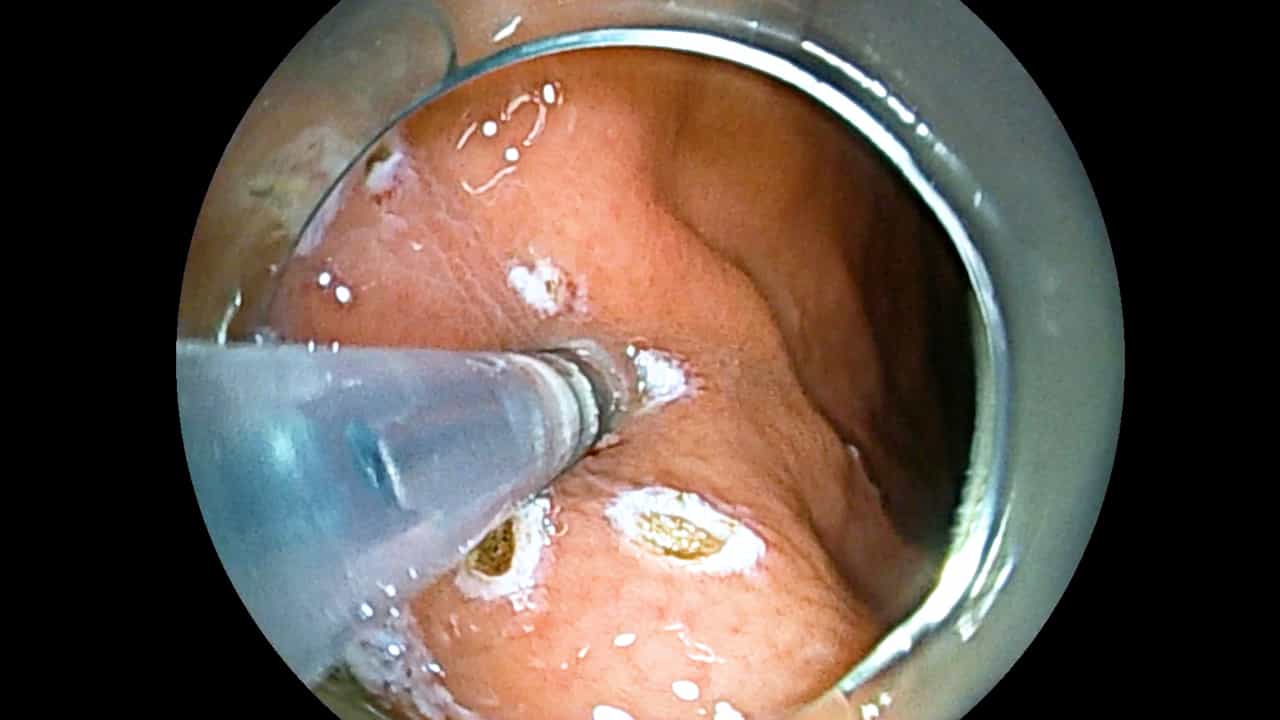
Related Experiment Video
Updated: Jun 9, 2026


Structured Approach to Colonoscopy Technique Optimization: A Single-Center Experience with Novice Endoscopists
Published on: July 11, 2025
Long-term effectiveness of endoscopic and stool-based colorectal cancer screening strategies: a systematic review and
Motoki Kaneko1, Atsushi Sakuraba2
1Division of Digestive Diseases and Nutrition, Department of Internal Medicine, RUSH University Medical Center, Chicago, IL, USA.

Background:
The population impact of colorectal cancer (CRC) screening depends on test performance and uptake, yet the comparative effectiveness of colonoscopy (CS), flexible sigmoidoscopy (FS), fecal immunochemical test (FIT), and guaiac-based fecal occult blood test (gFOBT) remains uncertain.
Objectives:
To compare the 10-year effects of CS, FS, FIT, and gFOBT on CRC incidence, CRC mortality, and all-cause mortality.
Design:
A systematic review and network meta-analysis.
Data Sources And Methods:
We searched PubMed, EMBASE, and Cochrane CENTRAL from inception to June 13, 2025, for randomized controlled trials enrolling average-risk adults comparing CS, FS, FIT, or gFOBT with no screening (NS) or each other. Risk ratios (RRs) with 95% confidence intervals (CI) were synthesized using a frequentist random-effects model. Intention-to-treat (ITT) analyses estimated invitation-based population effectiveness, with exploratory per-protocol (PP) analyses serving as a complementary assessment for screening completers (high risk of bias and very low certainty). The sparse network lacked closed loops, precluding formal inconsistency assessment.
Results:
In ITT analyses, CS (RR 0.83, 95% CI 0.72-0.96) and FS (0.78, 0.74-0.83), but not FIT (limited evidence) or gFOBT, reduced CRC incidence versus NS. For CRC mortality, FS (0.74, 0.67-0.83) and gFOBT (0.87, 0.79-0.95), but not CS or FIT, reduced risk. No strategy reduced all-cause mortality. In exploratory PP analyses, CS (0.78, 0.62-0.99) and FS (0.72, 0.66-0.79) reduced CRC incidence. For CRC mortality, CS (0.52, 0.31-0.85), FS (0.58, 0.49-0.70), and gFOBT (0.71, 0.61-0.82) reduced risk.
Conclusion:
CS reduced CRC incidence in ITT analyses but showed limited population-level effectiveness when uptake was low. FS reduced CRC incidence and mortality in ITT analyses, and gFOBT reduced CRC mortality. Screening strategies should be selected based on test characteristics, real-world participation, and healthcare capacity. PP findings were exploratory and should not be used in isolation to guide recommendations.
Trial Registration:
PROSPERO registration number CRD420251127511.