Related Experiment Video
Updated: Jun 9, 2026
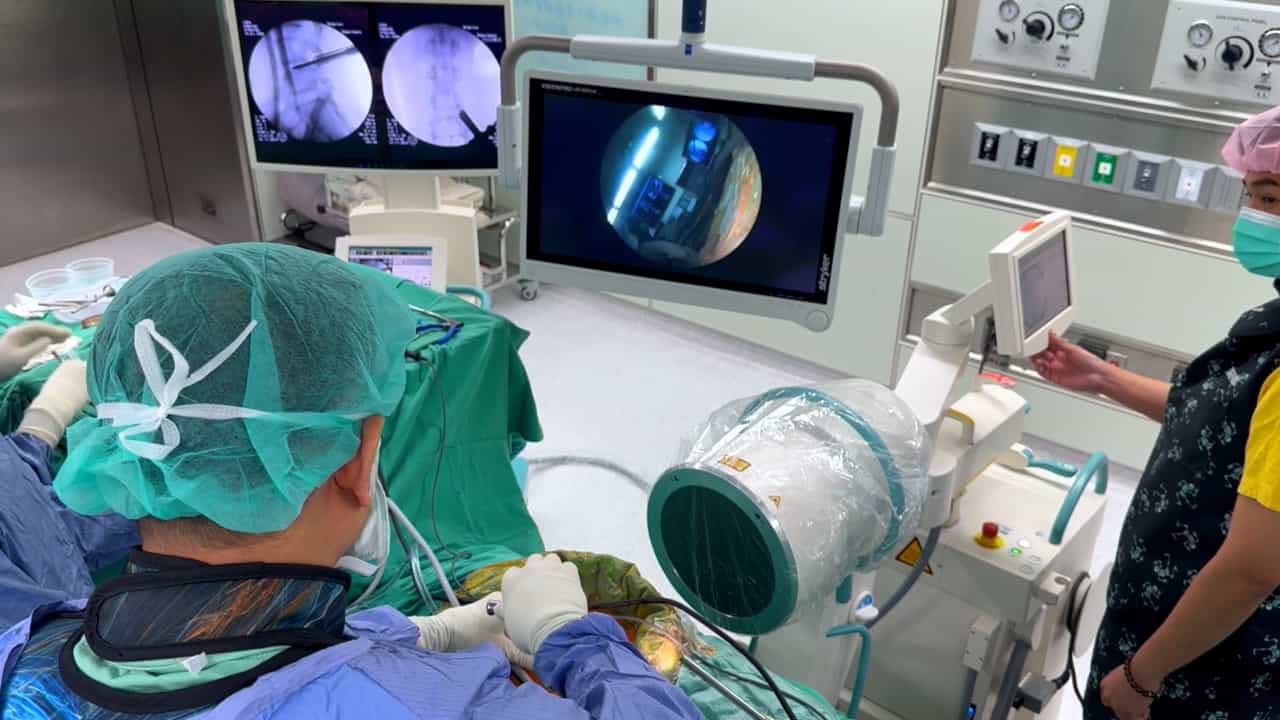

Uniportal Full Endoscopic Posterolateral Transforaminal Lumbar Interbody Fusion
Published on: June 6, 2025
Post-traumatic Exacerbation of Grade II L5-S1 Spondylolisthesis Requiring Surgical Stabilization
Elizabeth Blanco Espinosa1,2, Idania Cruzata Matos3, Yelka Matos Furones4
1Neurosurgery/General Surgery, Arnaldo Milián Castro Provincial University Hospital, Santa Clara, CUB.

Abstract:
Spondylolisthesis is characterized by the forward movement of one vertebra over the one beneath it, most frequently occurring at the L5-S1 level due to its biomechanical susceptibility. Although often asymptomatic, it may become clinically significant when underlying instability is exacerbated by external factors. Low-energy trauma can unmask previously undiagnosed spondylolisthesis, resulting in acute pain, neurological symptoms, and functional impairment. We report the case of a 51-year-old woman with a history of hypertension treated with atenolol, with no prior medically documented history of chronic low back pain or spinal pathology (noting that this information was obtained retrospectively from patient history after resolution of acute intoxication). She presented with severe low back pain following a fall from standing height while under the influence of alcohol. The pain was progressive, refractory to analgesia, with a reported intensity of 9/10 on the Visual Analog Scale (VAS), and associated with paresthesia and impaired ambulation. No standardized functional outcome scores were available pre- or post-operatively, which limits functional outcome comparison. Imaging studies, including magnetic resonance imaging (MRI), revealed Grade II L5-S1 spondylolisthesis with degenerative disc changes, canal narrowing, and suspected neural compression, without evidence of acute fracture. Computed tomography (CT) was not available at presentation for independent review, and prior external imaging reports were not retrievable. Given persistent symptoms after failed conservative management and clinical evidence of neurological progression, the patient underwent posterior lumbar stabilization with pedicle screw instrumentation at L5-S1. The procedure performed was posterior instrumented fusion with pedicle screw fixation and posterolateral arthrodesis. The postoperative course was uneventful, with improvement in pain and mobility and resolution of sensory symptoms. The VAS score improved from 9/10 preoperatively to 2/10 at the six-week follow-up. The patient was discharged on postoperative day 3 and showed continued improvement at six months. This case highlights that low-energy trauma may reveal previously asymptomatic spondylolisthesis. Early recognition, appropriate imaging, and timely surgical intervention are essential for optimal outcomes. Posterior instrumentation remains a reliable treatment option when tailored to clinical presentation. However, functional outcome measures and long-term radiographic fusion assessment were not available, limiting interpretation of definitive recovery.
