Related Experiment Video
Updated: Jun 9, 2026
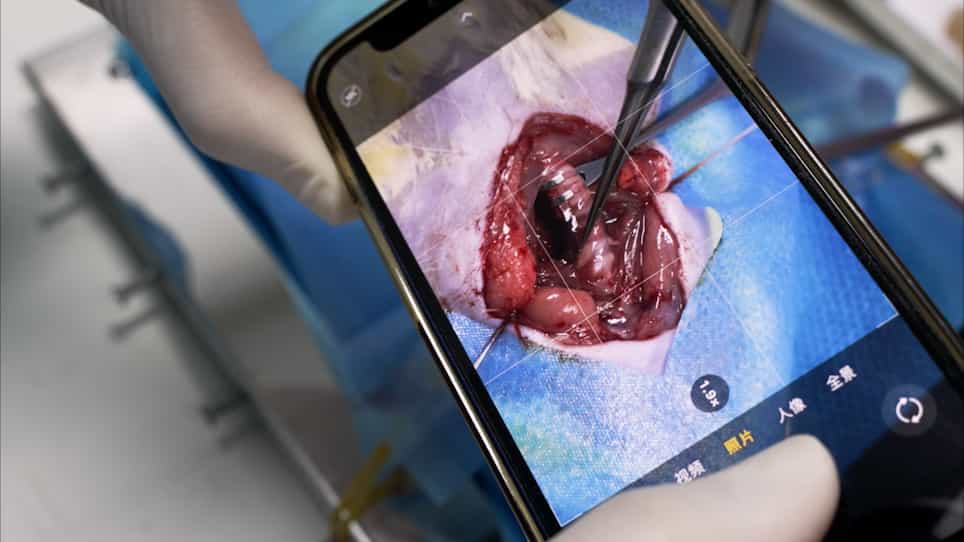
Establishment of a Simple and Effective Rat Model for Intraoperative Parathyroid Gland Imaging
Published on: August 17, 2022
Timing of Denosumab Therapy in Relation to Parathyroidectomy in the Setting of Primary Hyperparathyroidism: Case
Ryan S MacLeod1, Adriana Ramirez2, Barbara Gulanski1
1Department of Internal Medicine, Section of Endocrinology, Yale University School of Medicine, 333 Cedar Street, New Haven, 06510, Connecticut, USA, yale.edu.

Abstract:
The optimal timing of denosumab therapy in relation to parathyroid surgery to avoid hypocalcemia and rebound bone resorption is not well described. Herein we report the case of a 62-year-old woman with steroid-induced osteoporosis who received denosumab for several years prior to undergoing parathyroidectomy. She had a history of lupus and required 20-60 mg of daily prednisone. Prior to her presentation at our institution, she was initially treated with alendronate and calcium/vitamin D supplementation. A dual-energy X-ray absorptiometry (DXA) scan 4 years after starting prednisone showed stable osteopenia in the lumbar spine and total hip but osteoporosis in the femoral neck with a significant reduction of bone mineral density (BMD) by 15.4% since baseline. Denosumab was initiated by her local endocrinologist for antiresorptive therapy due to declining bone density while on alendronate. She remained on prednisone for three additional years while on denosumab. 3 years of denosumab therapy resulted in stable bone density. Vitamin D levels were appropriate but elevations in PTH and calcium were noted. What was initially thought to be secondary hyperparathyroidism was at this point consistent with primary hyperparathyroidism (PHPT). A 4-dimensional computed tomography (4D CT) scan of the neck identified a parathyroid adenoma, and she was referred to our institution for parathyroidectomy. The timing of parathyroidectomy in relationship to the next denosumab injection was a concern due to the rebound bone resorption phenomenon and increased risk of vertebral fractures if denosumab is delayed or missed. Conversely, if denosumab is given in the periprocedural period, severe postsurgical hypocalcemia can result if denosumab prevents liberation of calcium from bone. Considering this, parathyroidectomy was performed 6 months after the last denosumab dose, and it was resumed 8 weeks after surgery. 1 month after surgery, calcium was normal, and PTH had recovered to mid-normal range. Her postoperative course was uncomplicated, and she was able to resume denosumab.
Related Concept Videos
 00:59
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:40
Bone Remodeling
 01:21
Skeleton and Calcium Homeostasis