Related Experiment Video
Updated: Jun 10, 2026
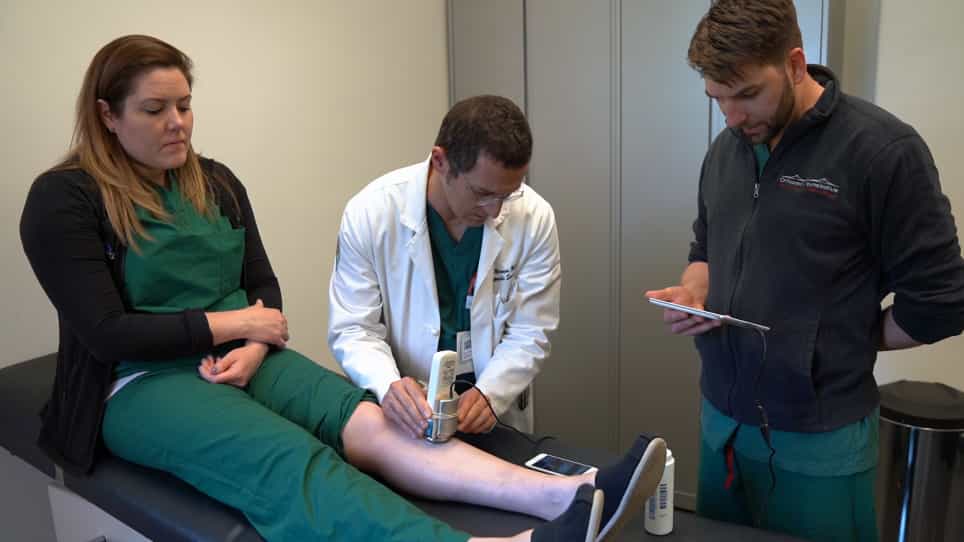

A Novel Non-invasive Method for the Detection of Elevated Intra-compartmental Pressures of the Leg
Published on: May 31, 2019
Phlegmasia Cerulea Dolens With Compartment Syndrome
Aryan Shiari1, Ryan Bailey2, Jason Beckerman3
1Pulmonary, Critical Care, and Sleep Medicine, Mayo Clinic Health System - Northwest Wisconsin Region, Eau Claire, Wisconsin, shiari.aryan@mayo.edu.

Insights
Phlegmasia cerulea dolens (PCD), a severe deep vein thrombosis, can lead to critical limb ischemia. Prompt diagnosis and intervention are crucial to prevent limb loss, especially when complicated by underlying malignancy.
Area of Science:
- Vascular Surgery
- Hematology
- Emergency Medicine
Background:
- Phlegmasia cerulea dolens (PCD) is a rare, severe form of deep vein thrombosis (DVT).
- PCD involves extensive venous thrombosis and congestion, causing limb swelling, cyanosis, and pain.
- It leads to secondary arterial compromise and critical limb ischemia, posing an emergency.
Introduction:
Phlegmasia cerulea dolens (PCD) is a rare, severe form of deep vein thrombosis (DVT) characterized by extensive venous thrombosis and significant venous congestion, leading to swelling, cyanosis, and severe pain. Unlike typical DVT, PCD causes secondary arterial compromise via small arteriole collapse, resulting in critical limb ischemia and potential venous gangrene. This compromise, coupled with increased compartment pressures and fluid sequestration, makes PCD a true emergency requiring immediate intervention to prevent irreversible damage and limb loss.
Case Presentation:
A 58-year-old woman with a complex medical history presented with severe left hip and lumbar pain following trauma. Examination revealed a swollen, cold, cyanotic, and painful left leg with weak pulses indicating compromised blood flow. Computed tomography confirmed extensive DVT from the left common iliac to the tibial veins, consistent with PCD and concerning for compartment syndrome. Given the critical presentation, fasciotomy was performed without obtaining compartment pressure measurements. The patient received anticoagulation and underwent inferior vena cava filter placement, attempted thrombectomy, and subsequent fasciotomy. Despite these measures, persistent ischemia necessitated a left above-the-knee amputation. Incidental cholangiocarcinoma was subsequently diagnosed, likely contributing to her thrombotic condition.
Conclusions:
This case highlights the need for prompt diagnosis and intervention in PCD and its progression to compartment syndrome. Underlying malignancy can complicate the clinical course, necessitating a multidisciplinary approach to care. Immediate anticoagulation, thrombus removal, and supportive measures are essential in preventing further complications and improving outcomes.

Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Varicose Veins I: Introduction
 01:30
Peripheral Artery Disease I: Introduction