Related Experiment Video
Updated: Jun 10, 2026
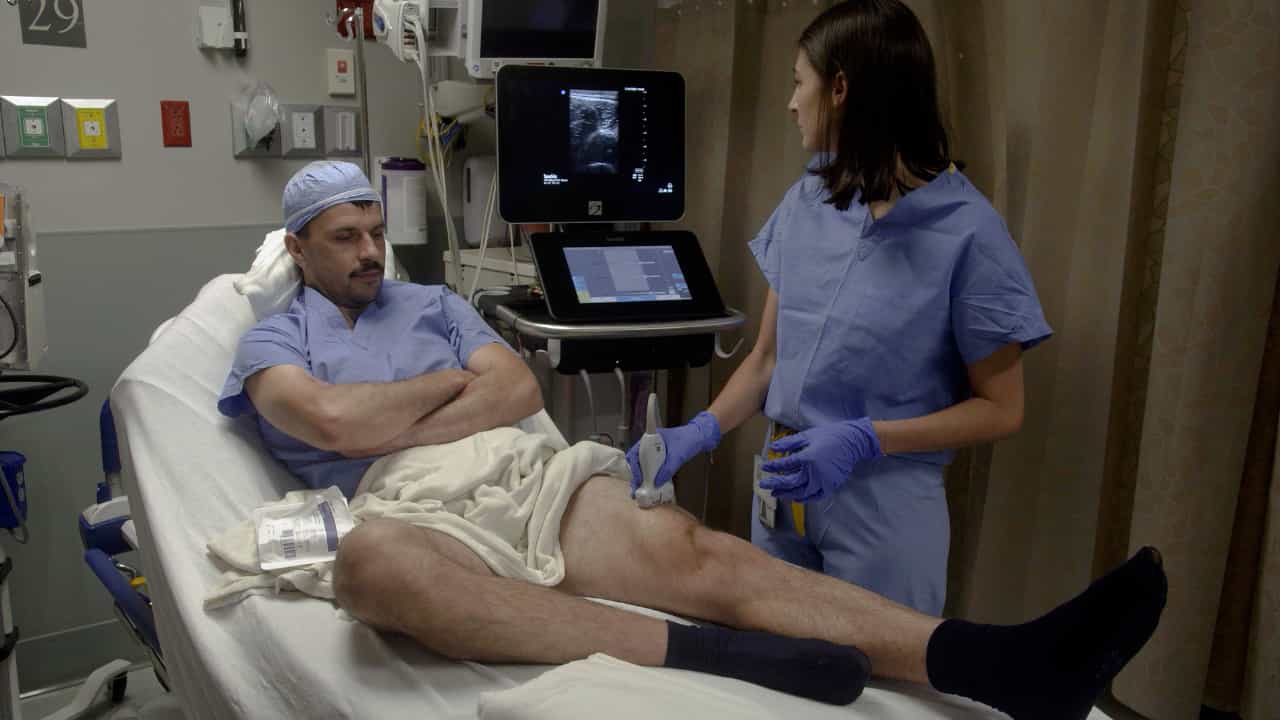

Identifying Frailty Using Point-of-Care Ultrasonography: Image Acquisition and Assessment
Published on: July 26, 2024
Frailty Status and Preoperative Cardiac Risk Stratification in Older Adults Undergoing Noncardiac Surgery: A
Athanasia Chatziperi1,2,3, Calvin Diep2, Julian F Daza4
1Department of Anesthesia St. Michael's Hospital-Unity Health Toronto Toronto Ontario Canada.

Background:
Frailty is prevalent among older adults and associated with increased postoperative morbidity and death. Guidelines recommend consideration of frailty to inform preoperative cardiac risk stratification. However, its incremental prognostic value beyond established tools including clinical indices, functional capacity, and biomarkers is uncertain.
Methods:
We conducted a secondary analysis of a multicenter prospective cohort study involving older adults (aged ≥65 years) undergoing major elective noncardiac surgery. Frailty was assessed using the Clinical Frailty Scale. The primary outcome was 30-day major adverse cardiac events, defined as myocardial infarction, nonfatal cardiac arrest, or death. Multivariable logistic regression evaluated the association between frailty (Clinical Frailty Scale ≥4) and major adverse cardiac events, adjusting for age, sex, Revised Cardiac Risk Index, Duke Activity Status Index, and natriuretic peptide concentration. Incremental prognostic value was assessed using the likelihood ratio test, concordance index, fraction of new predictive information, and decision curves.
Results:
Among 1939 participants (median age, 72 years; 42% women), 43% had frailty, and 4.9% experienced 30-day major adverse cardiac events. The Duke Activity Status Index and the Clinical Frailty Scale were strongly correlated (R=-0.64). Frailty was associated with major adverse cardiac events after adjustment for age, sex, and Revised Cardiac Risk Index (odds ratio, 1.62 [95% CI, 1.05-2.51]) but not after further adjustment for Duke Activity Status Index or natriuretic peptide concentrations. Frailty improved prediction beyond clinical factors alone but not when functional capacity or biomarkers were included.
Conclusions:
Frailty was associated with increased cardiac risk and improved prediction beyond clinical factors, but its incremental prognostic value diminished when functional capacity or biomarkers were available, supporting its selective use when these measures are unavailable.

Related Concept Videos
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:00
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Distribution
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Metabolism
 01:15
Drug Dosing: Geriatric Patients