Related Experiment Video
Updated: Jun 10, 2026
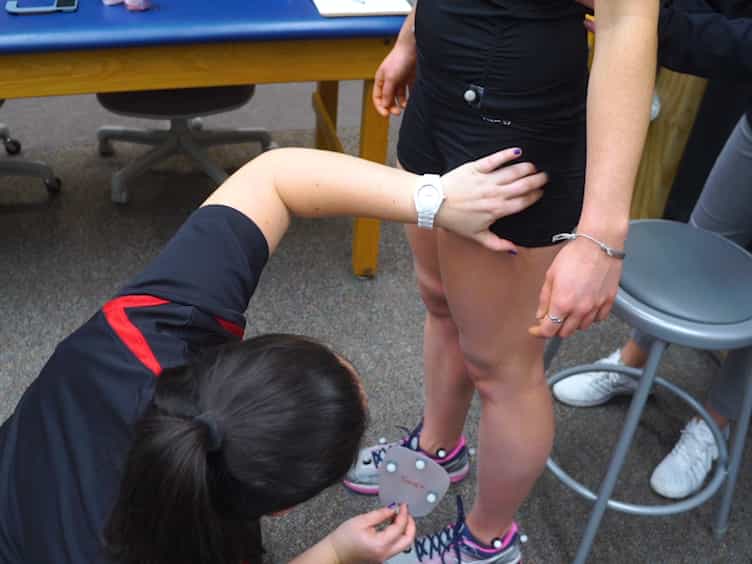

Subject-specific Musculoskeletal Model for Studying Bone Strain During Dynamic Motion
Published on: April 11, 2018
Stress Fractures in a U.S. Military Population by Duration of Active Duty-A Retrospective, Sex-Stratified
Andrew J Spiro1, Gregory S Schmidt1, James H Prim1
1Department of Endocrinology, Walter Reed National Military Medical Center, Bethesda, MD 20889, United States.

Introduction:
Stress fractures affect military personnel at higher rates than the general population. They can lead to serious injury and negatively impact military force readiness. Most prior studies have focused on recruits undergoing basic training. Our goal was to characterize stress fractures over the full spectrum of military career stages to identify whether fracture locations varied by career length.
Materials And Methods:
A retrospective chart review was conducted of a 3-year period (January 1, 2017-December 31, 2019) to identify active duty military patients in the National Capital Region diagnosed with a new stress fracture. Patients were stratified by career length: New Recruit (<12 months of service), Early-Career (1-5 years of service), Mid-Career (5-14 years of service), and Late-Career (>14 years of service). The percentage of fractures at each anatomic location was reported and compared by binary career length (New Recruit vs. others) with Chi-square or Fisher's exact tests performed among the full cohort. The total cohort was stratified by sex, and the analysis was repeated separately in males and females. The percentage of patients who presented with multiple fractures was similarly reported and compared by career length, among the full cohort and by sex strata. The study was approved by the Walter Reed National Military Medical Center Institutional Review Board, protocol # WRNMMC-2018-0162.
Results:
The study population included 446 military members with 537 total fractures. Percentages of femoral neck (11.1% vs. 3.6%, P = .001), femoral shaft (8.1% vs. 1.8%, P = .001) and pelvis fractures (3.8% vs. 0.7%, P = .031) were greater in the New Recruit group compared to the other career-length groups. Percentage of foot fractures was lower (19.2% vs. 34.3%, P < .001) in the New Recruit group vs. the other career-length groups. Percentage of patients presenting with multiple stress fractures (23.7% vs. 10.1%, P < .001) was greater in the New Recruit group vs. the other career-length groups. The significant differences in femoral shaft and foot fractures persisted when males and females were analyzed separately.
Conclusions:
Our findings support that the distribution of the anatomic locations of stress fractures differs between military members in the New Recruit period versus later in their careers. Specifically, New Recruits had a higher percentage of femoral neck, femoral shaft, and pelvic fractures. Providers may consider having a lower threshold for imaging new recruits with hip pain as this could identify a stress reaction before it becomes a stress fracture. Potential explanations for the findings include sex, training intensity, and force attrition. Some of the significant findings persisted when males and females were analyzed separately, which supports that there are contributions from other factors than patient's sex. Additional studies are needed to build upon these findings. Limitations included the use of ICD-10 codes and physician reporting to identify stress fractures, the lower numbers of patients once the total study population was stratified by sex, unavailability of bone density data, and unclear generalizability of the findings.
