Related Experiment Video
Updated: Jun 11, 2026
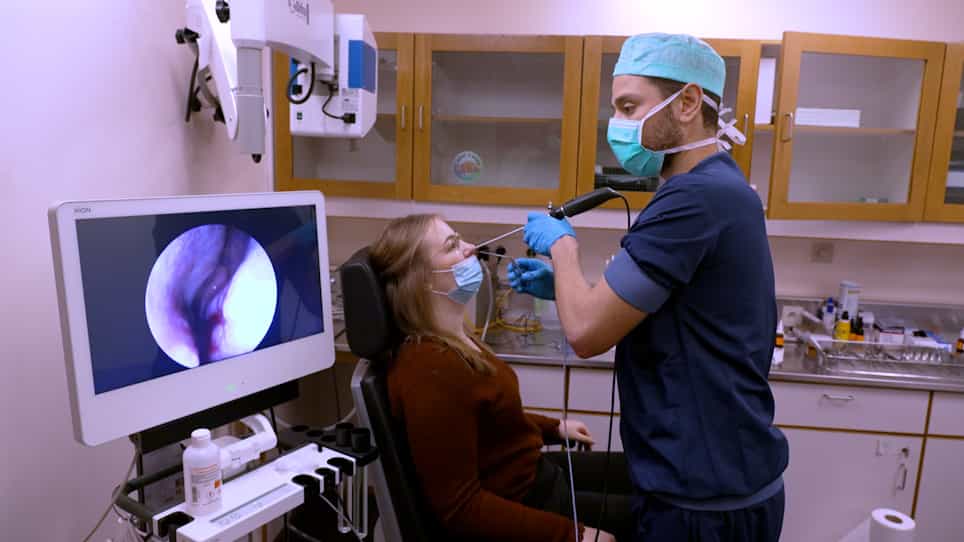

Nasal Brushing Sampling and Processing Using Digital High Speed Ciliary Videomicroscopy – Adaptation for the COVID-19 Pandemic
Published on: November 7, 2020
Unique and shared patterns of chemosensory dysfunction distinguish chronic COVID-19 and aspirin-exacerbated
Dante G Minichetti1, Tiffany Dharia1, Amelia Boyd1
1Division of Allergy and Clinical Immunology, Jeff and Penny Vinik Center for Allergic Disease Research, Brigham and Women's Hospital, Boston, Massachusetts; Department of Medicine, Harvard Medical School, Boston, Massachusetts.

Background:
Persistent chemosensory dysfunction (CSD) occurs in both COVID‑19 and aspirin-exacerbated respiratory disease (AERD). The similarities and differences in the chemosensory experiences of these 2 conditions remain undefined and poorly understood.
Objective:
To compare qualitative and quantitative chemosensory alterations and quality-of-life impact in individuals with COVID-19-associated vs AERD-associated CSD.
Methods:
Participants from the Brigham and Women's Hospital COVID-19 CSD registry (n = 406) and the Brigham and Women's Hospital AERD registry (n = 389) completed online questionnaires assessing CSD characteristics and sinonasal disease-related quality of life.
Results:
COVID‑19 CSD showed a distinct qualitative phenotype. Overall, 60% of COVID‑19 participants reported that odors smelled different from how they recalled them, vs 19% with AERD (P < .001). Unpleasant odor perception was experienced by more than 20% of COVID‑19 participants, but by less than 5% of AERD participants. COVID‑19 CSD involved selective impairment and unpleasant distortion of sour, bitter, and umami tastes, whereas AERD exhibited a uniform quantitative reduction across taste modalities. Flavor distortions, particularly for foods with bitter or fatty components (eg, coffee, chocolate, and nut butter) and chemesthetic flavors (eg, spicy, mint, alcohol, garlic, and ginger), were significantly more common in COVID‑19 CSD (average: 25%) than in AERD (average: 0%). Both conditions were associated with impaired quality of life, including odor and food safety-related concerns.
Conclusion:
Both COVID‑19 CSD and AERD cause profound chemosensory disruption. However, COVID‑19 CSD is distinguished by marked qualitative distortions in smell, taste, flavor, and chemesthesis. In contrast, AERD CSD reflects a more generalized sensory reduction. Incorporating these characteristic sensory profiles into routine evaluations may improve diagnostic accuracy and guide patient counseling for ongoing chemosensory care.
Related Concept Videos
 01:13
Asthma III: Clinical Manifestations
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:30
Toxidromes: Clinical Features
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations