Approach to the Preoperative Pharmacological Management of Catecholamine-Secreting Tumors in Children: A Case Series and Review
Related Experiment Video
Updated: Jun 11, 2026

Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
Olivia Dollimer1, Mike Raschka1, David Dassenko2
1Department of Pharmacy (MR, OD), Children's Minnesota, Minneapolis, MN.

Abstract:
Catecholamine-secreting tumors (CSTs) are an uncommon tumor in pediatrics that can result in hypertensive crisis secondary to catecholamine release from the tumor cells. Pheochromocytoma is the tumor type most associated with excessive catecholamine release, but paragangliomas and neuroblastoma tumors can also generate and release excessive amounts of catecholamines. Surgical resection is typically the treatment of choice for these tumor types; however, manipulation during surgical resection can lead to further catecholamine release. If the patient's adrenergic receptors are not fully inhibited before undergoing surgery, the patient is at risk for experiencing additional hypertensive crises and arrhythmias due to the catecholamine release secondary to the surgery. Although studies have identified sequential α- and β-adrenergic blockade as a prerequisite for surgery to minimize the effects of further catecholamine release during resection, there is little guidance regarding medication timing, dosing, and testing to ensure the pediatric patient has adequately suppressed adrenergic receptors before surgery. Further, with recent shortages of the first-line medication treatment options for this indication, it is vital to establish a treatment plan with alternative treatments for use during drug shortages. This case series describes the successful use of enteral phenoxybenzamine and parenteral phentolamine for α-adrenergic blockade, coupled with enteral atenolol and parenteral esmolol or labetalol for β-adrenergic blockade, in 9 pediatric patients with CST before surgical resection of the tumors. Eight patients underwent a phenylephrine challenge, and all demonstrated appropriate α-blockade preceding tumor removal.

Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:30
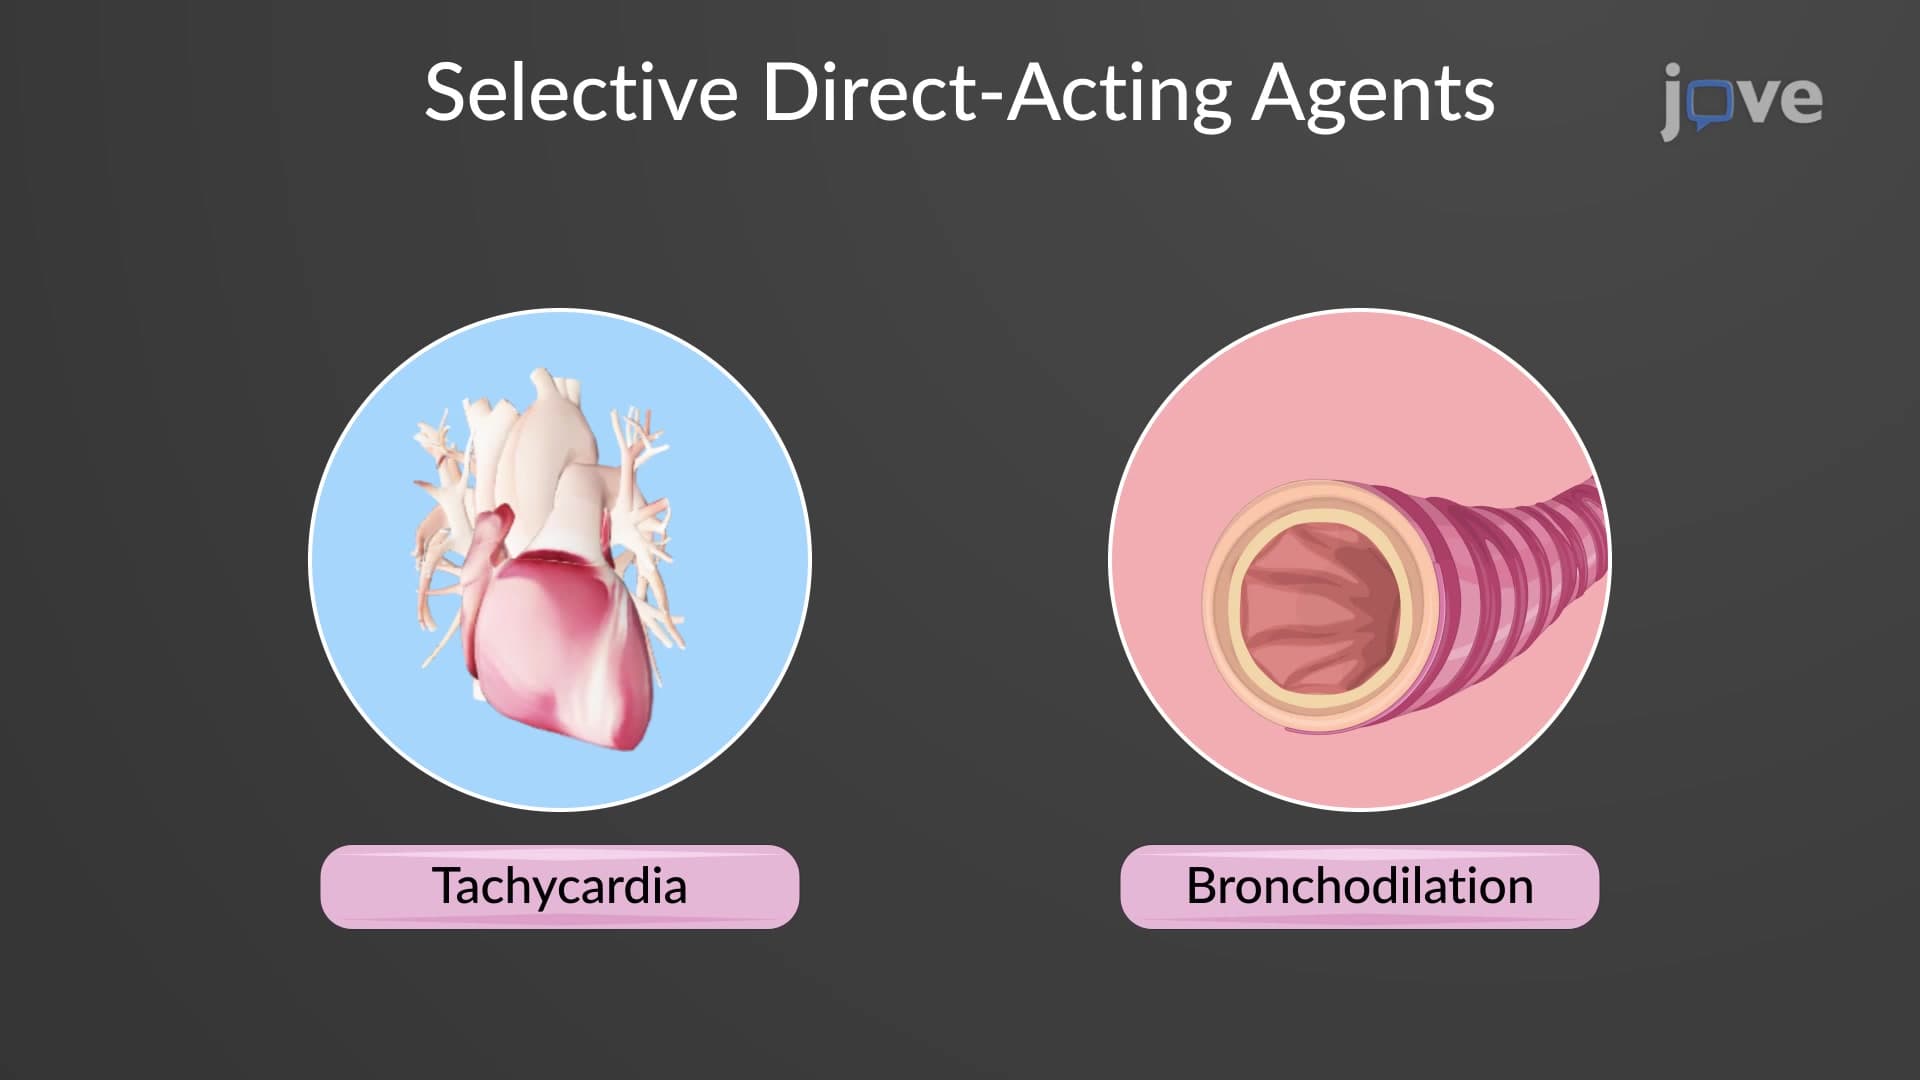
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:21
Drugs Affecting Neurotransmitter Release or Uptake
 01:25
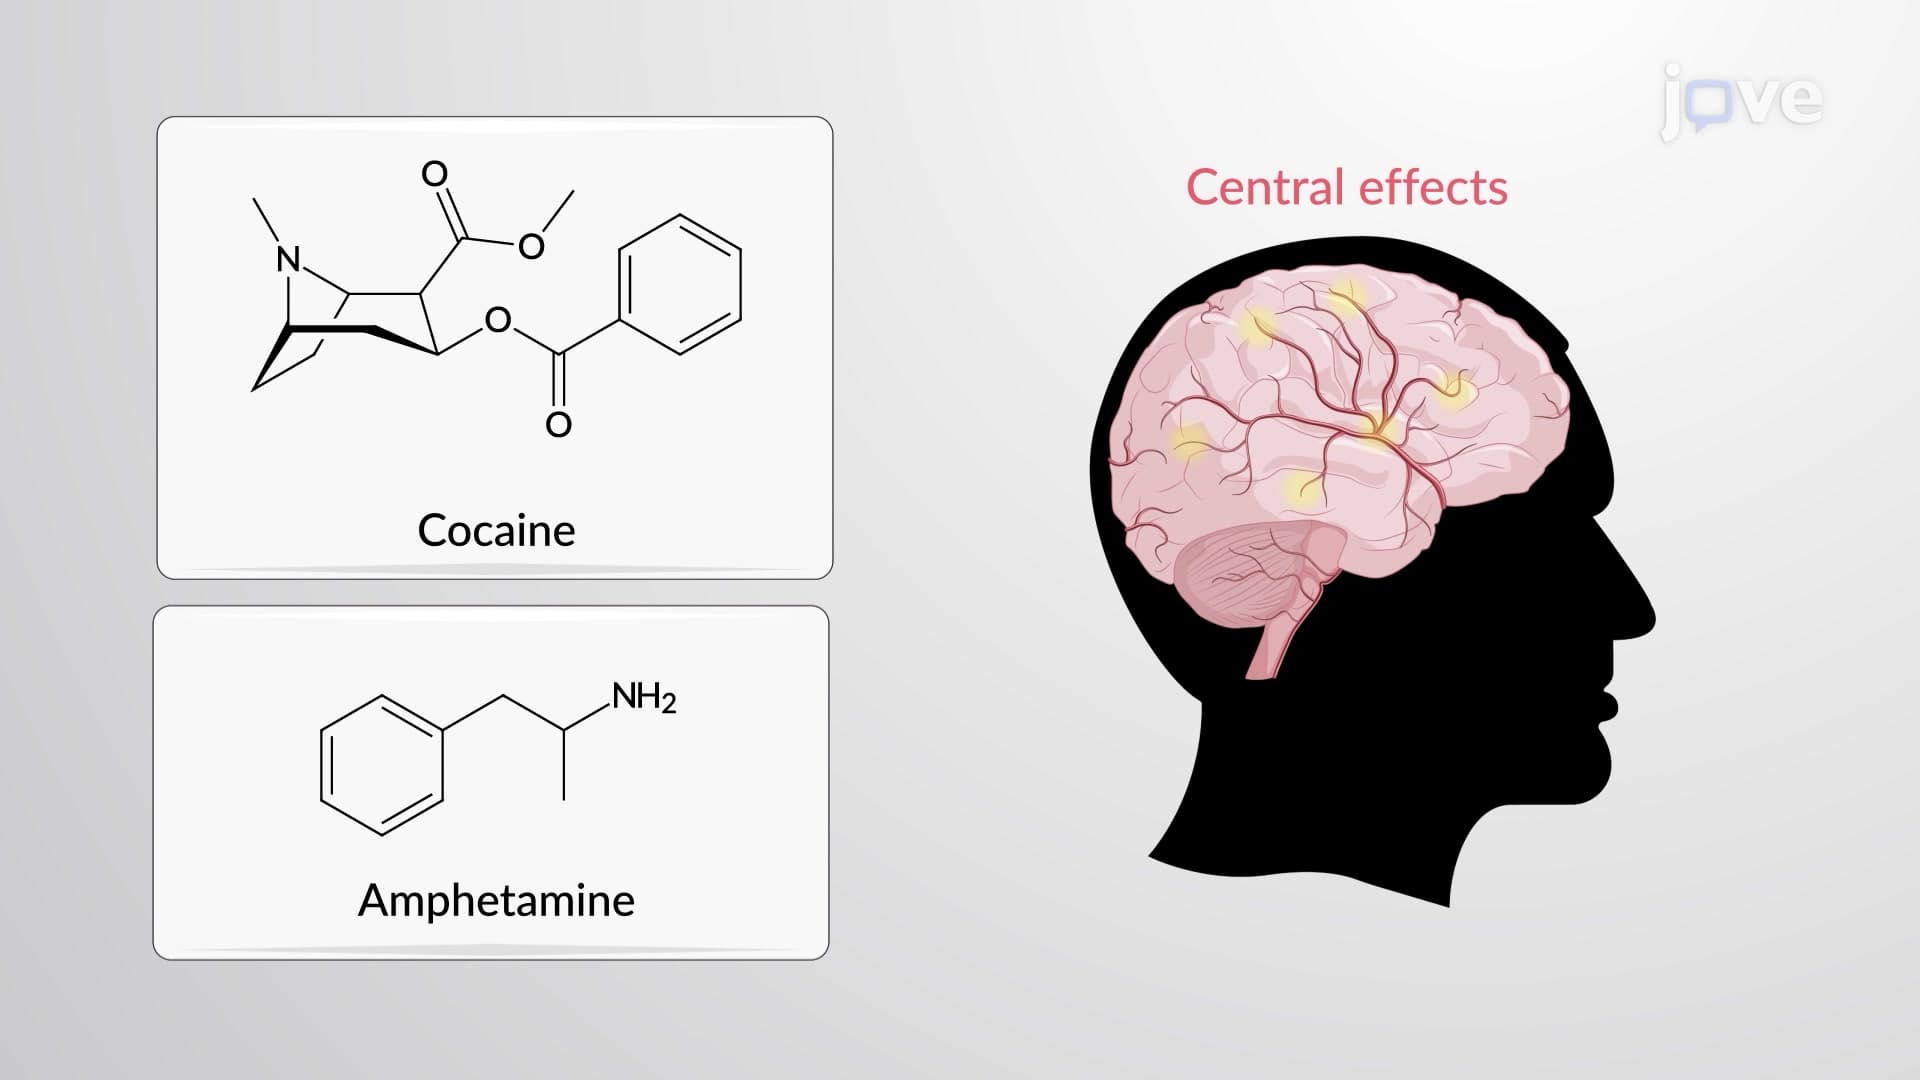
Adrenergic Agonists: Indirect-Acting Agents
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral bioavailability, and...
 01:18
Adrenergic Agonists: Therapeutic Classification
Vasopressor or pressor agents: They increase blood pressure and function as cardiac stimulants. Examples include endogenous catecholamines (norepinephrine and dopamine) and synthetic agents (phenylephrine).
Bronchodilators: β2-agonists can relax bronchial muscles and widen airways. They are commonly used for treating obstructive pulmonary...
 01:11
Direct-Acting Cholinergic Agonists: Therapeutic Uses