Related Experiment Video
Updated: Jun 12, 2026

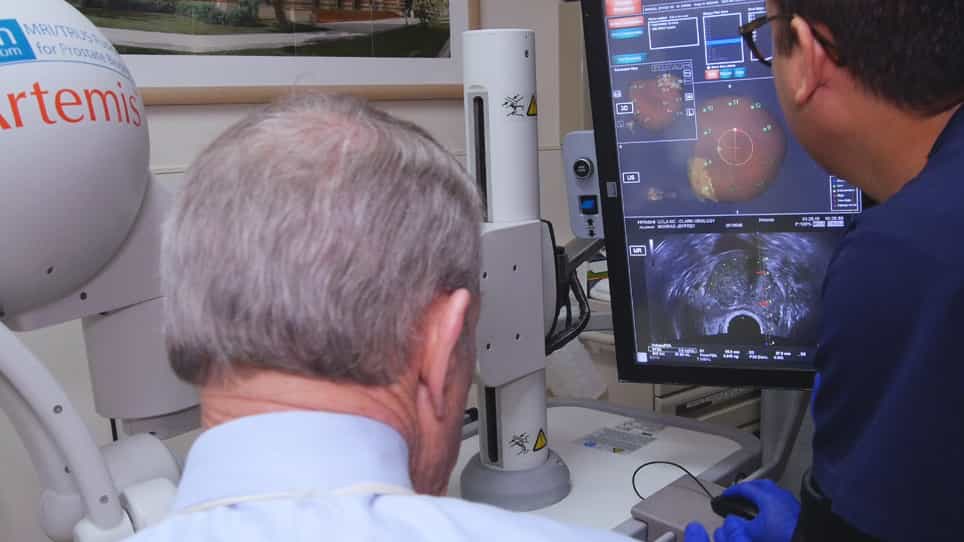
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
MRI-derived real PSA density for risk stratification of PI-RADS 3 lesions: A rule-in approach for clinically
1Department of Radiology, Ankara Bilkent City Hospital, Üniversiteler Mahallesi, Bilkent Bulvarı No:1, 06800 Çankaya, Ankara, Turkey.

Abstract:
Management of PI-RADS 3 lesions remains challenging due to their variable probability of clinically significant prostate cancer (csPCa). Conventional prostate-specific antigen density (PSAD) assumes homogeneous PSA production across the prostate, which may not reflect underlying tissue heterogeneity. This retrospective single-center study included 116 patients with PI-RADS 3 lesions who underwent multiparametric MRI followed by systematic biopsy. Real PSA density (rPSAD) was calculated by normalizing serum PSA to an MRI-derived PSA-producing volume incorporating glandular proxy volume and inflammation-adjusted peripheral zone contribution. csPCa was detected in 20 patients (17%). Among evaluated PSA-based metrics, rPSAD demonstrated the highest discrimination (apparent AUC 0.848; bootstrap-corrected AUC 0.846; 95% CI 0.767-0.924). After Holm-Bonferroni correction, rPSAD significantly outperformed PSA and PZ-PSAD (both adjusted p < 0.001). In a pre-specified multivariable model adjusted for age and prostate volume, rPSAD remained independently associated with csPCa (adjusted OR 2.03 per 0.1 increase; 95% CI 1.48-2.78; p < 0.001). A pre-specified sequential strategy stratified patients into low-risk (PSAD <0.10; csPCa prevalence 9%), intermediate-risk (16%), and high-risk (PSAD ≥0.10 and rPSAD ≥0.45; 53%) groups. Decision curve analysis showed that rPSAD yielded the highest net benefit across most threshold probabilities, while the sequential strategy provided comparable net benefit with categorical clinical interpretability; both substantially exceeded conventional PSAD. Bootstrap-based internal validation confirmed minimal optimism and excellent calibration. These findings suggest that rPSAD improves risk stratification in PI-RADS 3 lesions and may serve as a rule-in tool supporting biopsy decision-making.