Related Experiment Video
Updated: Jun 12, 2026


Setting Up a Stroke Team Algorithm and Conducting Simulation-based Training in the Emergency Department - A Practical Guide
Published on: January 15, 2017
Clinical variable-based decision-support model for rapid differentiation of hemorrhagic and ischemic stroke at
Jae-Woo Kim1, Jin-Heon Jeong2, Moon-Ku Han3
1Chungbuk National University College of Medicine, Medical Artificial Intelligence Center, Chungbuk National University Hospital, Cheongju, Korea.

Background:
Prompt differentiation between ischemic stroke (IS) and hemorrhagic stroke (HS) is critical because their treatment strategies fundamentally differ. While neuroimaging is essential, clinical decision-making often begins before imaging is completed, and conventional clinical scores have shown inconsistent performance. The objective of this study was therefore to develop and externally validate a machine-learning model that supports HS vs. IS subtype suspicion at emergency department (ED) presentation using only clinical variables.
Methods:
We conducted a retrospective multicenter cohort study of 2,998 adult patients with a final diagnosis of acute IS or HS treated at three comprehensive stroke centers (July 2020-January 2024). Patients from hospitals A and B comprised the development/internal validation cohort (n=2,418), while patients from hospital C served as an independent external validation cohort (n=580). An extreme gradient boosting (XGBoost) algorithm was trained using four-fold cross-validation, and feature contributions were assessed using Shapley additive explanation (SHAP) values.
Results:
Internal validation showed an area under the receiver operating characteristic curve (AUROC) of 0.937 (95% CI, 0.922-0.950) with a sensitivity 0.828, specificity of 0.932, and accuracy of 0.905. Independent external validation yielded an AUROC of 0.841 (95% CI, 0.792-0.883) with a sensitivity 0.758, specificity of 0.789, and accuracy of 0.783. SHAP analysis identified headache and higher National Institutes of Health Stroke Scale item 1a (level of consciousness) as factors increasing the model output toward HS, whereas atrial fibrillation shifted predictions toward IS.
Conclusions:
A clinical variable-only model can support early HS vs. IS subtype suspicion at ED presentation among patients managed in an acute-stroke pathway without requiring laboratory tests. Performance decreased on independent external validation, suggesting potential site-related differences and the need for prospective evaluation and calibration. Stroke mimics were not included and should be addressed in future studies.

Related Concept Videos
 01:17
Hemorrhagic Stroke l: Introduction
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:29
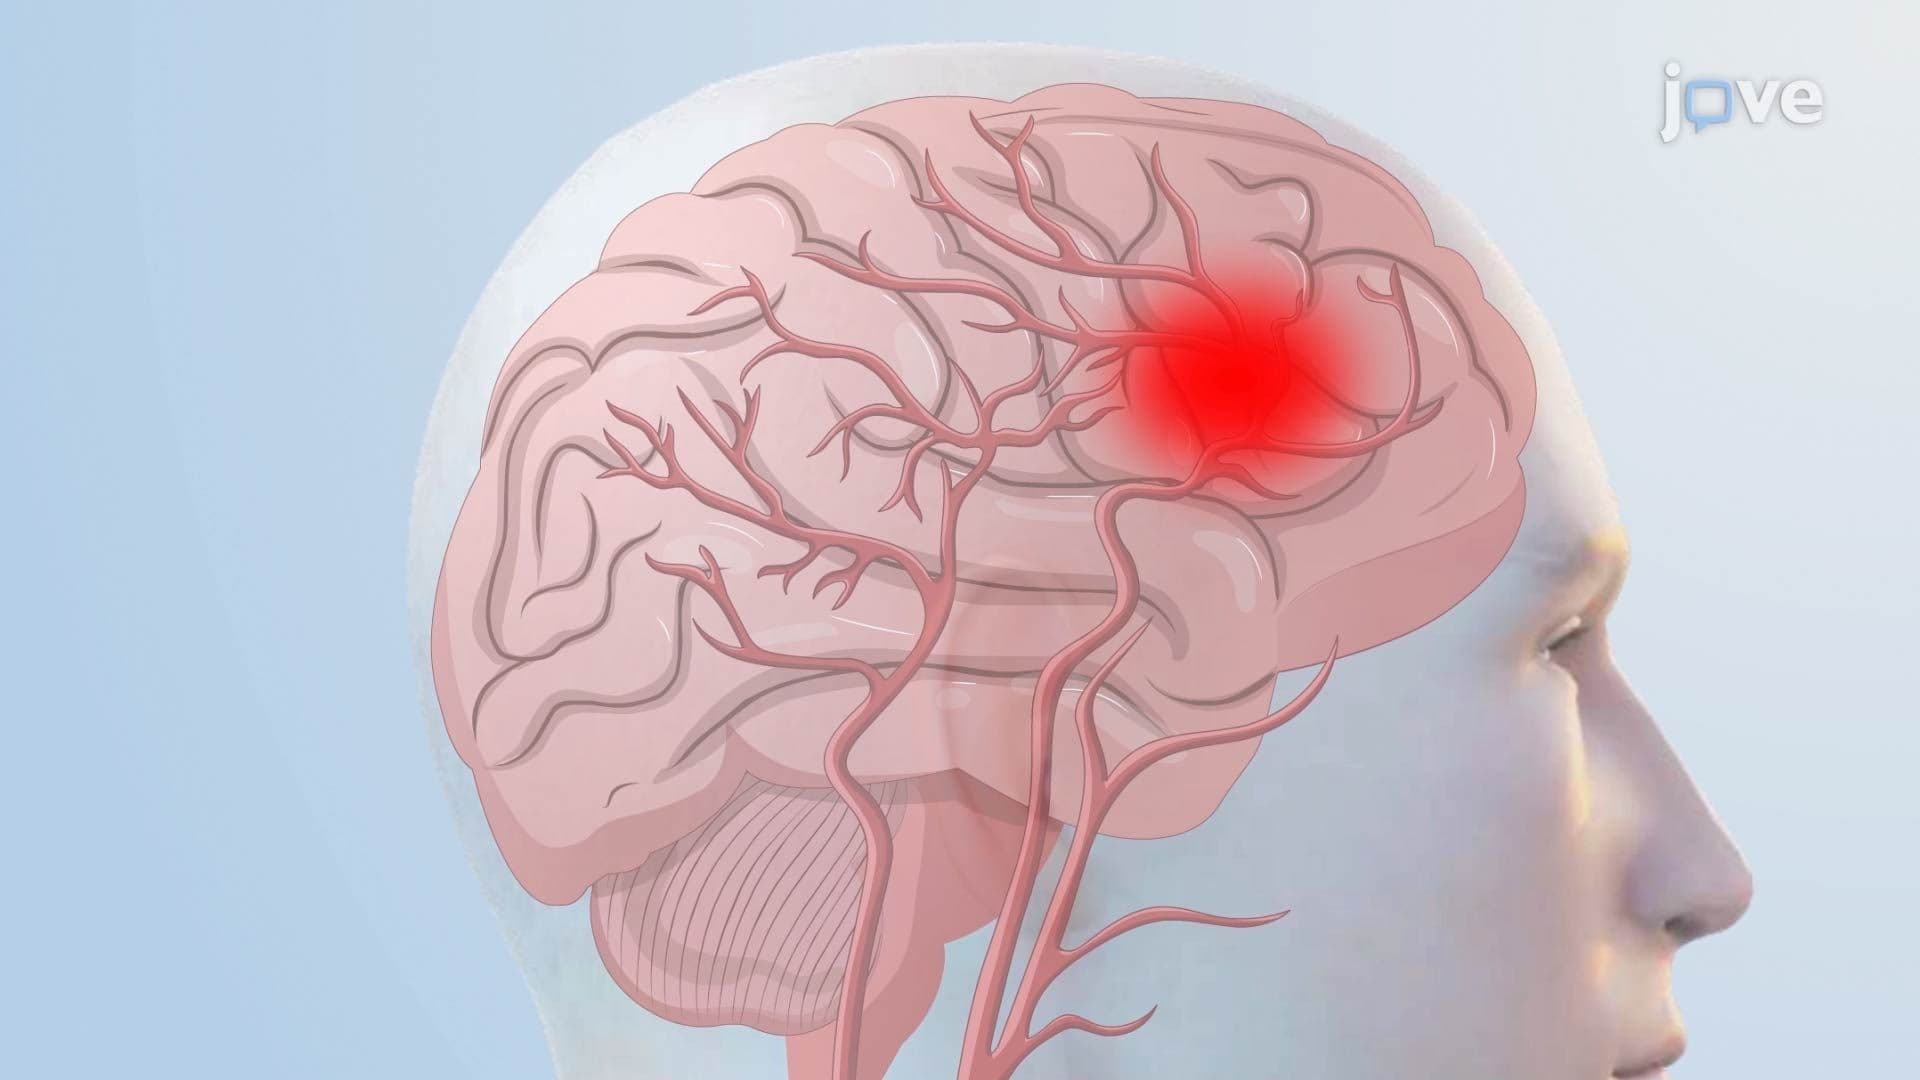
Stroke: Introduction and Types
 01:15
Ischemic Stroke l: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology
 01:30
Acute Coronary Syndrome III: Diagnostic Studies