Related Experiment Video
Updated: Jun 12, 2026
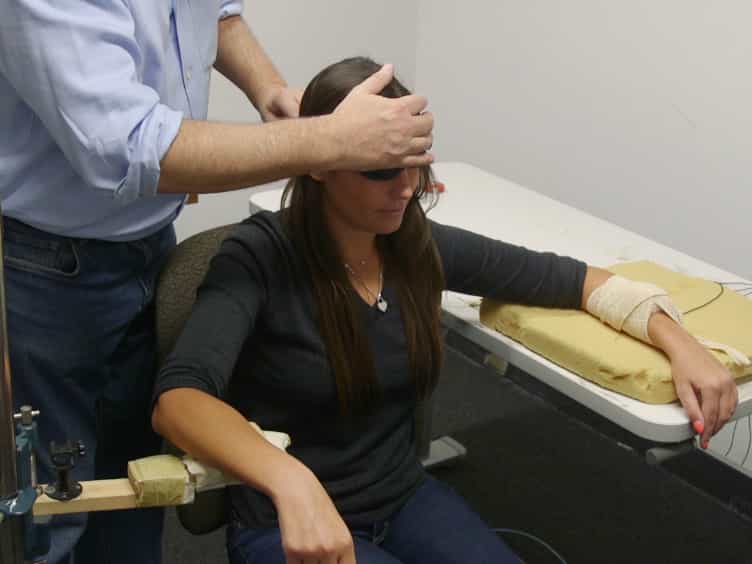
Testing Tactile Masking between the Forearms
Published on: February 10, 2016
Collaborative approaches to masking: statewide threshold development and performance across three respiratory seasons
Jessica Nerby1, Wendy Berg2, Mindy McFarren3
1Safety, Quality and Experience, Allina Health, Minneapolis, MN, USA.

Objective:
Transmission of respiratory illnesses in health care settings poses significant risks to patients and staff. Without clear, standardized masking thresholds, policies may vary, resulting in confusion. We developed statewide consensus thresholds to guide masking in Minnesota health care systems over three respiratory seasons.
Methods:
A multidisciplinary workgroup consisting of infection preventionists, infectious disease providers, occupational health specialists, and representatives from the state health department reviewed available data, including hospitalization rates, influenza-like illness levels, test positivity, and wastewater data. Thresholds used for masking were evaluated and updated each year after analyzing performance and feedback from health care facilities.
Results:
Analysis of the first season thresholds revealed issues with data sources selected and resulted in the group changing threshold recommendations from illness levels to hospitalization rates. Analysis of the second season thresholds revealed issues with masking timing and threshold recommendations for COVID-19 hospitalization leading to changes in COVID-19 masking thresholds and the addition of a masking implementation date for season three. Nine of out ten health systems reporting implementing universal masking during the respiratory season. Those that implemented masking reporting strong staff and leadership support due to the aligned metrics.
Discussion:
Development of standardized thresholds improved staff support for masking and reduced staff and patient confusion. Use of basic epidemiology tools in threshold development allowed for replication across healthcare systems and easy communication of thresholds to staff and patients. Data reporting lags can delay masking during periods of rapidly increasing illness.
More Related Videos
 14:05
Behavioral Assessment of Hearing in 2 to 4 Year-old Children: A Two-interval, Observer-based Procedure Using Conditioned Play-based Responses
Published on: January 23, 2017
 12:43
A Protocol for Comprehensive Assessment of Bulbar Dysfunction in Amyotrophic Lateral Sclerosis (ALS)
Published on: February 21, 2011
Related Concept Videos
 01:24
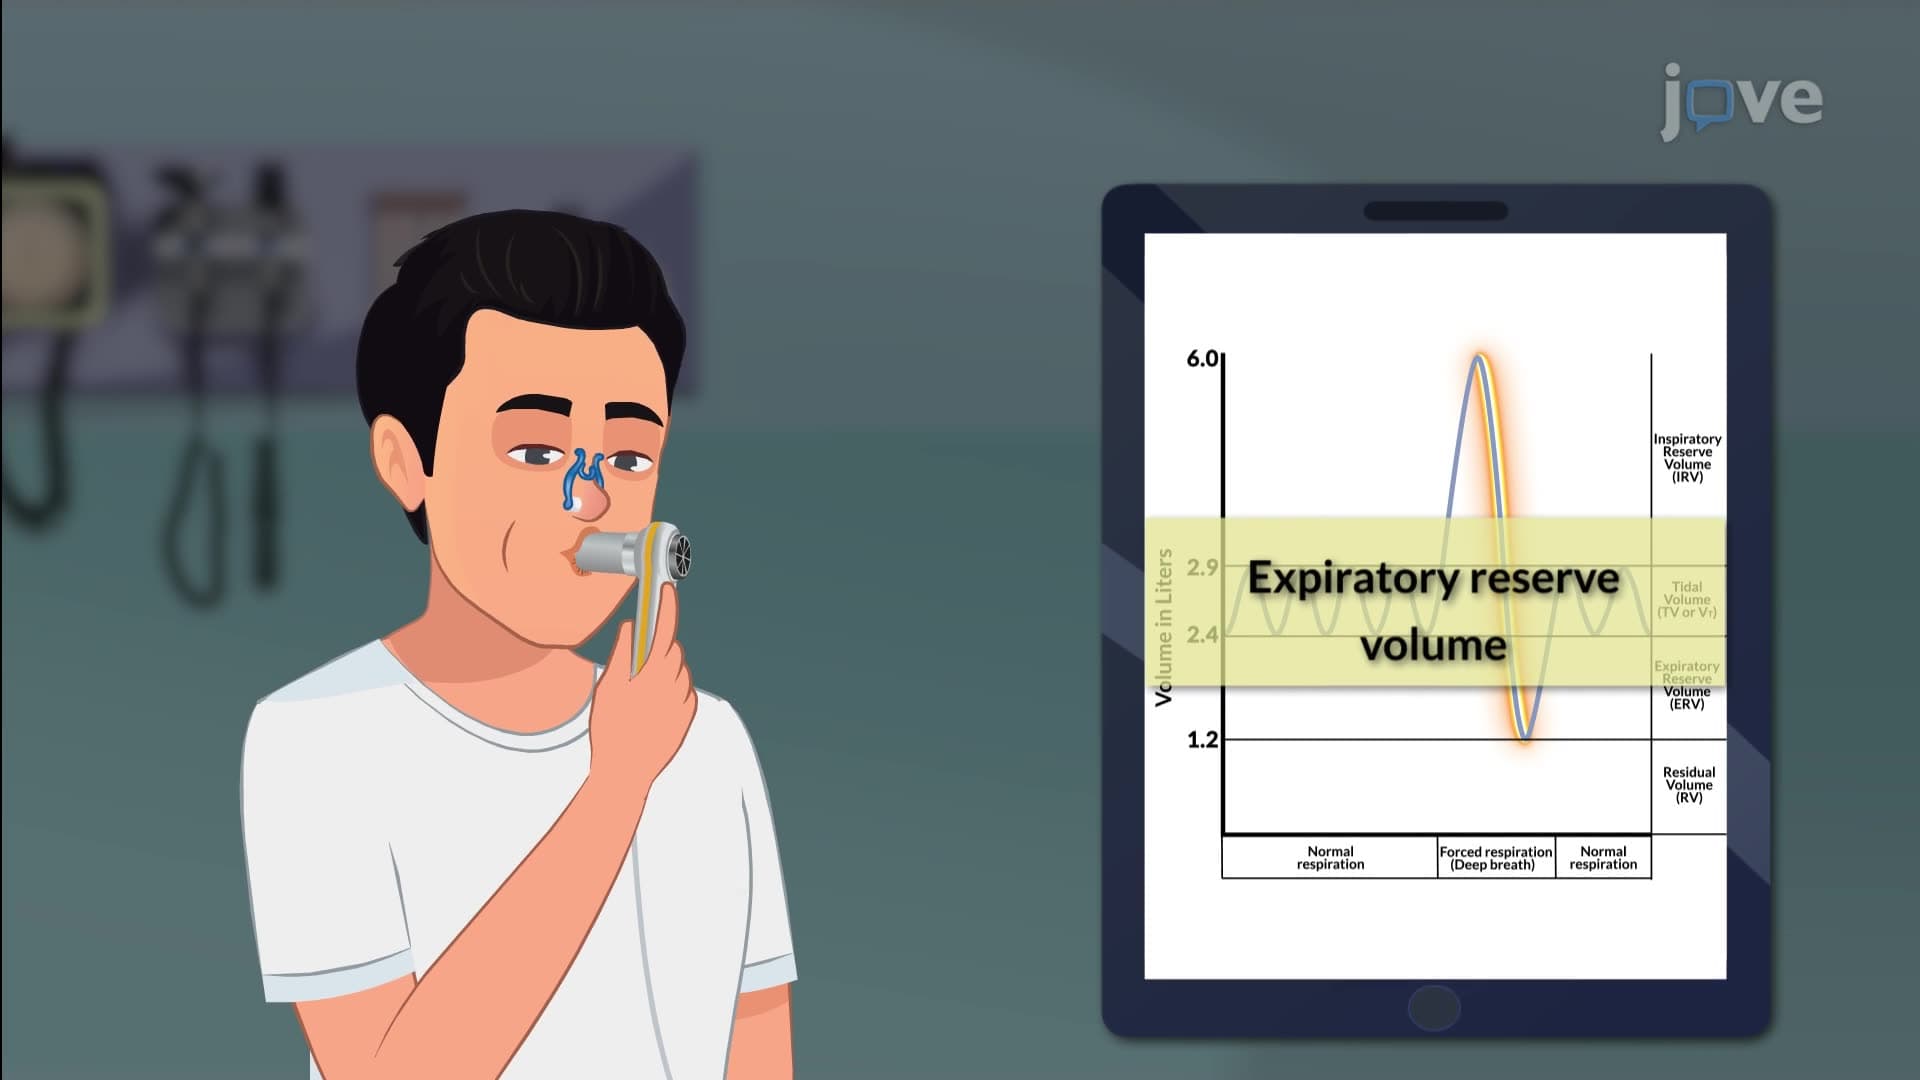
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:15
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:31
Common Respiratory Disorders
Upper respiratory disorders impact the airways above the vocal cords, encompassing areas like the nose, sinuses, and throat. Various conditions fall under this category, including the common cold and allergic rhinitis. These disorders can stem from several causes,...
 01:26
Respiratory Volumes and Capacities I
 01:22
Respiratory Volumes and Capacities