Related Experiment Video For Asian Pacific Association for the Study of the Liver
Updated: Jun 12, 2026
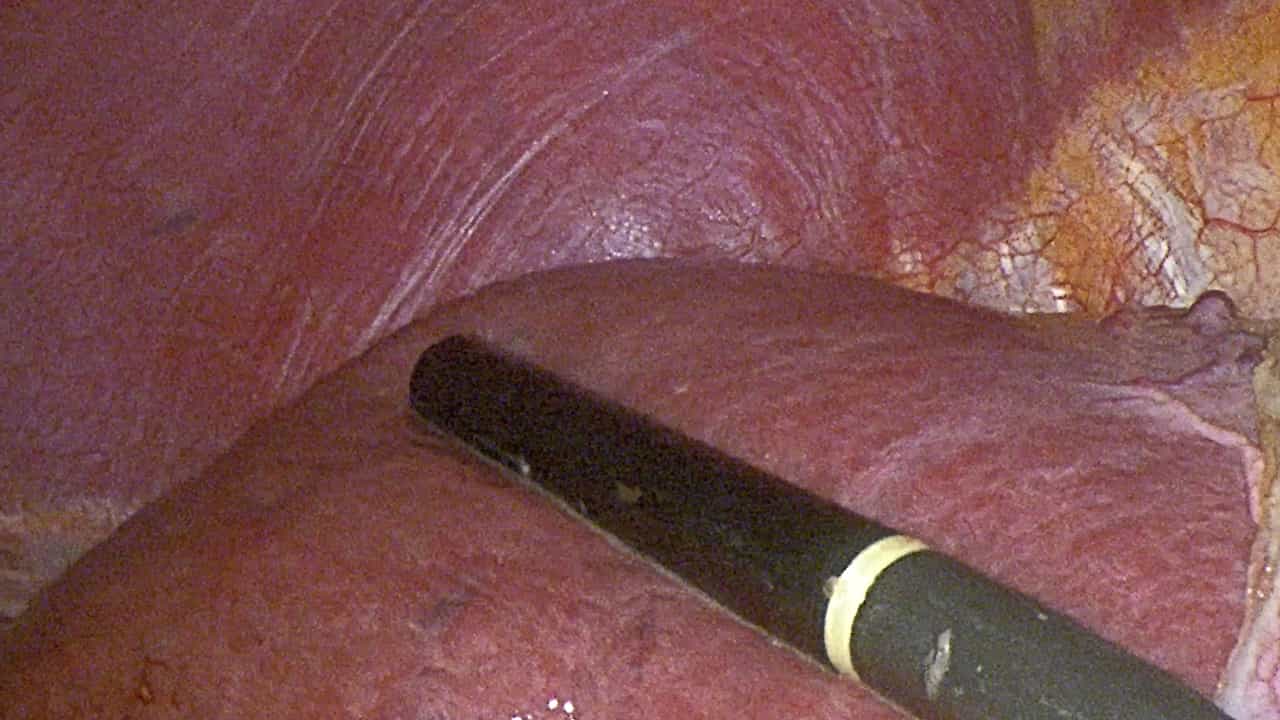

Laparoscopic Anatomical Hepatectomy Using Takasaki's Approach and Indocyanine Green Fluorescence Navigation
Published on: May 16, 2025
Imaging-Based Liver Transplant Eligibility in Hepatocellular Carcinoma: Analysis of 1,094 Patients Using Liver
Yeongseok Hwang1, Subin Heo2, Jihyun An3
1Department of Gastroenterology, Asan Medical Center, University of Ulsan College of Medicine, Seoul, Republic of Korea.

Introduction:
Accurate imaging diagnosis is essential for evaluating liver transplantation (LT) eligibility in hepatocellular carcinoma (HCC) patients. This study investigated whether pre-transplant imaging assessment using the Liver Imaging Reporting and Data System (LI-RADS) and Asia-Pacific guideline-based criteria could effectively predict long-term prognosis when determining LT eligibility.
Methods:
From a prospective registry, we analyzed 1,094 patients with a preoperative HCC diagnosis who had dynamic CT available within 1 month before LT. LT eligibility was assessed with Milan criteria (MC) and Up-to-Seven criteria (UTS). Imaging evaluation was performed using the LI-RADS, Asian Pacific Association for the Study of the Liver, Japan Society of Hepatology, and Korean Liver Cancer Association-National Cancer Center guidelines. We compared HCC-related mortality using competing risk analysis, overall survival, and prognostic performance between imaging-based and pathologic assessments.
Results:
The cohort comprised 158 (14.4%) anti-HCC treatment naïve patients and 936 (85.6%) patients who received anti-HCC treatments in the pre-LT setting. No significant difference in HCC-related mortality was observed between patients meeting imaging-based MC and pathological MC (5-year HCC-related mortality: 8.6-8.7% vs. 6.6%; all p > 0.05). Prognostic performance, assessed by 5-year area under the precision-recall curve and integrated Brier score, showed no significant differences between imaging-based MC and pathological MC groups (all p > 0.05). Similar results were observed for overall survival, UTS-based analyses, and pre-LT treatment subgroup analyses. Concordance between imaging-based MC and pathology-based MC was 84.0-84.4%.
Conclusion:
Although some discordance between imaging-based and pathology-based LT eligibility criteria was observed, pre-transplant imaging provided prognostic stratification comparable to pathology. Given that comprehensive pathological assessment is unattainable before LT, imaging-based evaluation using both LI-RADS and Asia-Pacific guidelines represents a practical and clinically relevant approach for determining LT eligibility.