Related Experiment Video
Updated: Jun 12, 2026
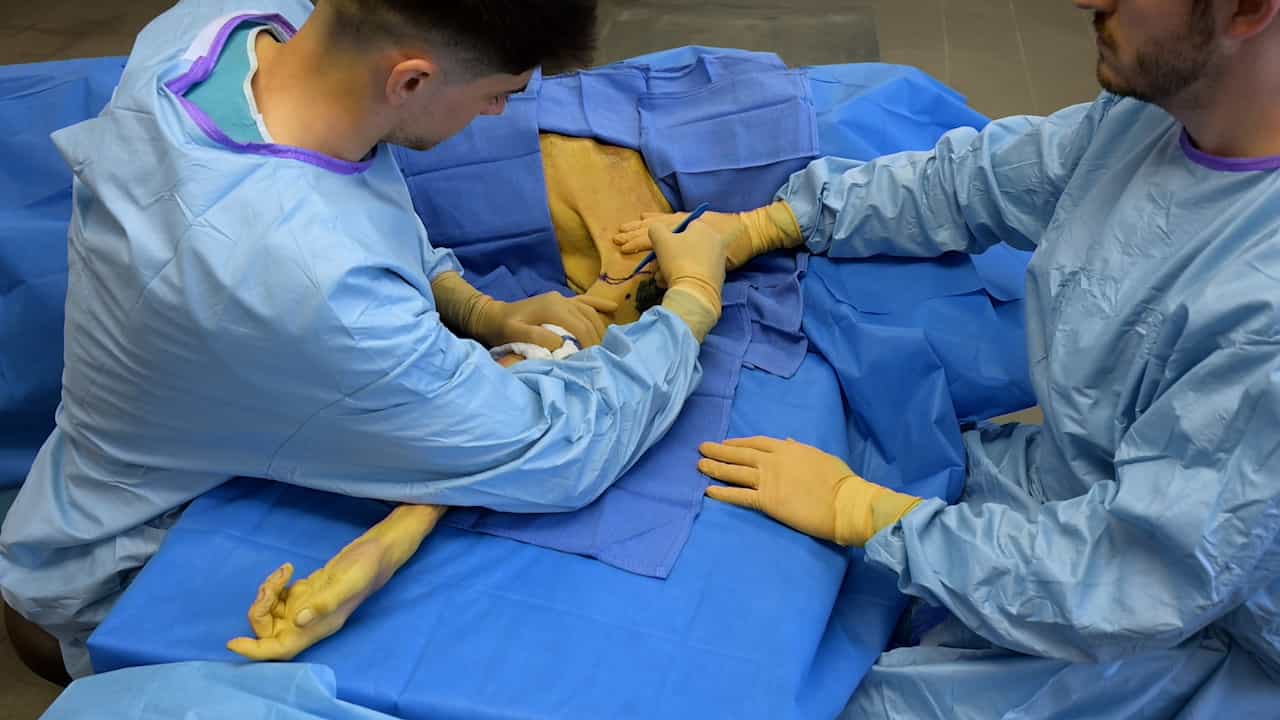

Vascularized Composite Upper Limb Allograft Harvesting for Proximal Arm Allotransplantation
Published on: June 13, 2025
Bone Graft Harvesting Site Morbidity in Donor Area (Anterior Iliac Crest): A Retrospective Study
Bhaskar Borgohain1, Tashi G Khonglah1
1Department of Orthopaedics and Trauma, North Eastern Indira Gandhi Regional Institute of Health and Medical Sciences, Shillong, Meghalaya, India.

Introduction:
In orthopedic practice, autologous bone grafts are routinely employed to aid fracture healing in non-unions. The anterior iliac crest (AIC) is readily accessible, and a standard harvesting site in adults, yielding a generous quantity of bone grafts. Although autologous bone graft remains the gold standard, harvesting graft from the AIC may potentially risk donor site morbidity that is highlighted, especially in the western literature. Our objective in this study was to explore the quantum of donor site morbidity after harvesting AIC bone graft for various reconstructive orthopedic surgeries.
Materials And Methods:
A total of 44 patients of autologous AIC bone graft procedure for various reconstructive orthopedic surgeries (with an average follow-up of 3 years) were evaluated retrospectively on a 9-point retrospective questionnaire response to understand the extent of morbidity.
Results:
Early post-operative pain at the donor site was reported by 19 patients, but the highest level of pain was only 3/10 in Visual Analog Scale (VAS). There was no post-operative wound complication at the donor site (both as per file records/discharge paper and/or patient recollection). Only two patients experienced pain that lasted beyond 1 week. After stitch removal, the average pain in VAS reported was as low as 0.8, and none complained of any residual pain at the final follow-up. Only two patients experienced persistent paresthesia at the donor site.
Conclusion:
In our hands, AIC for bone graft harvesting was a safe and effective procedure with low donor site morbidity. This low morbidity appears to be due to multiple factors (1) low volume of work compared to high volume/high turnover centers (2) bone graft harvesting done by surgeons not below the rank of senior resident (3) awareness in the surgical team about potential graft site morbidity (4) adjunct local anesthetic infiltration/post-operative regional block and pre-emptive analgesia.
Level Of Study:
Level IV, Retrospective study.
