Related Experiment Video
Updated: Jun 13, 2026


Mechanisms Underlying Gut Hormone Secretion Using the Isolated Perfused Rat Small Intestine
Published on: February 26, 2019
Restoring Satiety After GLP-1/GIP Pharmacotherapy: Metabolic Stability, Diet Quality, and the Gut Microbiota
Lidia Lasik1, Natalia Ukleja-Sokołowska2
1Independent Researcher, Poradnia Żywieniowa Akaja, 89-100 Nakło nad Notecią, Poland.

Abstract:
GLP-1 receptor agonists and dual GLP-1/GIP agonists have significantly transformed the treatment of obesity, enabling clinically meaningful weight reduction and improvements in cardiometabolic parameters. However, clinical trial data indicate that cessation of therapy is associated with biologically driven weight regain and a partial loss of metabolic benefits. This phenomenon underscores the chronic nature of obesity and the limited durability of effects achieved through pharmacotherapy alone. Nevertheless, structured clinical frameworks describing how to maintain satiety and metabolic stability after GLP-1/GIP dose reduction or discontinuation remain limited. The aim of this narrative review is to discuss the mechanisms underlying weight regain following dose reduction or discontinuation of GLP-1/GIP pharmacotherapy and to present strategies supporting long-term metabolic stabilisation. Weight regain is driven in part by persistent metabolic adaptations, including a reduction in resting energy expenditure (adaptive thermogenesis), alterations in the hunger-satiety axis (increased ghrelin, reduced leptin signalling), and potentially incomplete restoration of adipose tissue and liver-related metabolic function, although direct evidence in this specific setting remains limited. Weight loss is often accompanied by a reduction in fat-free mass, which further lowers energy expenditure and increases susceptibility to a positive energy balance after treatment cessation. It remains unclear whether pharmacological suppression of appetite results in sustained normalisation of endogenous satiety regulation after treatment cessation, and its effects on gut microbiota function remain uncertain. In clinical practice, key priorities include preserving muscle mass (adequate protein intake, resistance training), maintaining dietary nutrient density, stabilising postprandial glycaemia, and ensuring sufficient intake of fermentable fibre to support short-chain fatty acid production and gut-brain signalling. GLP-1/GIP pharmacotherapy should be viewed as a component of an integrated model of obesity treatment. We propose that long-term weight stabilisation may require a transition from pharmacologically induced satiety to satiety supported by diet quality, preserved fat-free mass, and metabolic stability. Further research is needed to define optimal post-treatment strategies and to identify patients in whom therapy can be safely reduced or discontinued. This transition should be regarded as a conceptual framework and forward-looking hypothesis requiring validation in prospective studies.
Related Concept Videos
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:18
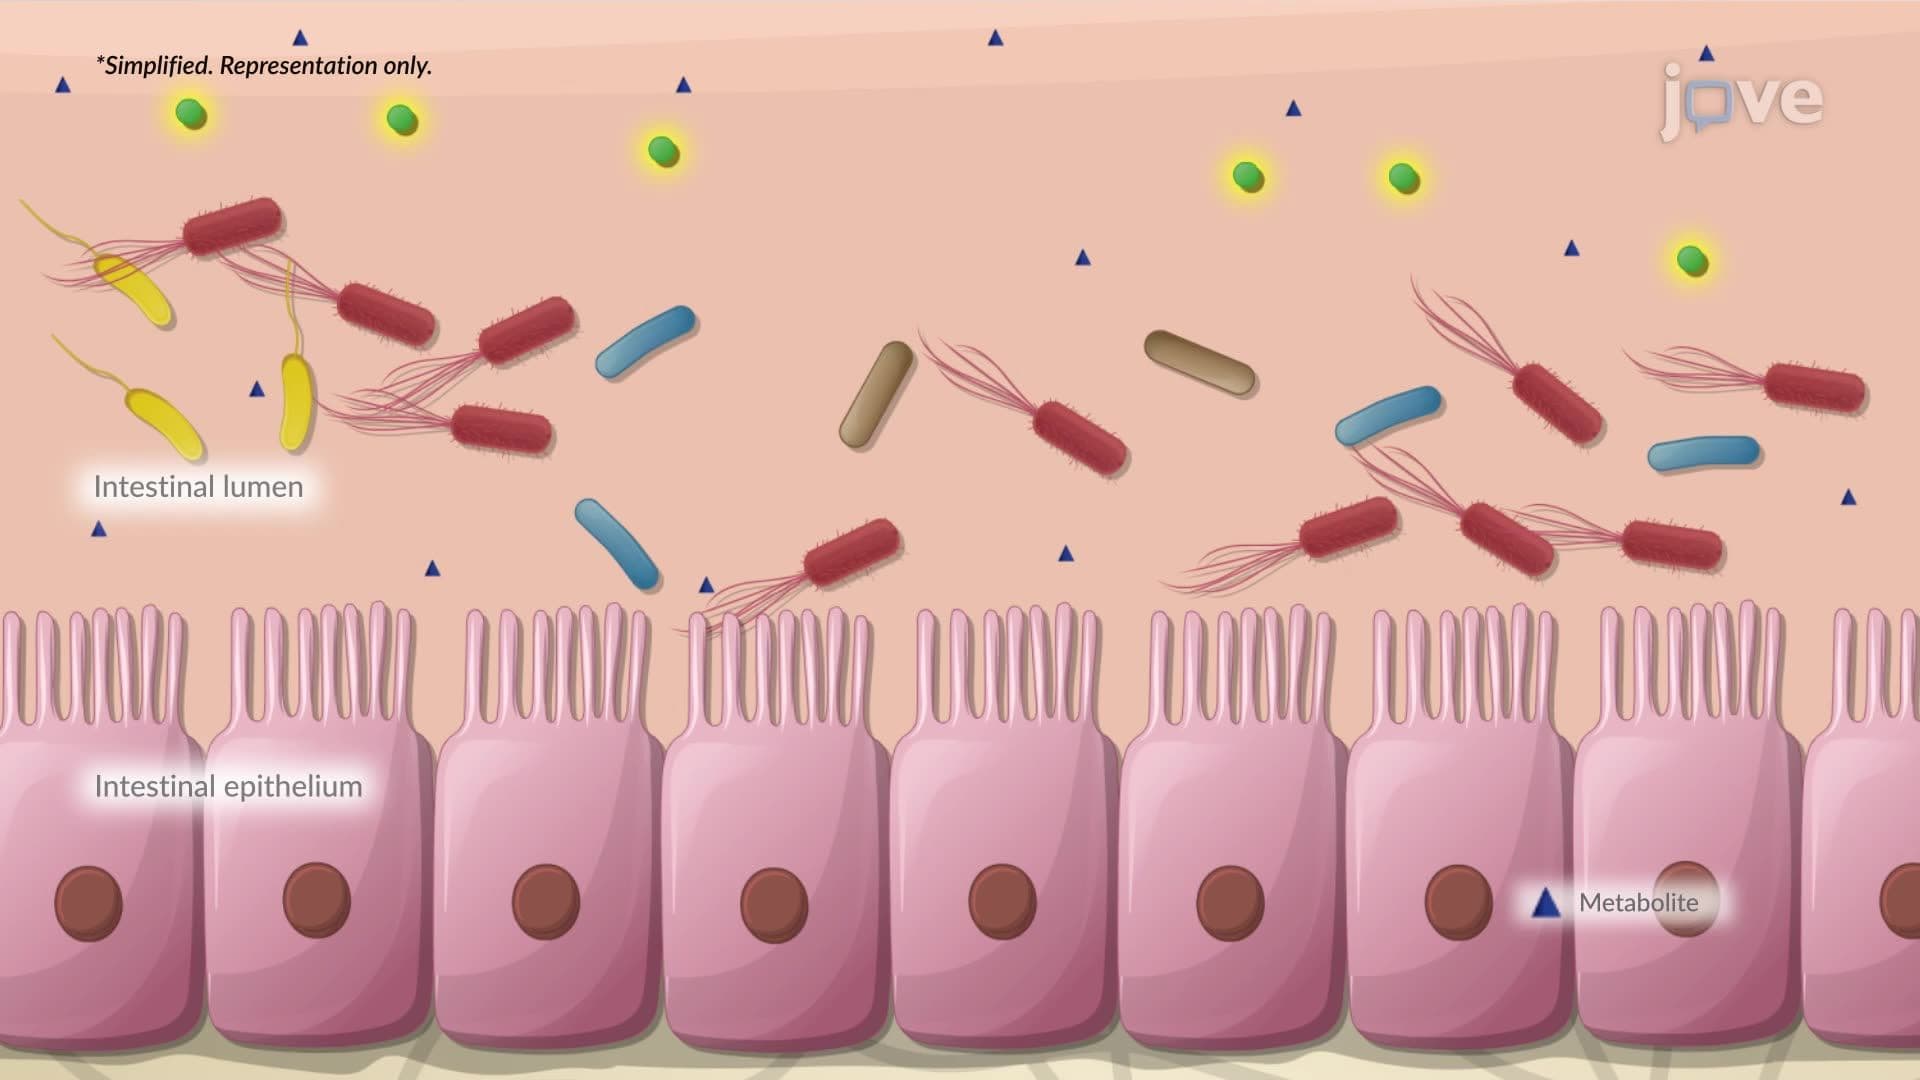
Dysbiosis of the Gut Microbiota
 01:06
Oral Hypoglycemic Agents: Glinides
 01:21
Microbiota Modulation by Antibiotics
 01:15
Hypoglycemia and Glucagon