Related Experiment Video
Updated: Jun 13, 2026
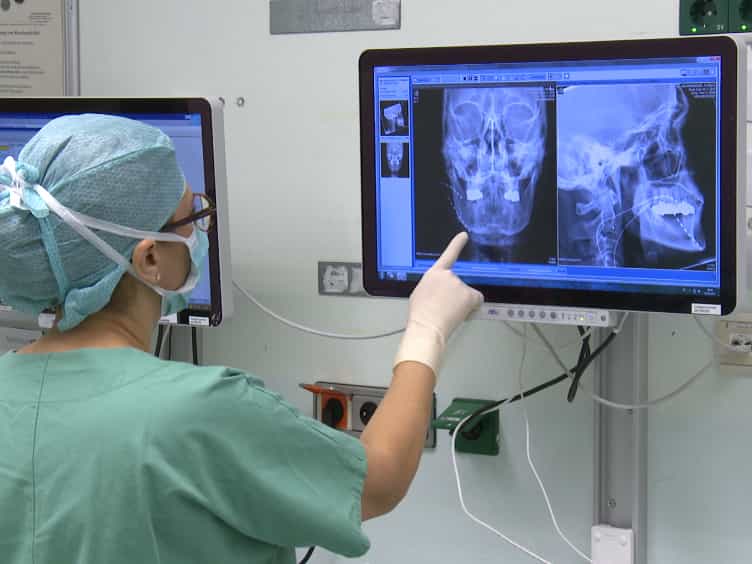

Subcutaneous Trigeminal Nerve Field Stimulation for Refractory Facial Pain
Published on: May 10, 2017
Post-Dental and Alveolar Nerve-Related Trigeminal Pain in Patients Referred with Trigeminal Neuralgia Terminology: A
Shachar Zion Shemesh1,2, Paz Kelmer1, Jose Asprilla1
1Department of Neurosurgery, Sheba Medical Center, Ramat Gan 5266202, Israel.

Abstract:
Background: Trigeminal neuralgia (TN), a facial pain disorder classically characterized by recurrent brief electric-shock-like paroxysms in one or more trigeminal divisions, frequently traverses dental pathways before specialist evaluation. Conversely, dental extraction, endodontic treatment, implant procedures, and third-molar surgery may injure the inferior alveolar, superior alveolar, mental, or lingual nerves and generate painful post-traumatic trigeminal neuropathy. We sought to define the diagnostic interface between classical TN and post-dental/alveolar nerve-related trigeminal pain in a tertiary referral cohort. Methods: We performed a retrospective single-center diagnostic-pathway study using a clinical dataset comprising 672 unique patients. A dental-interface trigeminal candidate cohort was assembled from aggregated patient-level source notes and adjudicated into five prespecified phenotypes: confirmed alveolar neuropathy, post-extraction neuropathic onset, odontogenic diagnostic misclassification, mixed/uncertain dental-interface pain, and clean classical TN. Extracted variables included demographics, trigeminal branch documentation, sensory deficit, dental procedure history, post-extraction onset, MRI and neurovascular conflict language, secondary structural disease, TN-directed medication exposure, invasive treatment exposure, documented outcomes, and time from first specialist documentation to first dated invasive treatment. Results: Among 201 dental-interface trigeminal candidates, 19 patients (9.5%) had confirmed alveolar neuropathy, 31 (15.4%) had post-extraction neuropathic onset, 20 (10.0%) represented odontogenic diagnostic misclassification, 115 (57.2%) remained mixed/uncertain, and 16 (8.0%) fulfilled a clean classical TN phenotype. Overall, 114 patients (56.7%) carried explicit TN terminology somewhere in the chart. Non-classical alveolar/post-dental syndromes comprised 70 patients (34.8%). Compared with clean classical TN, this non-classical group had higher rates of documented oral sensory deficit (38.6% vs. 0.0%, p = 0.002), post-extraction onset (52.9% vs. 0.0%, p < 0.001), extraction history (61.4% vs. 0.0%, p < 0.001), and secondary structural disease (22.9% vs. 0.0%, p = 0.035). Neurovascular conflict or vascular-loop language did not distinguish non-classical alveolar/post-dental syndromes from clean classical TN (38.6% vs. 37.5%, p = 1.000). Conclusions: A substantial minority of tertiary dental-interface trigeminal referrals represented alveolar/post-dental syndromes rather than clean classical TN, even while carrying TN labels and accumulating TN-directed treatment exposure. Post-extraction onset, lower-lip/chin or intraoral sensory change, and pain persisting despite extraction should prompt careful phenotyping before classical TN-directed escalation. The alveolar-trigeminal interface can be operationalized as a recognizable diagnostic pathway with direct implications for multidisciplinary facial-pain evaluation.

Related Concept Videos
 01:21
Tooth Anatomy
The Crown, Neck, and Root
The visible part of the tooth is referred to as the crown. It's covered by enamel, the hardest substance in the human body. The crown is uniquely shaped for each type of tooth, allowing for different functions such as cutting, tearing, or grinding food.
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:25
Analgesia and Pain Management