Related Experiment Video
Updated: Jun 13, 2026


A Machine Learning Approach to Design an Efficient Selective Screening of Mild Cognitive Impairment
Published on: January 11, 2020
Predicting the timing of first sustained cognitive worsening in Alzheimer's disease using real-world clinical data

Background:
Cognitive assessments are sparsely documented in electronic health records (EHRs), limiting scalable detection of cognitive worsening in real-world clinical settings.
Methods:
We applied a deep neural network optimized for identifying clinical event timing from sparsely labeled gold-standard data ( label-efficient incident phenotyping from longitudinal EHR , LATTE) to predict time-to-first sustained cognitive worsening in AD patients from a large healthcare system (2011-2022) with linkage to an AD Research Center registry in a subset. Sustained cognitive worsening was defined as cognitive decline persisting over ≥2 consecutive visits within 3 years. Separate LATTE models were trained with worsening labels from Clinical Dementia Rating (CDR), Mini-Mental Status Examination (MMSE), and Montreal Cognitive Assessment (MoCA) scores; semi-supervised learning scaled predictions to larger imputation cohorts lacking sufficient longitudinal scores. We evaluated model performance using average time-specific area under the receiver operating characteristic curve (AUC), area between curves (ABC), and Brier scores. To demonstrate clinical utility, we examined whether predicted time-to-worsening differentiated clinically meaningful patient subgroups using competing-risk Cox proportional hazards models accounting for death.
Findings:
The cohort comprised 27,614 AD patients (65% women, 91% non-Hispanic White, mean [SD] age at start of follow-up 78.76 [9.53] years). In gold-standard cohorts (n: CDR=632, MMSE=710, MoCA=752; remaining patients formed imputation cohorts), LATTE demonstrated robust predictive performance (average time-AUC: CDR 0.816, MMSE 0.694, MoCA 0.710; ABC: CDR 0.067, MMSE 0.293, MoCA 0.078; Brier score: CDR 0.252, MMSE 0.437, MoCA 0.295). APOE -ε4 carriers had shorter predicted time-to-worsening compared to non-carriers across all assessments in the imputation cohorts (HRs 1.241-1.376, all p <0.025), and k-means derived patient clusters showed differential time-to-worsening in the overall and imputation cohorts (HRs 0.777-0.908, all p <.001).
Interpretation:
LATTE enables scalable prediction of sustained cognitive worsening timing, differentiating clinically meaningful patient subgroups. This approach could improve AD clinical monitoring and decision-making in routine care and support targeted clinical trial enrichment.
Evidence Before This Study:
The growing burden of Alzheimer's disease (AD) creates an urgent unmet need for pragmatic tools to monitor cognitive decline at the point of care and identify target patient populations for clinical trial recruitment. However, cognitive assessments are sparsely documented in electronic health records (EHRs), and fluctuating scores can obscure true worsening, whereas specialized fluid and neuroimaging biomarkers are rarely available outside research settings, limiting scalable real-world utility.
Added Value Of This Study:
We applied a deep neural network algorithm optimized for identifying clinical event timing from sparsely labeled longitudinal EHR data (LATTE) to predict time-to-first sustained cognitive worsening across three complementary cognitive assessments in AD patients from a large healthcare system: the Clinical Dementia Rating (CDR), Mini-Mental State Examination (MMSE), and Montreal Cognitive Assessment (MoCA). We defined sustained cognitive worsening as clinically meaningful decline (without improvement) persisting over ≥2 consecutive visits within 3 years. We trained LATTE on gold-standard cohorts with sparse outcome labels derived from longitudinal cognitive assessments, then leveraged a semi-supervised framework to scale predictions to larger imputation cohorts lacking gold-standard cognition outcome labels. The algorithm robustly predicted the timing of first sustained cognitive worsening, with CDR outperforming MMSE and MoCA. For orthogonal validation, predicted time-to-worsening differentiated clinically meaningful subgroups defined by APOE-ε4 carrier status and knowledge graph-guided patient clustering.
Implications Of All The Available Evidence:
Scalable prediction of cognitive worsening from sparsely labeled EHR data could identify patients at higher risk of sustained cognitive worsening. In routine clinical practice, this could inform timely disease-modifying therapy initiation and care planning. Targeted enrichment of clinical trial populations with higher-risk patients could increase statistical power and reduce sample size requirements.
Related Concept Videos
 01:29
Alzheimer Disease l: Introduction
 01:26
Alzheimer's Disease: Overview
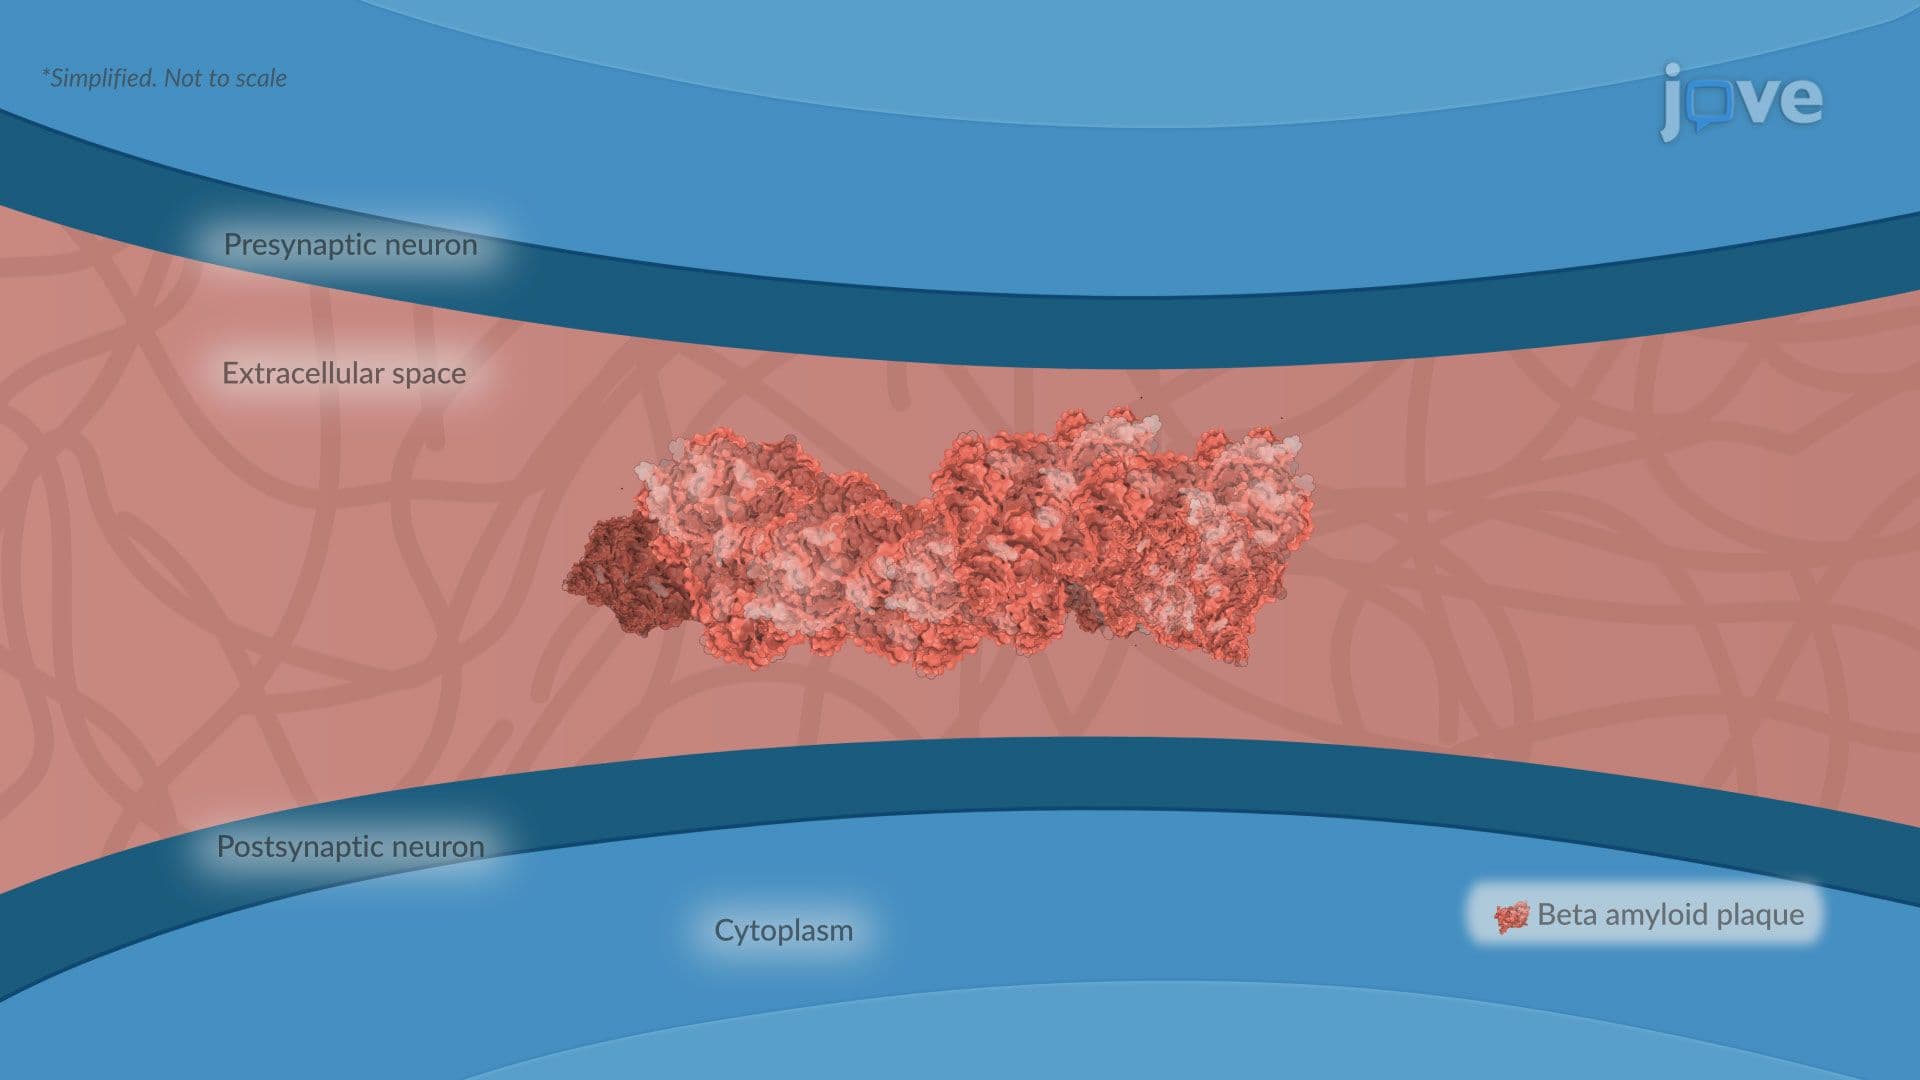
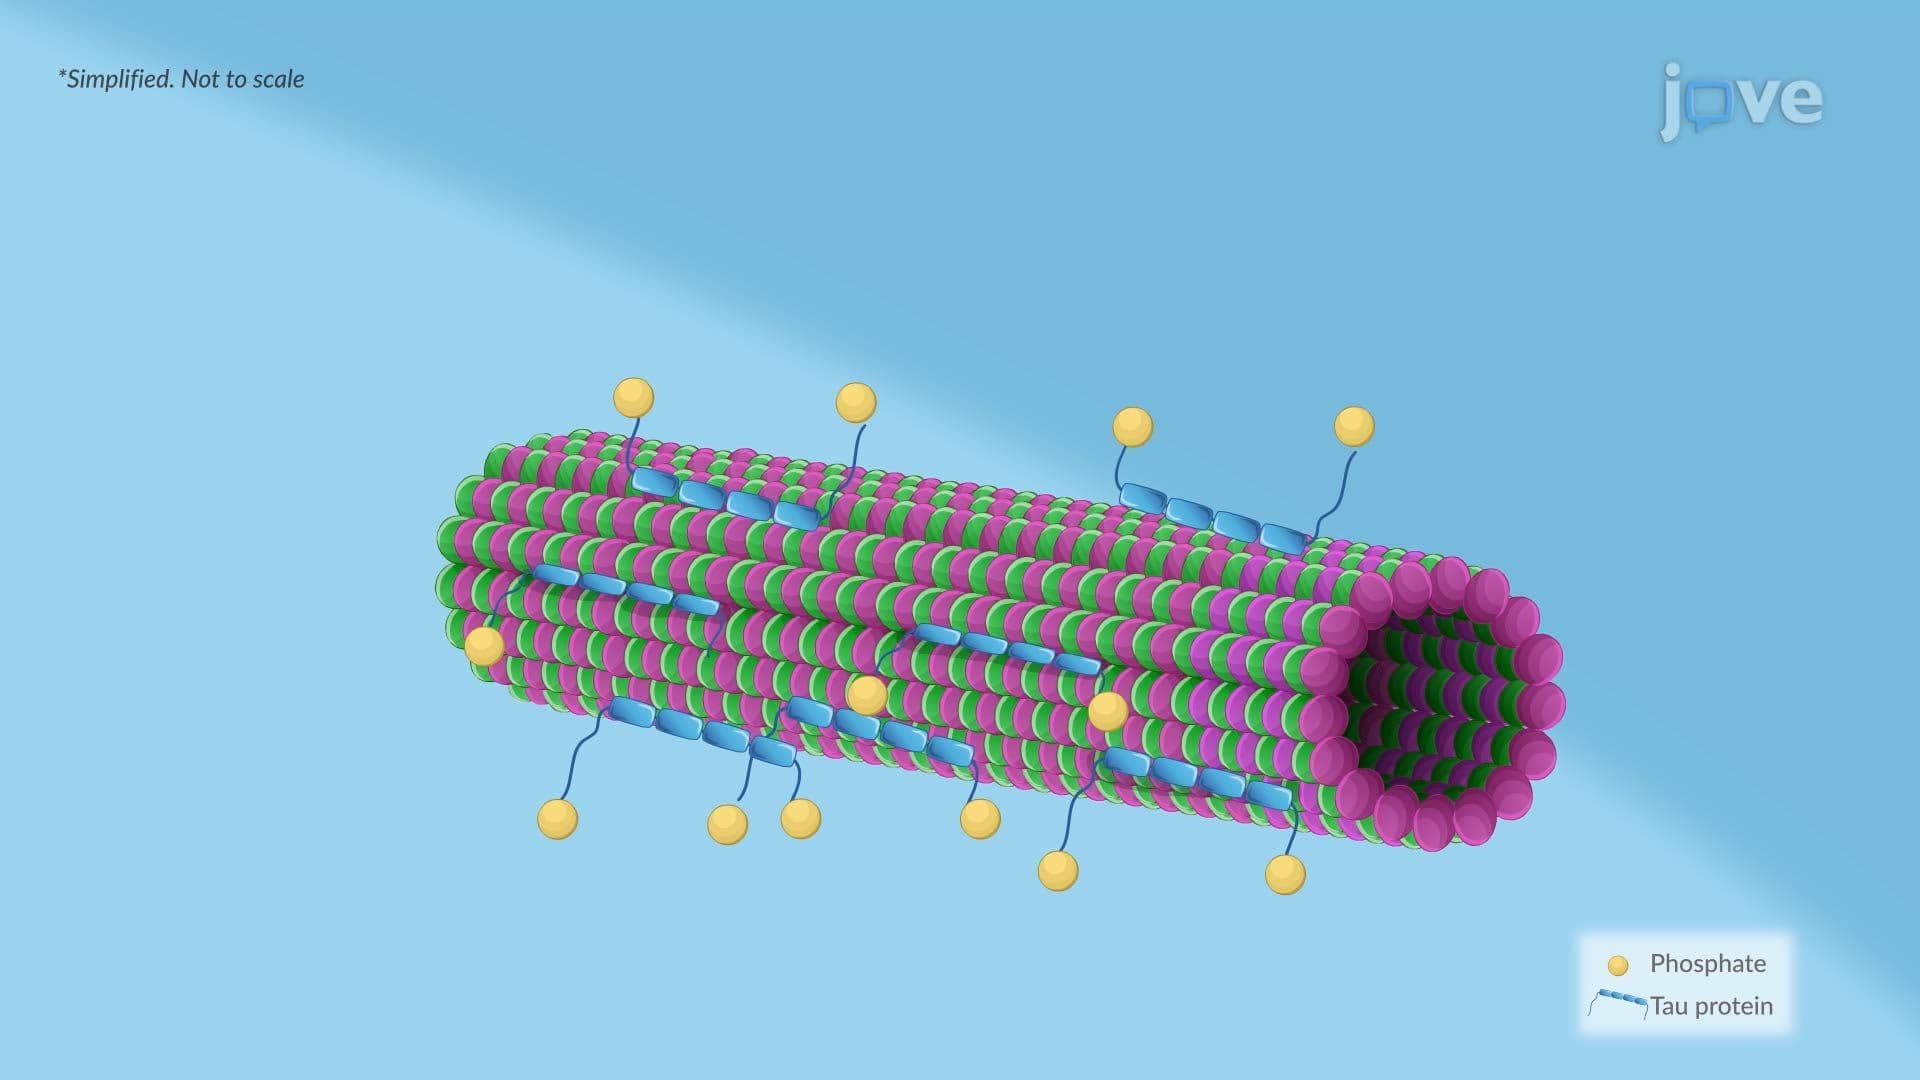
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:22
Dementia l: Introduction
 01:22
Alzheimer's Disease: Treatment
 01:23
Alzheimer Disease ll: Pathophysiology
 01:30
Dementia
The progression of dementia is generally gradual.