
Gastric Residual Volume Assessment in Critically Ill Children: The GASTRIC-PICU Randomized Clinical Trial
Lyvonne N Tume1,2, Paul R Mouncey3, Julia M Broomhall3
1Faculty of Health, Social Care & Medicine, Edge Hill University, Ormskirk, United Kingdom.

Insights
Discontinuing routine gastric residual volume (GRV) assessments in critically ill children on mechanical ventilation did not worsen outcomes and improved nutritional delivery. This evidence-based approach enhances care for pediatric patients receiving enteral nutrition.
Area of Science:
- Pediatric Critical Care Medicine
- Clinical Nutrition
- Gastroenterology
Background:
- Routine assessment of gastric residual volume (GRV) is common practice in critically ill children but lacks evidence.
- High perceived GRV often leads to withholding enteral feeds, negatively impacting nutritional delivery.
- Current guidelines do not support routine GRV assessment for guiding enteral feeding.
Purpose of the Study:
- To evaluate the impact of omitting routine GRV assessments versus 6-hourly assessments in ventilated children.
- To determine effects on mechanical ventilation duration, survival rates, and nutritional target achievement.
- To assess the noninferiority and superiority of a strategy without routine GRV monitoring.
Main Methods:
- A pragmatic, multicenter randomized noninferiority trial involving 4700 children (0-16 years) on invasive ventilation.
- Participants were randomized to either usual care (GRV assessment every 6 hours) or no routine GRV assessment.
- Feed tolerance in the no-routine GRV group was assessed clinically; primary outcomes included survival, days free from ventilation, and nutritional achievement by 72 hours.
Main Results:
- No routine GRV assessment was noninferior to 6-hourly assessments for survival and days free from mechanical ventilation (median 25 days in both groups).
- The group without routine GRV assessment showed significantly higher achievement of energy requirements by 72 hours (80.3% vs. 76.8%).
- Per-protocol analysis confirmed the intention-to-treat findings, supporting the noninferiority and nutritional benefits.
Conclusions:
- Omitting routine gastric residual volume assessments in critically ill, enterally fed children is safe and noninferior to current practices.
- This strategy significantly enhances the achievement of nutritional targets within 72 hours.
- Clinical assessment of feed tolerance is sufficient, supporting a shift away from routine GRV monitoring in pediatric intensive care.
Importance:
Routine assessment of gastric residual volume (GRV) to guide enteral feeding in critically ill children is widespread but not based on evidence. Perceived high gastric volumes often lead to withholding feeds, impairing nutritional delivery.
Objective:
To evaluate the effect of not routinely assessing GRV compared with assessments at least every 6 hours in children undergoing mechanical ventilation on the duration of mechanical ventilation and survival and achievement of nutritional targets.
Design, Setting, And Participants:
A pragmatic, multicenter, randomized, noninferiority trial in 23 pediatric intensive care units (PICUs) in the UK and 1 in Switzerland. A total of 4700 children aged 0 to 16 years who were receiving invasive ventilation and starting enteral feeds were recruited between June 29, 2023, and December 7, 2025, with 30-day follow-up completed on January 6, 2026.
Interventions:
Children were randomized (1:1) to receive usual care (GRV assessment every 6 hours) or no routine GRV assessment to guide enteral feeding. In the no routine GRV assessment group, feed tolerance was assessed using only clinical signs. All other enteral feeding practices followed local protocols.
Main Outcomes And Measures:
The clinical co-primary outcome (noninferiority) was a composite of survival and days free from mechanical ventilation at 30 days. The nutritional co-primary outcome (superiority) was the percentage of children meeting energy requirements by 72 hours.
Results:
Of the 4700 children randomized (2352 to the no routine GRV assessment group and 2348 to the usual care group), 4460 were included in the intention-to-treat analysis (median [IQR] age, 8 [1-44] months; 1925 [42.6%] females). No routine GRV assessment was noninferior to regular 6-hourly assessments for survival and days free from mechanical ventilation at 30 days (median [IQR], 25 [21-27] days in both groups; adjusted odds ratio [OR], 0.95 [95% CI, 0.86-1.05]). Results of the per-protocol analysis were consistent with the intention-to-treat analysis (adjusted OR, 1.01 [95% CI, 0.90-1.13]). The mean percentage of energy requirements achieved by 72 hours was 80.3% in the no routine GRV assessment group and 76.8% in the usual care group (adjusted mean difference, 3.2 [95% CI, 1.3-5.2] percentage points; P < .001).
Conclusions And Relevance:
Among critically ill children being enterally fed, not assessing GRV routinely was noninferior to regular assessments every 6 hours and significantly increased nutritional achievement at 72 hours.
Trial Registration:
isrctn.org Identifier: ISRCTN79668198.
Related Concept Videos
 01:16
Gastric Emptying
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:15
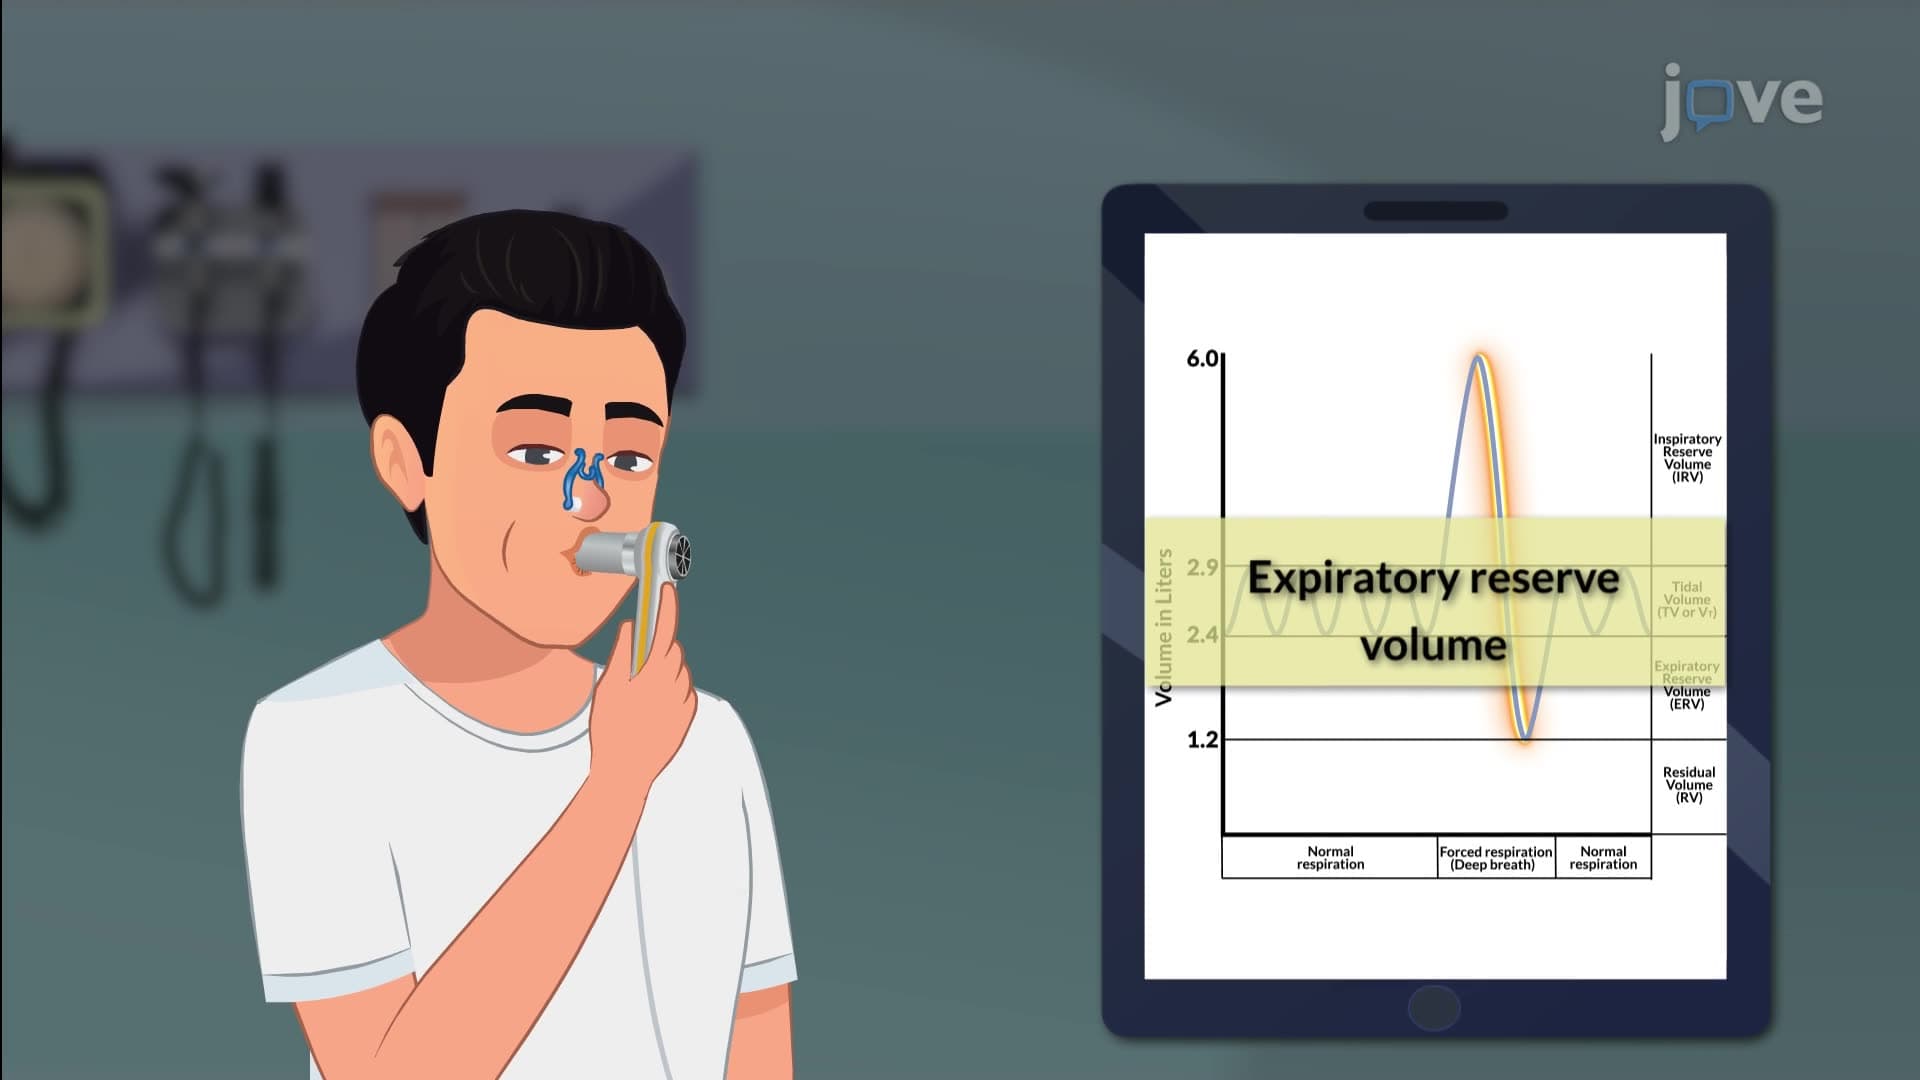
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 00:56
One-Compartment Open Model for IV Bolus Administration: Estimation of Clearance
In the one-compartment open model for intravenous (IV) bolus administration, clearance is estimated by dividing the elimination rate by the plasma drug concentration. This equation leverages the elimination rate constant and the apparent...