Lumbosacral spondylodiscitis following superior hypogastric nerve block performed during uterine artery embolization: a case report
Related Experiment Videos
Hamidreza Rouientan1, Dina Seyedi1, Shahram Akhlaghpoor2
1Department of Interventional Radiology, Pardis Noor Medical Imaging and Cancer Center, Pardisnoor Niloo, No. 30, Farokhi Yazdi Ave, Pasdaran, Tehran, Iran.

Background:
Uterine artery embolization (UAE) is a minimally invasive, uterus-preserving treatment for symptomatic uterine fibroids with a low infection rate, and post-procedural infections are typically confined to the pelvis. Extra-pelvic deep infections are exceptionally rare. We describe an unusual delayed presentation of lumbosacral spondylodiscitis following an otherwise uncomplicated UAE.
Case Presentation:
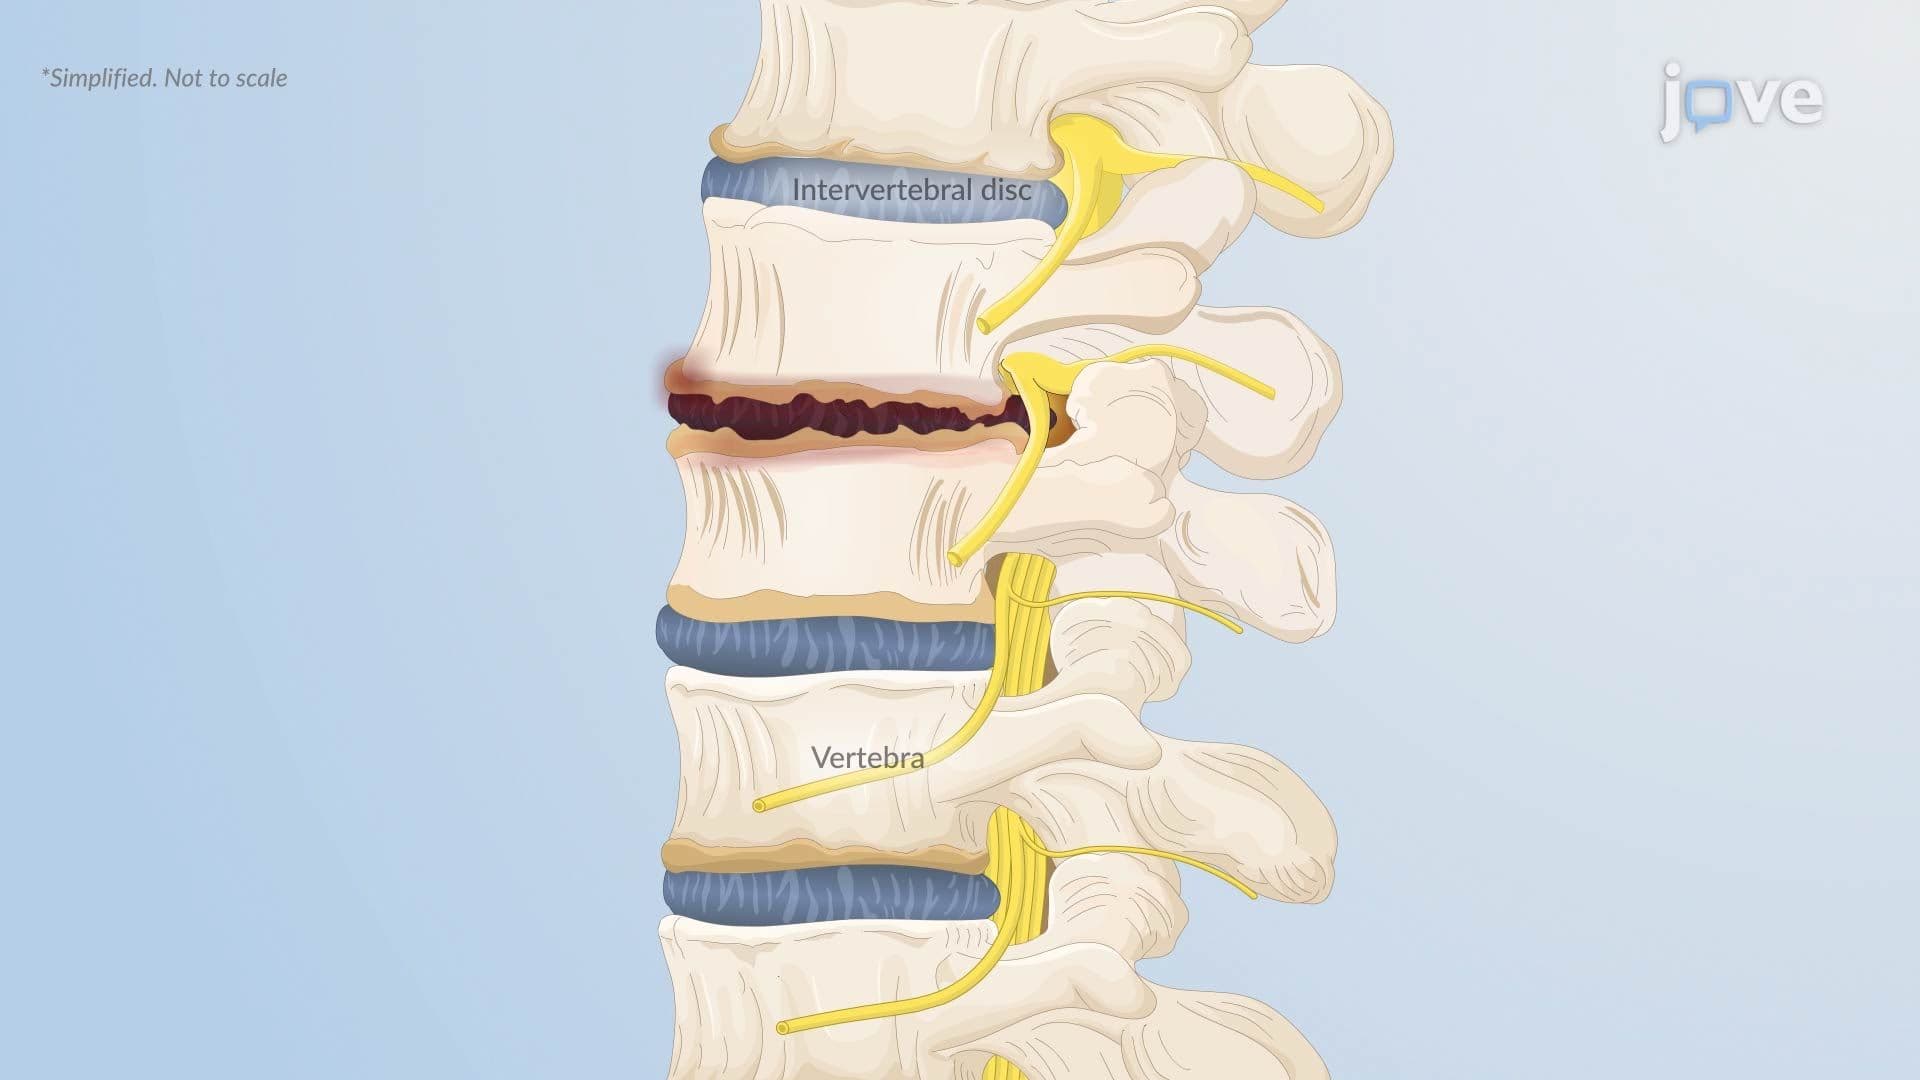
A 30-year-old woman with symptomatic uterine fibroids underwent bilateral UAE. Embolization was performed with 700-900 μm microspheres to angiographic stasis, with adjunct superior hypogastric nerve block (SHNB) for analgesia via an anterior suprapubic approach. Recovery was initially uneventful; however, new low back pain developed approximately 1 week post-procedure. At day 20, inflammatory markers were mildly elevated with a normal white blood cell count, and lumbar magnetic resonance imaging (MRI) demonstrated no abnormality. Despite conservative management, pain progressively worsened with functional limitation. Repeat MRI at 7 weeks revealed L5-S1 spondylodiscitis. After antibiotic therapy, follow-up MRI at 11 weeks demonstrated progression with abscess formation, prompting referral to neurosurgery for further management.
Conclusion:
Persistent or progressive back pain after UAE, particularly when inflammatory markers rise, warrants reassessment and consideration of spondylodiscitis. Early MRI may be normal; repeat MRI is appropriate when symptoms persist or worsen. This case highlights spondylodiscitis as a rare but serious complication in the procedural setting, with SHNB representing a possible contributory mechanism.