Related Experiment Video
Updated: Jun 16, 2026

Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
Radiological features and formation mechanisms of periosteal proliferation in osteogenesis imperfecta type V
1Department of Radiology, Peking Union Medical College Hospital, Chinese Academy of Medical Sciences and Peking Union Medical College, Shuaifuyuan No. 1, Dongcheng District, Beijing 100730, China.

Aim:
This study investigates the radiological features and formation mechanisms of periosteal proliferation caused by disordered osteogenesis and mineralisation in osteogenesis imperfecta (OI) type V.
Materials And Methods:
A total of 24 patients (mean age: 6.3 ± 5.2 years; 62.5% females) underwent X-ray and dual-energy X-ray absorptiometry, yielding 134 images of 180 long bones. Bones were categorised into fracture and nonfracture groups. Fracture patterns and the subsequent healing process during follow-up were assessed. Periosteal proliferation morphology (thin, lamellated, solid, thick, circular, butterfly, shell, spindle, and irregular), boundary (well defined or ill defined), distribution (focal or diffuse), thickness, bone enlargement, bone cortex, and soft-tissue mass were assessed. Relevant clinical and laboratory data on bone metabolism and inflammation were also recorded.
Results:
Fractures healed gradually through callus formation (median follow-up: 2 years). All periosteal proliferations showed intact cortex and no soft-tissue mass; the solid type accounted for 63.8%. Ill-defined proliferation thickness was 2.3 times greater than well-defined (10.7 [5.1, 46.4] and 4.6 [3.5, 7.7], respectively; P = 0.003). Diffuse proliferation more often accompanied bone enlargement than focal (36.7% vs. 7.8%, P = 0.001) and progressed more frequently (73.7% vs. 42.9%, P = 0.030). The patients with elevated C-reactive protein (CRP) or erythrocyte sedimentation rate (ESR) are more likely to exhibit diffuse periosteal proliferation than the normal inflammatory markers (66.7% vs 0%), although not statistically significant (P = 0.147).
Conclusion:
OI type V shows delayed fracture healing or nonunion. Nonfracture cases present unique periosteal proliferation. Diffuse type correlates with bone enlargement and progression. Inflammatory markers' role needs further confirmation.
More Related Videos
 06:53
A Rat Tibial Growth Plate Injury Model to Characterize Repair Mechanisms and Evaluate Growth Plate Regeneration Strategies
Published on: July 4, 2017
 05:10
Improved Methodology for Studying Postnatal Osteogenesis via Intramembranous Ossification in a Murine Bone Marrow Injury Model
Published on: February 7, 2025
Related Concept Videos
 01:29
Bone Formation by Intramembranous Ossification
The process begins when mesenchymal cells in the embryonic skeleton gather together and differentiate into osteogenic cells, which then develop into...
 01:24
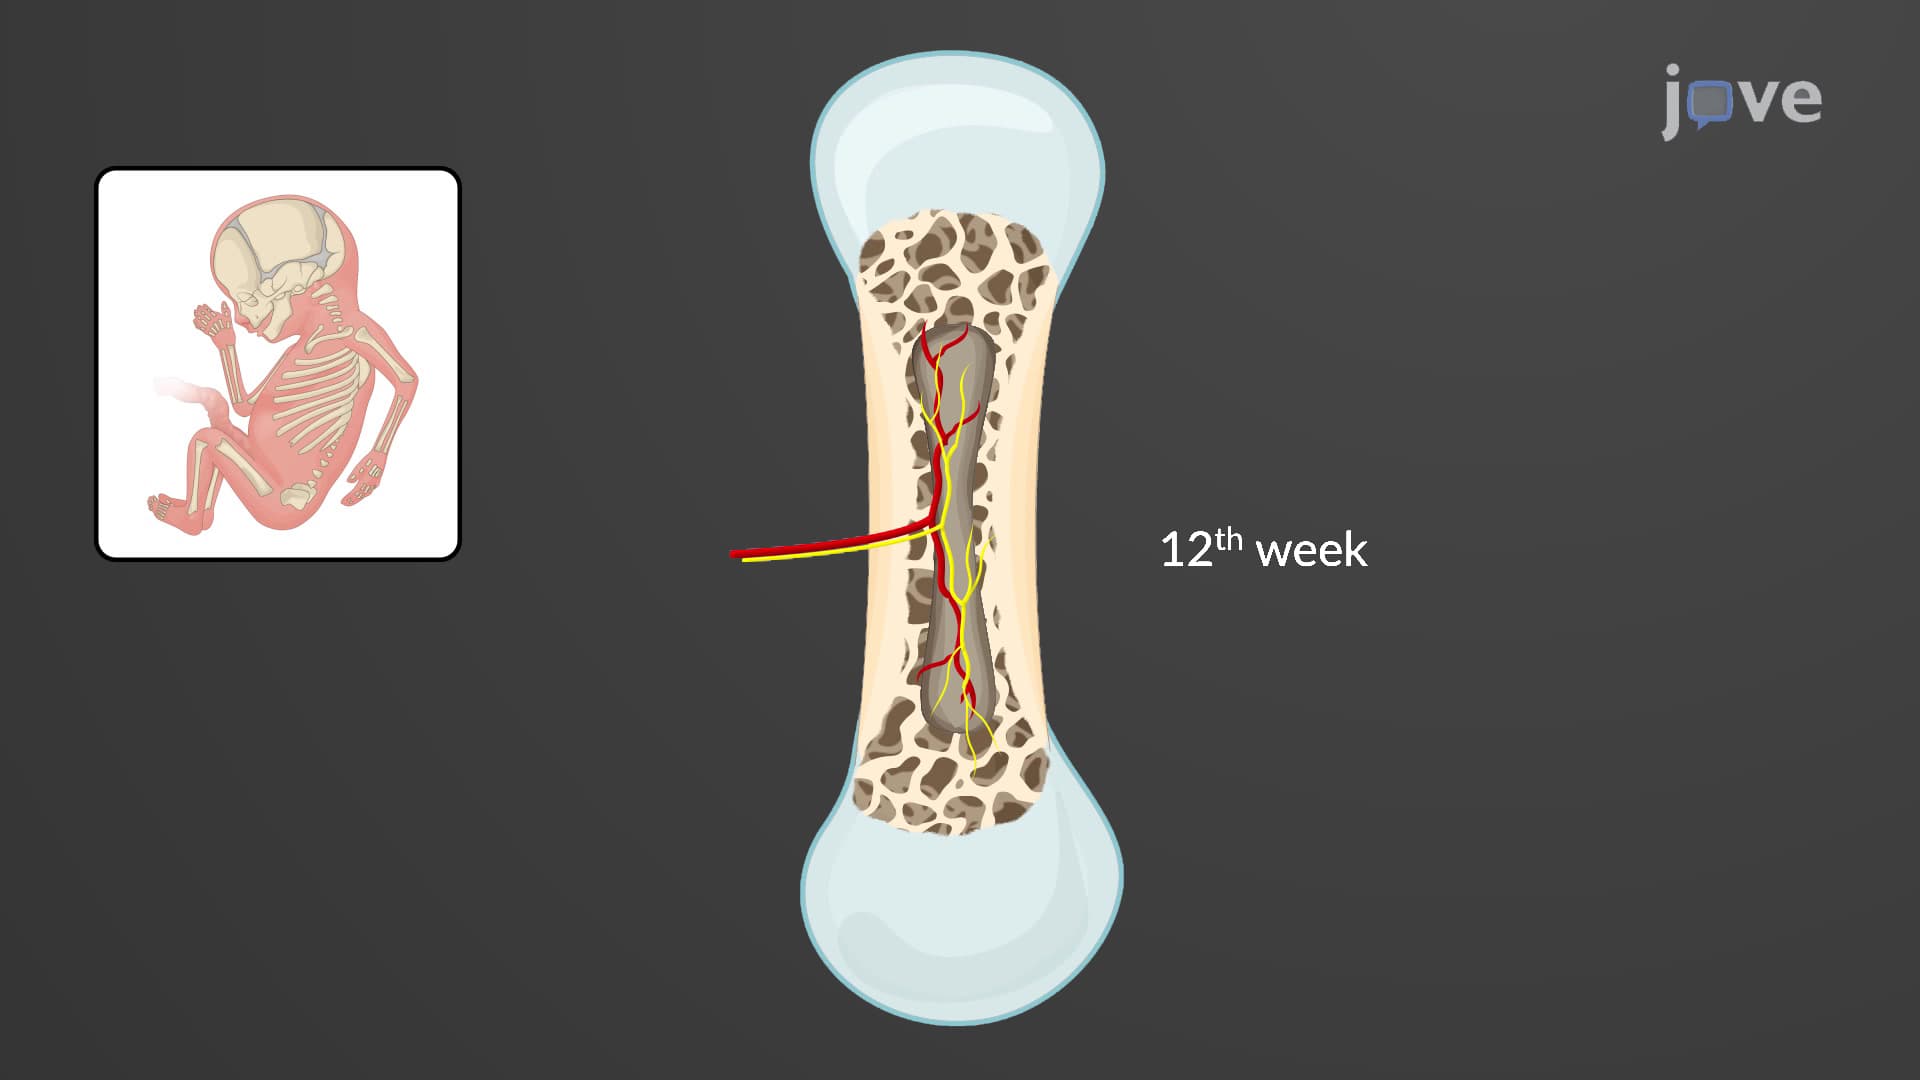
Bone Formation by Endochondral Ossification
 01:40
Bone Remodeling
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:30
Bone Cells and Tissue
Osteoblasts and Osteocytes
The osteoblast is the bone cell responsible for forming new bone tissue. It is found in the growing portions of bone, including the periosteum and...
 01:31
Osteoclasts in Bone Remodeling