Related Experiment Video
Updated: Jun 16, 2026
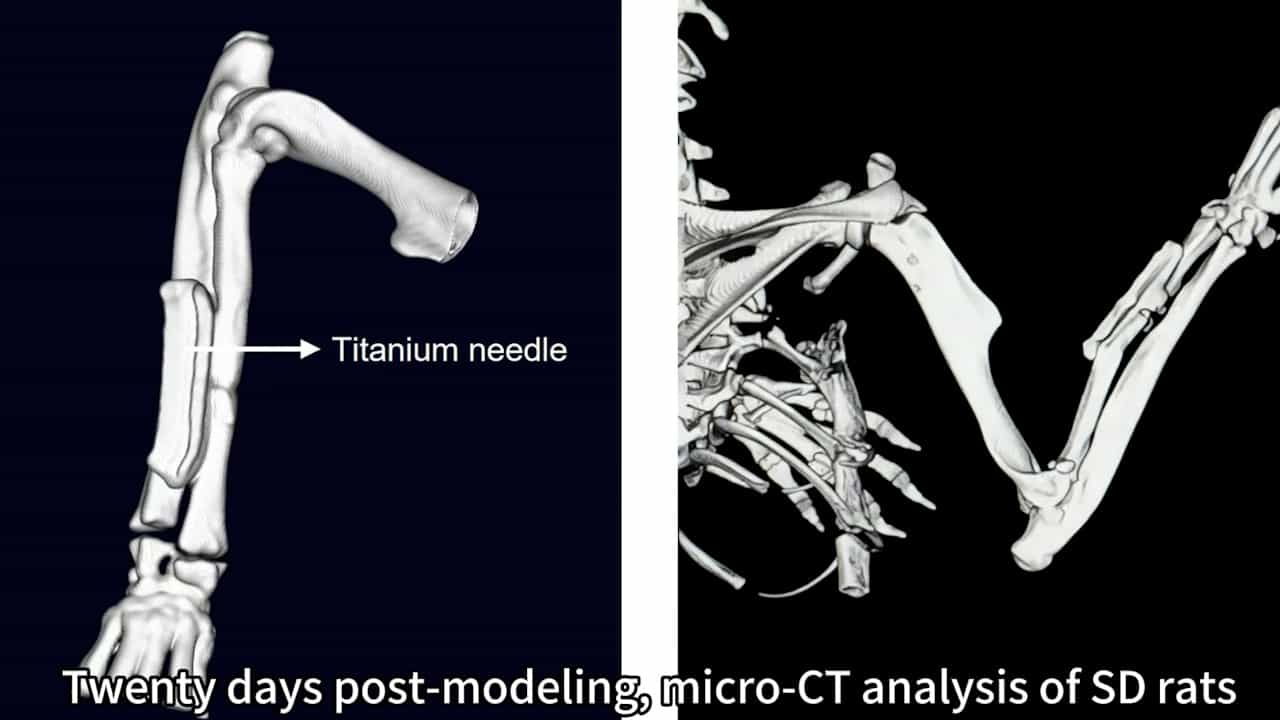

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Refracture after surgical management of pediatric diaphyseal forearm fractures: a retrospective analysis
Chen Zhang1, Zhenkun Gu1, Jianglong Xu1
1Department of Orthopedics, Shenzhen Children's Hospital, Shenzhen, China.

Purpose:
Pediatric diaphyseal forearm fractures are common, and refracture represents a significant postoperative complication. This study aimed to investigate risk factors for refracture following pediatric diaphyseal forearm fractures and to delineate the clinical characteristics and trends of these refractures.
Methods:
A retrospective analysis was conducted on the medical records of 1,593 patients with diaphyseal forearm fractures treated at our hospital between January 1, 2019, and January 1, 2024. Data collection included demographics, fracture characteristics, and surgical details. Patients were divided into refracture and non-refracture groups. Univariate analysis was performed to explore factors associated with refracture. Clinical features of refracture, including injury mechanisms and timing, were also described.
Results:
Among 1,593 children with diaphyseal forearm fractures, 73 cases (4.58%) experienced refracture. The median time to refracture was 135 days (range: 35-362 days), with 47.95% occurring between 3 and 6 months post-initial fracture. Routine daily activities were the cause of injury in 64.38% of refracture cases. Univariate analysis revealed significant differences between the refracture and non-refracture groups regarding midshaft fracture location (P = 0.01), shorter initial immobilization (P = 0.04), and the presence of intramedullary fixation tip exposure (P = 0.02). The two groups showed no significant differences in demographic characteristics, including age, gender, body weight, and height, or in initial fracture characteristics or surgical methods.
Conclusion:
The incidence of diaphyseal forearm refractures in our cohort was 4.58%, with the highest risk occurring between 3 and 6 months post-fracture-often related to daily activities. Variables associated with refracture in univariate analysis included midshaft fracture location, exposed intramedullary fixation tips, and shorter initial immobilization. Clinicians should consider burying intramedullary fixation tips, and extending postoperative protection with bracing after cast removal.

