Related Experiment Video
Updated: Jun 16, 2026
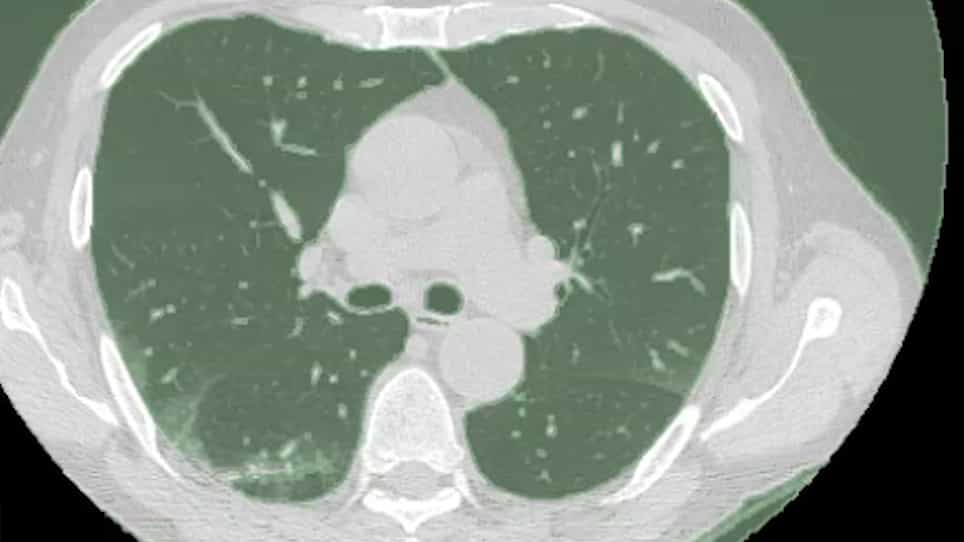

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Pulmonary ground-glass opacity associated with cystic airspace: clinicopathological features and aggressiveness
Ziwen Yu1,2, Jianfu Li1,2, Hongsheng Deng1,2
1Department of Thoracic Surgery and Oncology, the First Affiliated Hospital of Guangzhou Medical University, Guangzhou, China.

Background:
Pulmonary ground-glass opacity (GGO) is often considered to have inert biological behavior. However, whether the clinicopathological features and aggressiveness of GGO associated with cystic airspace (GGO-A) differ from GGO associated without cystic airspace (GGO-nA) remains unknown. This study aimed to compare the clinicopathological features and aggressiveness of GGO-A with GGO-nA.
Methods:
This retrospective study included patients with GGOs [lesion size: 0.5-2.0 cm, consolidation-to-tumor ratio (CTR) ≤50%] from 2017 to 2021. Patients were divided into GGO-As and GGO-nAs. Chi-squared, Mann-Whitney test, Kaplan-Meier analyses and Logistic regression were utilized for data analysis.
Results:
A total of 818 patients (266 with GGO-As and 552 with GGO-nAs) were enrolled. Compared to patients with GGO-nAs, patients with GGO-As had distinct clinical features: male [odds ratio (OR) =5.588, P<0.001], without family history of cancer (OR =5.121, P<0.001), with emphysema pulmonum (OR =3.228, P=0.003) and with pulmonary bullae (OR =2.634, P<0.001). Compared to GGO-nAs, GGO-As had more invasive adenocarcinomas (IAs) (75.8% vs. 39.3%, P<0.001) and micropapillary subtypes (17.0% vs. 5.7%, P=0.09). In addition, KRAS mutated more frequently in GGO-As than GGO-nAs (15.5% vs. 2.5%, P=0.07). Among patients followed up, there were higher frequency of GGO growth (28.9% vs. 17.0%, P=0.02) and shorter median time from baseline to GGO growth (24.0 months vs. not reached, log rank P<0.001) in GGO-As than GGO-nAs. Furthermore, among pure-GGOs and non-smokers, GGO-As were still associated with higher aggressiveness.
Conclusions:
GGO-A showed higher aggressiveness compared to GGO-nA, with more invasive histological subtypes, a higher frequency of KRAS mutations, and faster radiological progression. These findings suggested more proactive surveillance and potentially aggressive clinical management for GGO-As.

Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation, but...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema