Related Experiment Video
Updated: Jun 16, 2026


In Vitro Modeling of Down Syndrome Neurogenesis Using Human-Induced Pluripotent Stem Cells
Published on: March 7, 2025
Immunosuppression in down syndrome regression disorder: a prospective observational cohort study
Jonathan D Santoro1,2, Lilia Kazerooni1, Maeve C Lucas1
1Division of Neurology, Department of Pediatrics, Children's Hospital Los Angeles, Los Angeles, CA 90027, USA.

Down syndrome regression disorder is a severe neuropsychiatric condition for which intravenous immunoglobulin offers partial benefit in many cases. The efficacy of second-line immunosuppressive therapies in those with partial responses to intravenous immunoglobulin (IVIg) remains unclear. This study sought to evaluate the comparative efficacy of B-cell depletion, Janus kinase inhibition, and mycophenolate mofetil as second-line immunosuppressive therapies in individuals with Down syndrome regression disorder. This multicenter, prospective observational cohort study included 126 individuals with Down syndrome regression disorder. Participants were aged 10-30 years and had demonstrated >50% improvement following IVIg on either the Bush-Francis Catatonia Rating Scale or the Neuropsychiatric Inventory Questionnaire, followed by second-line immunosuppression with one of three agents. Participants received B-cell depletion (rituximab or biosimilar; n = 63), Janus kinase inhibitors (tofacitinib or baricitinib; n = 34), or mycophenolate mofetil (n = 29). Treatments were assigned as part of clinical care and not randomized. The primary outcomes were change scores (Δ) on the Bush-Francis Catatonia Rating Scale and the Neuropsychiatric Inventory Questionnaire following immunosuppression. Secondary outcomes included treatment-emergent adverse event rates. All therapies produced symptomatic improvement; however, mean Δ Bush-Francis Catatonia Rating Scale and Δ Neuropsychiatric Inventory Questionnaire scores were greatest with B-cell depletion (mean [standard deviation] Δ Bush-Francis Catatonia Rating Scale: -9.6 [4.1]; Δ Neuropsychiatric Inventory Questionnaire: -16.5 [6.1]) compared with Janus kinase inhibition (Δ Bush-Francis Catatonia Rating Scale: -6.3 [5.0]; Δ Neuropsychiatric Inventory Questionnaire: -12.0 [7.2]) and mycophenolate mofetil (Δ Bush-Francis Catatonia Rating Scale: -3.0 [4.3]; Δ Neuropsychiatric Inventory Questionnaire: -5.7 [6.8]). One-way ANOVA showed significant between-group differences for both Bush-Francis Catatonia Rating Scale (P < 0.001) and Neuropsychiatric Inventory Questionnaire (P < 0.001). Post hoc Tukey tests revealed B-cell depletion to be significantly more effective than mycophenolate mofetil on both outcomes. Adverse event rates were lowest in the B-cell depletion group (2.40 events/patient) compared with Janus kinase inhibition (3.32) and mycophenolate mofetil (4.14) (overall P < 0.001). In individuals with Down syndrome regression disorder who partially respond to intravenous immunoglobulin, second-line immunosuppression with B-cell depletion was associated with the greatest clinical improvement and the most favorable safety profile.
Down syndrome regression disorder is a severe neuropsychiatric condition for which intravenous immunoglobulin offers partial benefit in many cases. The efficacy of second-line immunosuppressive therapies in those with partial responses to intravenous immunoglobulin (IVIg) remains unclear. This study sought to evaluate the comparative efficacy of B-cell depletion, Janus kinase inhibition, and mycophenolate mofetil as second-line immunosuppressive therapies in individuals with Down syndrome regression disorder. This multicenter, prospective observational cohort study included 126 individuals with Down syndrome regression disorder. Participants were aged 10-30 years and had demonstrated >50% improvement following IVIg on either the Bush-Francis Catatonia Rating Scale or the Neuropsychiatric Inventory Questionnaire, followed by second-line immunosuppression with one of three agents. Participants received B-cell depletion (rituximab or biosimilar; n = 63), Janus kinase inhibitors (tofacitinib or baricitinib; n = 34), or mycophenolate mofetil (n = 29). Treatments were assigned as part of clinical care and not randomized. The primary outcomes were change scores (Δ) on the Bush-Francis Catatonia Rating Scale and the Neuropsychiatric Inventory Questionnaire following immunosuppression. Secondary outcomes included treatment-emergent adverse event rates. All therapies produced symptomatic improvement; however, mean Δ Bush-Francis Catatonia Rating Scale and Δ Neuropsychiatric Inventory Questionnaire scores were greatest with B-cell depletion (mean [standard deviation] Δ Bush-Francis Catatonia Rating Scale: -9.6 [4.1]; Δ Neuropsychiatric Inventory Questionnaire: -16.5 [6.1]) compared with Janus kinase inhibition (Δ Bush-Francis Catatonia Rating Scale: -6.3 [5.0]; Δ Neuropsychiatric Inventory Questionnaire: -12.0 [7.2]) and mycophenolate mofetil (Δ Bush-Francis Catatonia Rating Scale: -3.0 [4.3]; Δ Neuropsychiatric Inventory Questionnaire: -5.7 [6.8]). One-way ANOVA showed significant between-group differences for both Bush-Francis Catatonia Rating Scale (P < 0.001) and Neuropsychiatric Inventory Questionnaire (P < 0.001). Post hoc Tukey tests revealed B-cell depletion to be significantly more effective than mycophenolate mofetil on both outcomes. Adverse event rates were lowest in the B-cell depletion group (2.40 events/patient) compared with Janus kinase inhibition (3.32) and mycophenolate mofetil (4.14) (overall P < 0.001). In individuals with Down syndrome regression disorder who partially respond to intravenous immunoglobulin, second-line immunosuppression with B-cell depletion was associated with the greatest clinical improvement and the most favorable safety profile.

Related Concept Videos
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency disorders...
 02:57
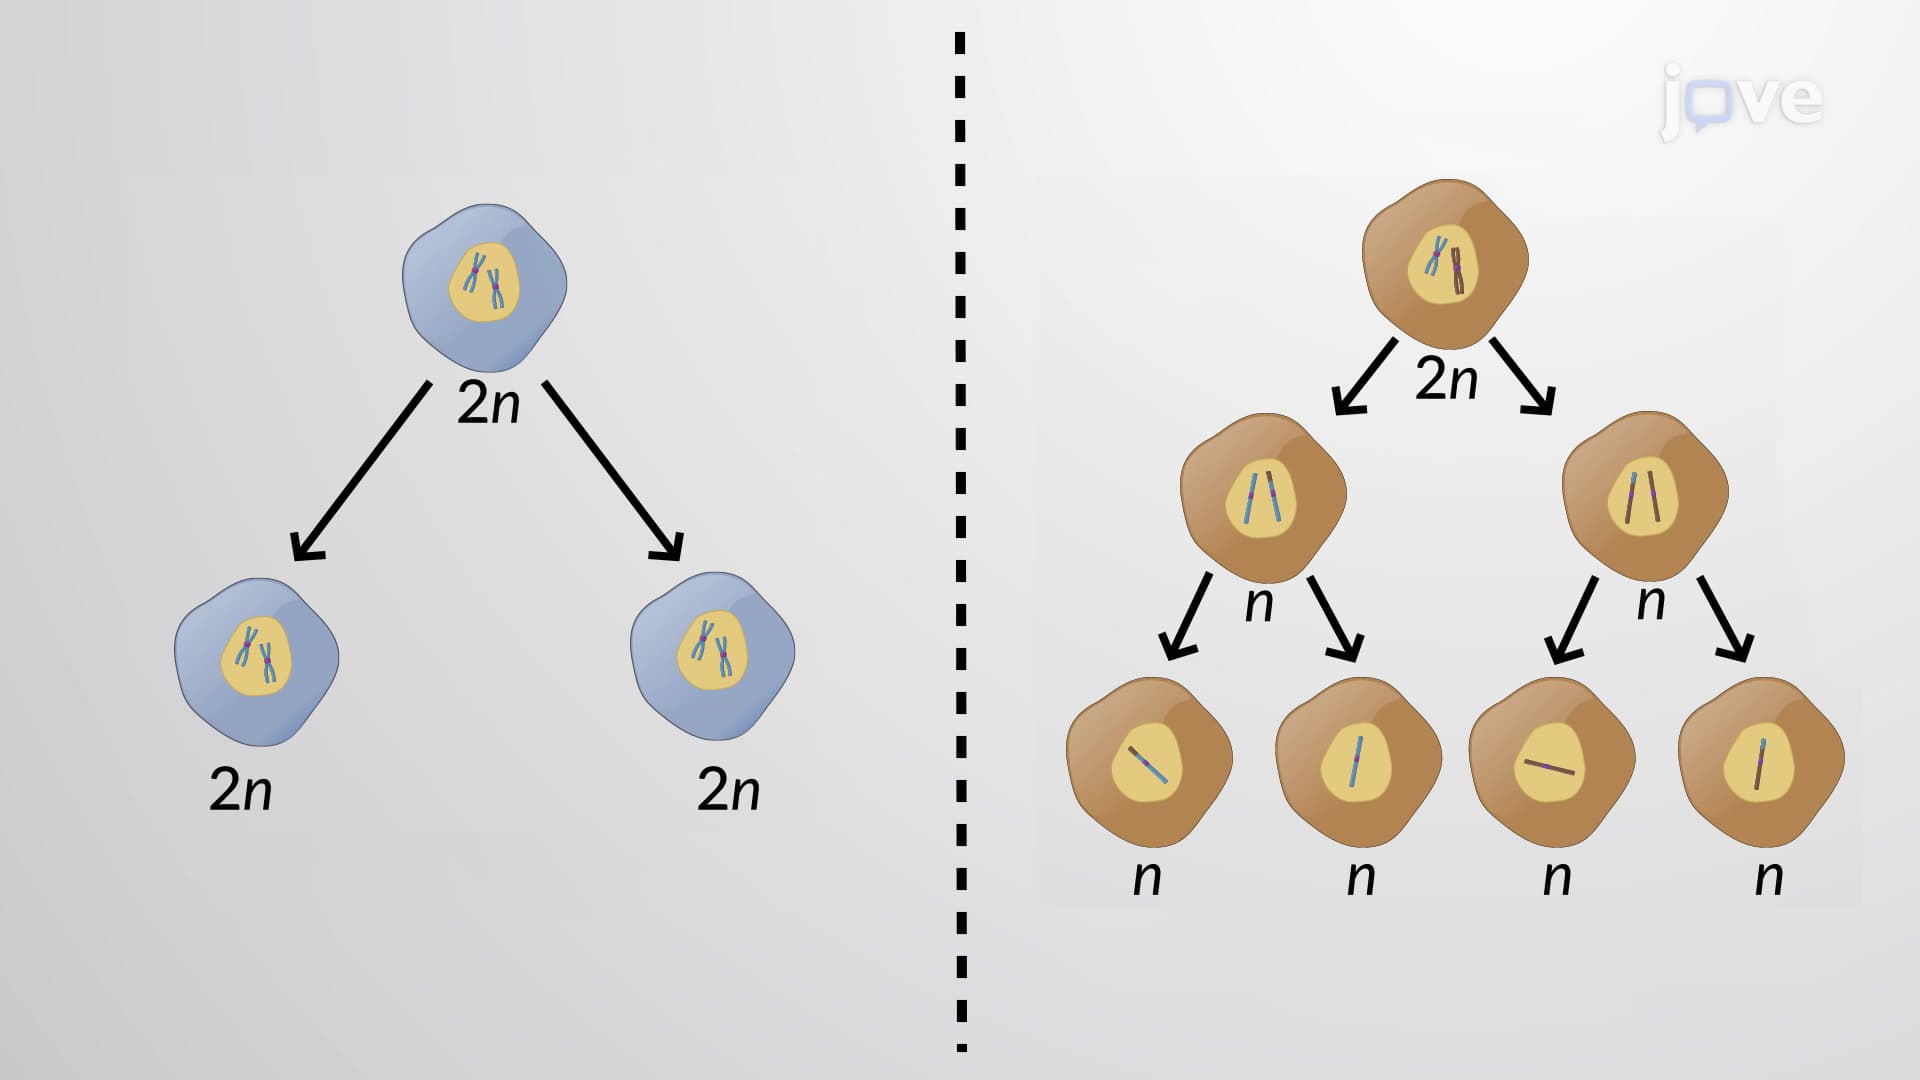
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...