Related Experiment Video
Updated: Jun 19, 2026
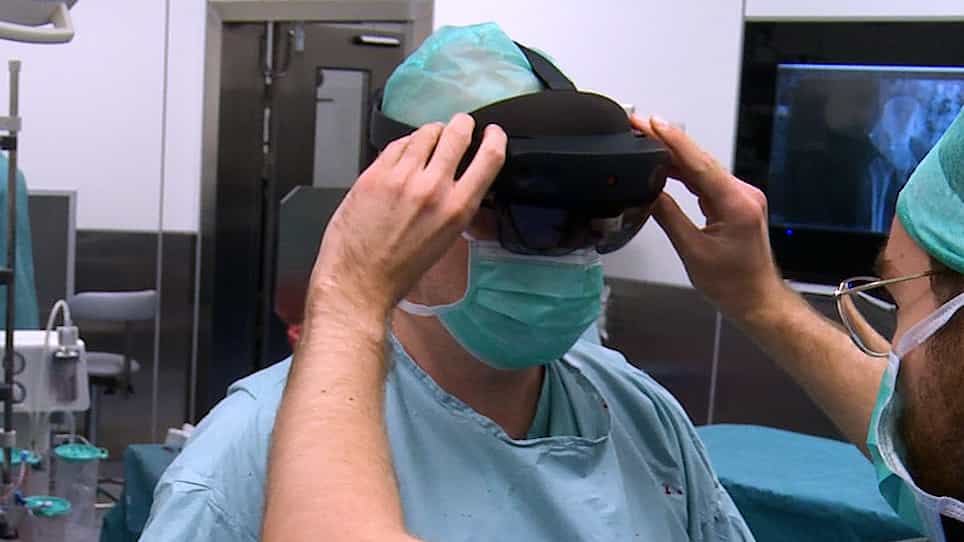

The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Joint-specific measures improve risk adjustment in total knee arthroplasty: A machine learning approach
Dirk Müller1, Amna Gillani2, Michael T Hirschmann3
1Department of Orthopaedic Surgery, TUM Klinikum Rechts der Isar, TUM School of Medicine and Health, Technical University of Munich, Munich, Germany.

Purpose:
Accurate risk adjustment in total knee arthroplasty (TKA) is essential for outcome prediction and quality assessment. Most existing prediction models rely solely on patient demographics and comorbidities and do not account for joint-specific pathology. This study evaluated whether incorporating radiographic and clinical joint-specific parameters improves machine learning (ML)-based risk adjustment and prediction of postoperative complications and residual pain following TKA.
Methods:
A retrospective analysis was performed on 1207 primary TKA procedures conducted at a single academic centre between 2018 and 2022. Three outcomes at 1 year were analysed: residual pain (Visual Analogue Scale [VAS] ≥ 4), any complications and major complications. Predictor variables included patient-related factors (e.g., age, body mass index, American Society of Anesthesiologists score, comorbidities) and joint-specific parameters (e.g., limb alignment, range of motion) derived from preoperative radiographs and clinical assessment. Binary classification models were developed using a stacked gradient-boosting ensemble combining XGBoost and CatBoost. For each outcome, models using patient-specific variables alone were compared with models incorporating both patient- and joint-specific variables. Model performance was evaluated using accuracy, sensitivity, specificity and area under the receiver operating characteristic curve (AUC).
Results:
Incorporating joint-specific parameters significantly improved prediction of complications. For major complications, the combined model achieved an AUC of 0.74 compared with 0.66 using patient variables alone. For any complications, the AUC increased from 0.64 to 0.72. No improvement was observed for predicting residual pain. The most influential joint-specific predictors included prior septic surgery, large bone defects, Kellgren-Lawrence Grade < 3, prior ligament reconstruction and preoperative knee flexion < 70°.
Conclusion:
Inclusion of joint-specific features improved ML-based prediction of postoperative complications following TKA, but did not improve prediction of residual pain. These findings suggest that joint-specific parameters may enhance risk adjustment for postoperative complications in TKA.
Level Of Evidence:
Level III retrospective cohort study.
More Related Videos
 07:33
In Vitro Application of a Wireless Sensor in Flexion-Extension Gap Balance of Unicompartmental Knee Arthroplasty
Published on: May 5, 2023
 06:28
Anterior Cruciate Ligament Transection and Synovial Fluid Lavage in a Rodent Model to Study Joint Inflammation and Posttraumatic Osteoarthritis
Published on: September 2, 2025