Related Experiment Video
Updated: Jun 17, 2026


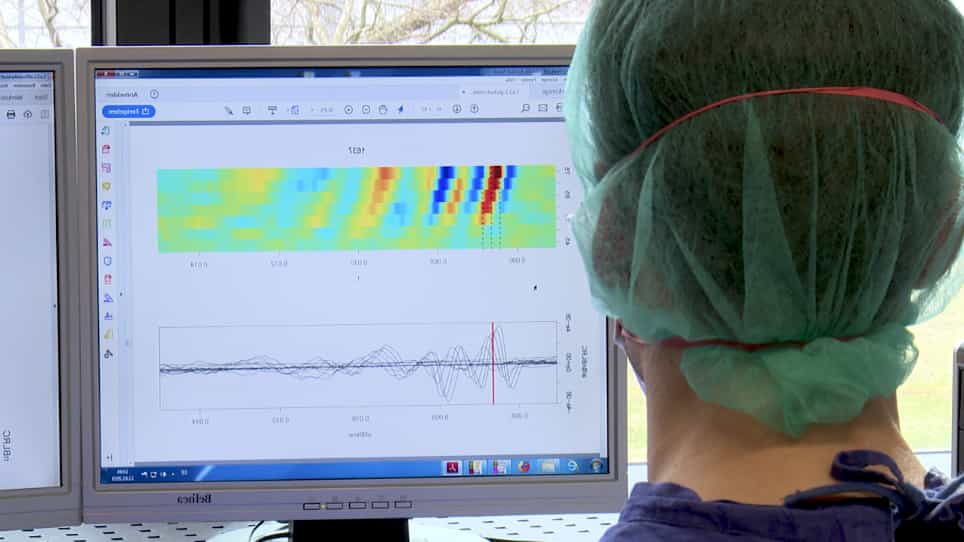
Semi-Automated Analysis of Peak Amplitude and Latency for Auditory Brainstem Response Waveforms Using R
Published on: December 9, 2022
Predicting abnormal auditory brainstem response outcomes using risk factors
Maria Leno1, Sima Sharghi2, Julie L Wei3
1Division of Otolaryngology/Audiology, Akron Children's Hospital, 1 Perkins Square, Akron, OH, 44308, USA.

Background:
Auditory brainstem response (ABR) testing diagnoses hearing loss in children unable to complete behavioral audiometry. ABR evaluations have been scheduled for 60-min operating room (OR) blocks regardless of hearing loss risk, resulting in poor utilization and prolonged wait times. At Akron Children's Hospital, wait times averaged 82 days. However, 63% of cases demonstrated normal hearing and were completed in under 60 min. No validated tool predicts abnormal ABR results prior to scheduling. A predictive model based on clinical risk factors could optimize OR block utilization and improve access.
Methods:
We conducted a retrospective study of 239 children who underwent sedated ABR testing between February 2024 and September 2025. Risk factors collected from electronic health records included autism, cardiac diagnosis, congenital CMV, hyperbilirubinemia, neurologic diagnoses, trauma, universal newborn hearing screening (UNHS) referral, family history of hearing loss, parental speech/hearing concern, NICU stay, prematurity, and syndrome diagnosis. Candidate models were compared using stratified 4-fold cross-validation; logistic regression was selected as the primary model and evaluated using discrimination, calibration, and clinical utility.
Results:
The model demonstrated moderate discrimination (AUC ≈ 0.68). UNHS referral and syndrome diagnosis showed increased abnormal ABR risk. Autism diagnosis was associated with decreased risk. At a 35% risk threshold, the model identified 53% of abnormal cases with 75% specificity and 49% positive predictive value.
Conclusions:
A pre-test risk stratification model can moderately discriminate children at higher risk for abnormal ABR, with potential to improve OR block utilization, patient access, and workflow efficiency.