Related Experiment Video
Updated: Jun 17, 2026
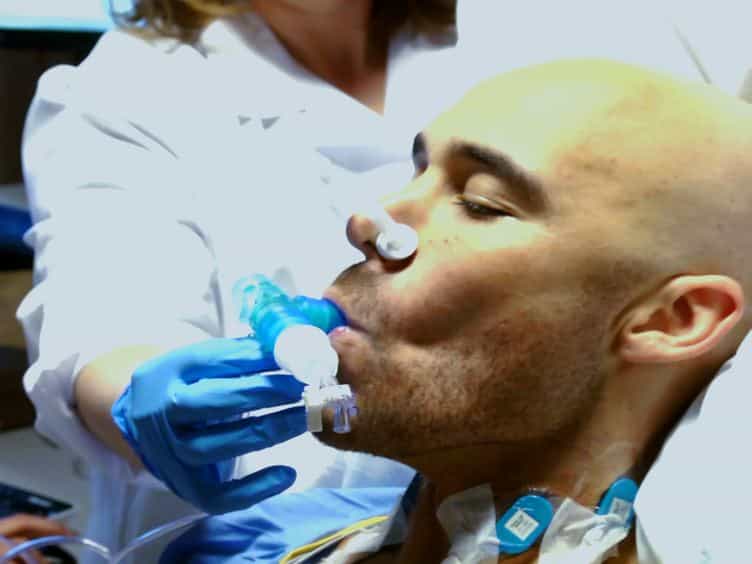

Evaluation of Respiratory Muscle Activation Using Respiratory Motor Control Assessment (RMCA) in Individuals with Chronic Spinal Cord Injury
Published on: July 19, 2013
Clinical profile of responders to adaptive servo-ventilation: a cluster analysis from the READ-ASV European cohort
Jean-Louis Pépin1, Raphael Heinzer2, Sébastien Bailly1
1University Grenoble Alpes, Inserm, CHU Grenoble Alpes, HP2, Grenoble, France.

Background:
Adaptive servo-ventilation (ASV) effectively treats central sleep apnea (CSA), with or without coexisting obstructive sleep apnea (CSA-OSA). However, this is a diverse patient group, and the characteristics of patients who are most likely to benefit from ASV therapy, outside of traditional etiology-based subgroups, are unknown.
Objectives:
To identify clusters of ASV-treated patients based on anthropometric data and comorbidities, and to evaluate the differential response to ASV in these patient clusters.
Methods:
This analysis used data from the READ-ASV registry, which enrolled adults with CSA prescribed ASV from September 2017-March 2021. Evaluations included the Epworth Sleepiness Scale, Functional Outcomes of Sleep Questionnaire, Pittsburg Sleep Quality Index, EuroQol-5-dimension, and sleep study data. Latent class analysis was used to identify patient clusters based on baseline anthropometric data and comorbidities.
Results:
Of 812 patients, 421 (52%) were in Cluster (C) 1 (older, high rate of cardiovascular comorbidities [including stroke], high body mass index [BMI]), 239 (29%) were in C2 (elderly/middle-aged, average-low cardiovascular comorbidity rate, high stroke rate, lower BMI, low diabetes rate), and 152 (19%) were in Cluster 3 (younger, low cardiovascular comorbidity rate, higher BMI, high depression rate). Patients from C3 versus C1/C2 had the highest apnea-hypopnea index at baseline (55 vs. 48/39.5 events/h), were the most symptomatic, had the worst quality of life (QoL), and had the greatest symptomatic and QoL improvement on ASV. They remained the most symptomatic cluster after treatment.
Conclusions:
The identification of subgroups of ASV users with differing responses to therapy and residual symptom burden could facilitate a more personalized approach to ASV prescription and therapy management.
Clinical Trial Registration:
https://www.
Clinicaltrials:
gov; NCT03032029.
Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...