Related Experiment Video
Updated: Jun 17, 2026

Motor and Hippocampal Dependent Spatial Learning and Reference Memory Assessment in a Transgenic Rat Model of Alzheimer's Disease with Stroke
Published on: March 22, 2016
Mechanisms of increased Alzheimer's disease pathology with R47H and R62H TREM2 variants
Nurun N Fancy1,2, Nanet Willumsen1,2, Vicky M N Chau1,2
1UK Dementia Research Institute at Imperial College, London, UK.

Abstract:
TREM2 plays multiple functional roles in microglia and variants are associated with increased risks of Alzheimer's disease (AD). Genetic polymorphisms reducing expression of the functionally related protein CD33 are protective. Here we have contrasted cellular pathology in human post-mortem brain with and without AD to test mechanisms associated with the differential genetic risks conferred by R47H and R62H TREM2 variants (TREM2var) with and without heterozygosity for the protective rs3865444 CD33 polymorphism. Epistasis between CD33 and TREM2 was demonstrated by relative normalisation of differences in β-amyloid load in TREM2var carriers of the protective CD33 allele. These functional differences were mirrored by differential microglial transcriptomic responses to β-amyloid. Controlling for CD33 genotype, microglial transcriptional responses to increasing β-amyloid were lower for TREM2var, particularly for R47H compared to CV, and there was a reduction in expression of neuroplasticity pathways in TREM2var. R62H microglial signatures were distinguished from those of R47H by upregulation of genes associated with phagocytosis and from CV by differences in inflammatory gene expression including those involved in NF-kappaB signalling. Differential gene expression with increasing β-amyloid also suggested upregulation of β-amyloid production and binding pathways in excitatory neurons in TREM2var heterozygotes. There was lower enrichment for pathways positively adaptive to pathology and expressed in inhibitory neurons from CV samples for both TREM2var. Exploratory bulk tissue proteomics support these observations with evidence for adaptive plasticity in response to β-amyloid pathology in CV tissue not found for the TREM2var, which showed evidence of increased β-amyloid formation and neuroplasticity changes. Together, these results highlight differences in molecular pathology between CV and TREM2var and between the TREM2var risk variants. They highlight mechanisms of AD risk mediated by secondary effects on astroglial and neuronal functions. Demonstration of strong epistasis between TREM2 and CD33 with AD supports the therapeutic potential of modulators of CD33 inhibition or expression.
Insights
Genetic variants in TREM2 increase Alzheimer's disease (AD) risk, while CD33 variants are protective. This study reveals how TREM2 variants interact with CD33, influencing AD pathology and microglial responses to amyloid-beta.
Area of Science:
- Neuroscience
- Genetics
- Immunology
Background:
- Triggering receptor expressed on myeloid cells 2 (TREM2) variants are linked to increased Alzheimer's disease (AD) risk.
- Genetic polymorphisms in CD33, a related protein, are protective against AD.
- Understanding the interplay between TREM2 and CD33 is crucial for elucidating AD pathogenesis.
Purpose of the Study:
- To investigate the mechanisms underlying differential genetic risks conferred by TREM2 variants (TREM2var) in the context of CD33 genotype.
- To contrast cellular pathology and microglial responses to beta-amyloid (Aβ) in human post-mortem brain tissue with and without AD, considering TREM2 and CD33 genotypes.
Main Methods:
- Comparative analysis of human post-mortem brain tissue from AD and control cases.
- Assessment of TREM2 variants (R47H, R62H) and the protective CD33 polymorphism (rs3865444).
- Microglial transcriptomic profiling and bulk tissue proteomics to analyze cellular responses and molecular pathology.
Main Results:
- Epistasis between CD33 and TREM2 was observed, normalizing differences in beta-amyloid load in TREM2var carriers with the protective CD33 allele.
- TREM2 variants showed altered microglial transcriptomic responses to beta-amyloid, with reduced neuroplasticity pathways.
- Differential gene expression indicated potential upregulation of beta-amyloid production and binding in neurons of TREM2var heterozygotes, and reduced adaptive pathways in inhibitory neurons.
Conclusions:
- Distinct molecular pathologies exist between control and TREM2var brains, and between different TREM2 risk variants.
- TREM2 and CD33 exhibit strong epistasis in AD, suggesting therapeutic potential for CD33 modulators.
- Secondary effects on astroglial and neuronal functions contribute to AD risk mediated by TREM2 variants.
More Related Videos


Related Concept Videos
 01:23
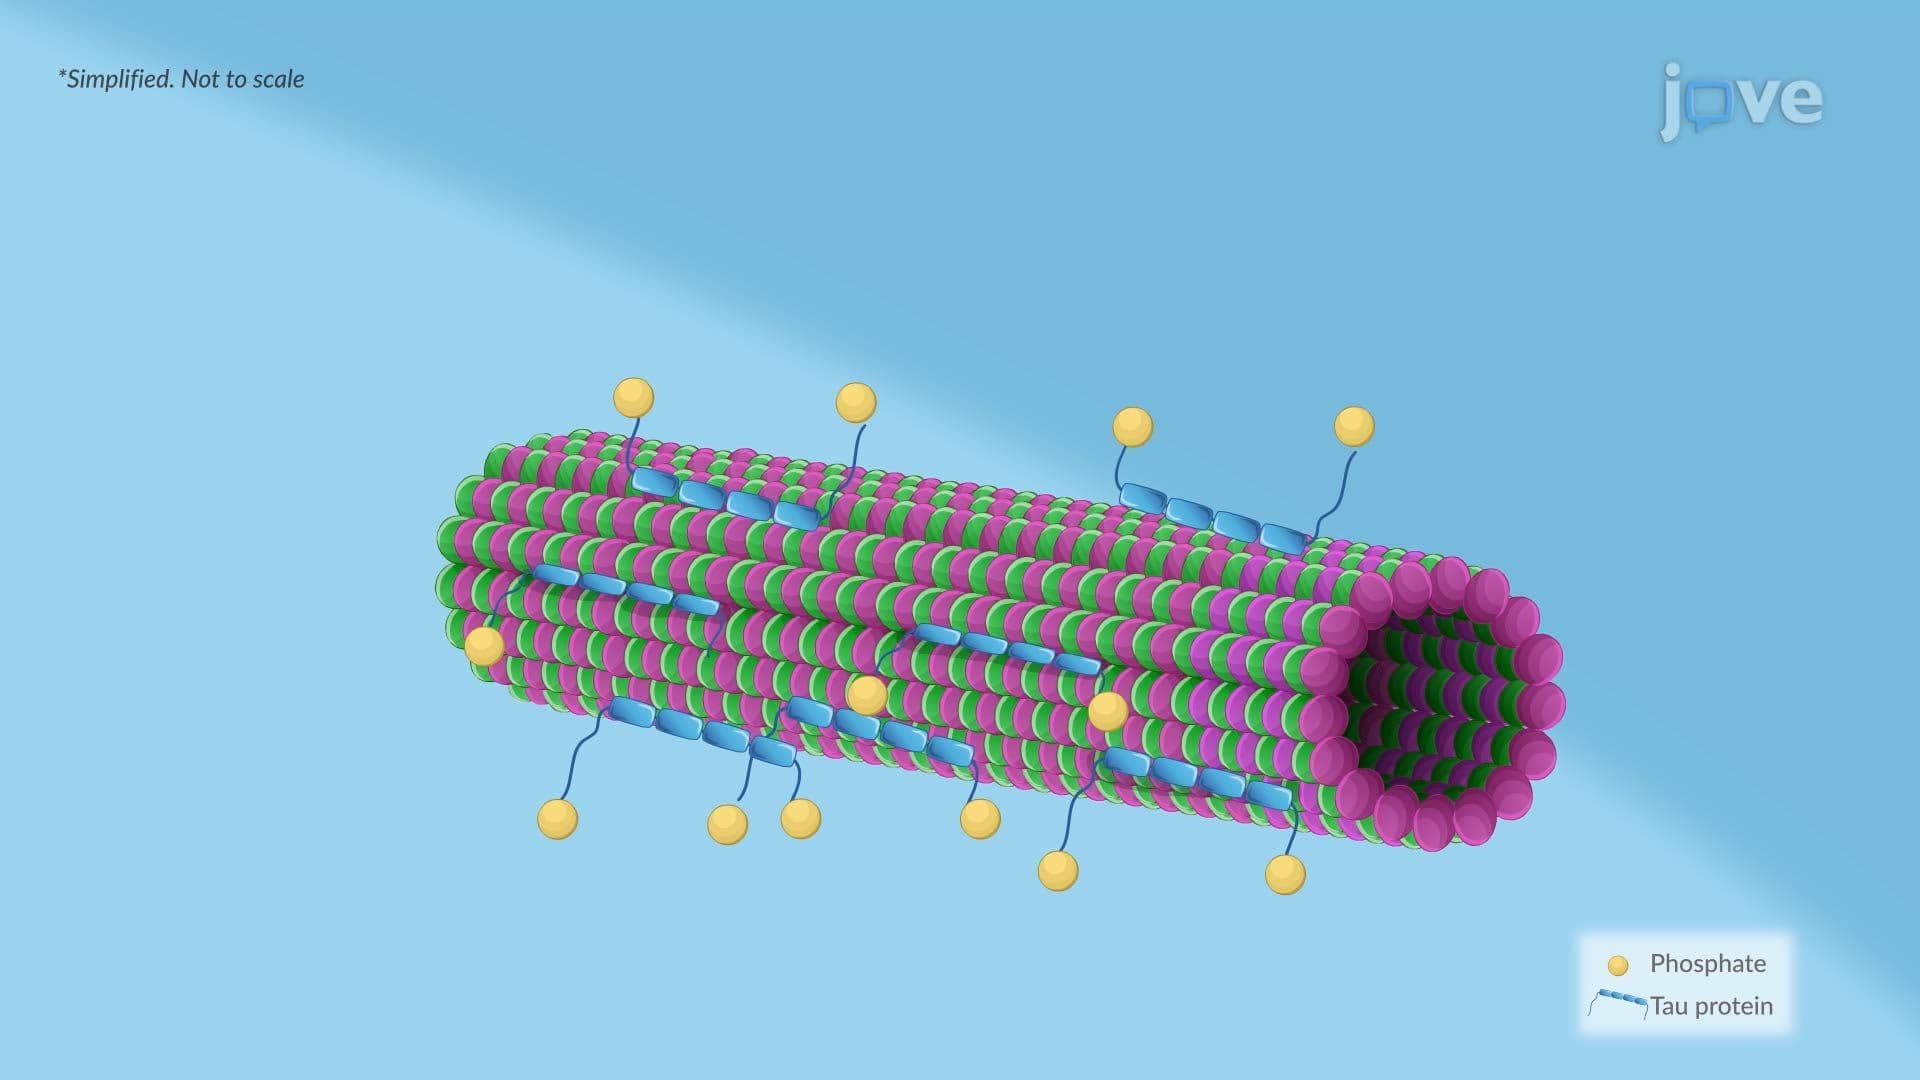
Alzheimer Disease ll: Pathophysiology
 01:29
Alzheimer Disease l: Introduction
 01:24
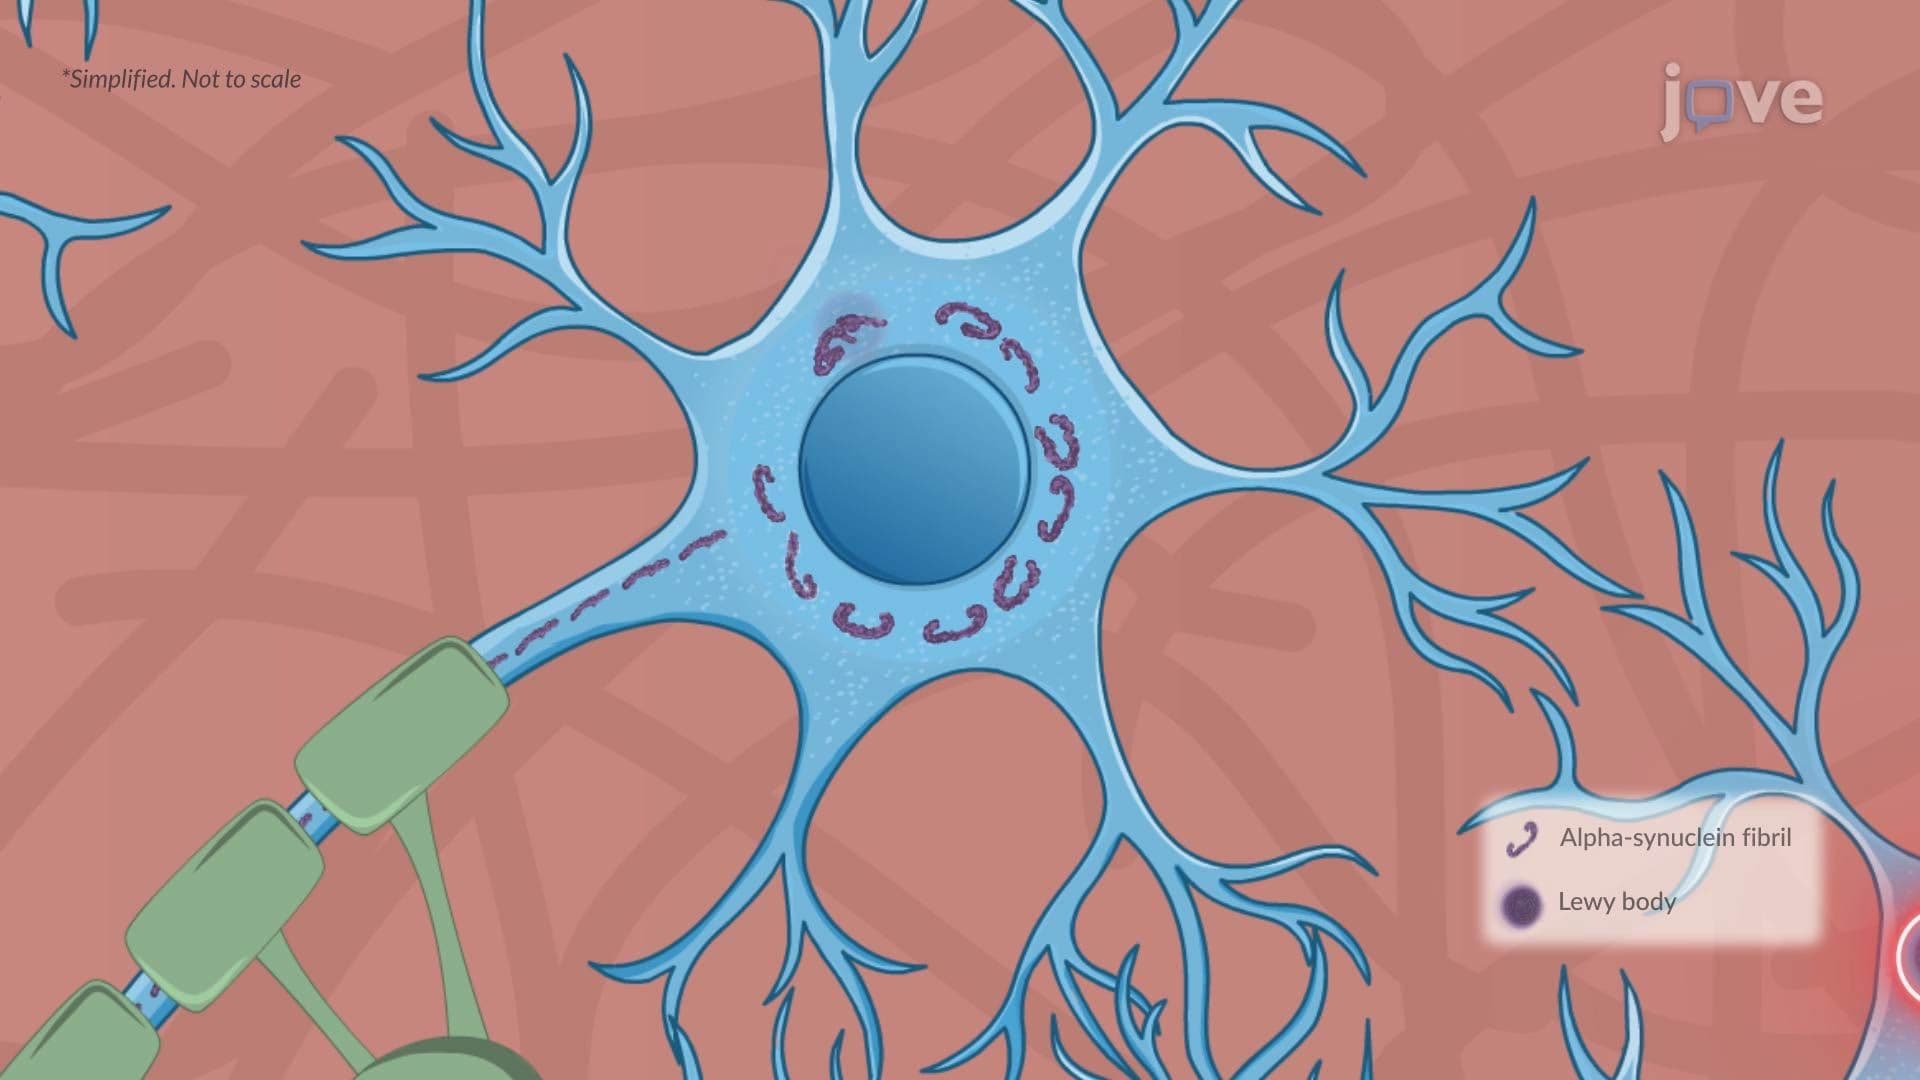
Parkinson Disease ll: Pathophysiology
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 03:03
Amyloid Fibrils
Amyloid deposits were observed as early as 1639 in the liver and the spleen. In 1854, Rudolph Virchow performed iodine staining, normally used to...
 01:21
Huntington Disease l: Introduction