Related Experiment Video
Updated: Jun 17, 2026


Midface Hypoplasia and Cranial Base Morphology in Syndromic Craniosynostosis: A Comparative Analysis Study Using a Predictive Regression Model
Published on: November 4, 2025
Age-stratified study on symptoms of upper airway obstruction and craniofacial development in children
Hui Qu1, Chang Liu1, Jing Sun1
1Department of Otolaryngology, The Second Affiliated Hospital of Dalian Medical University, Dalian, 1116000, P.R. China.

Insights
Upper airway obstruction (UAO) symptoms in children aged 3-14 are linked to craniofacial development changes, with distinct patterns observed across age groups. Early identification and tailored interventions are crucial for managing these UAO-associated changes.
Area of Science:
- Pediatric dentistry
- Orthodontics
- Sleep medicine
Background:
- Upper airway obstruction (UAO) in children can impact craniofacial development.
- Understanding these associations is crucial for early diagnosis and intervention.
Purpose of the Study:
- To investigate the association between upper airway obstruction (UAO) symptoms and craniofacial development indicators in children aged 3-14 years.
- To analyze age-specific differences in these associations.
Main Methods:
- 177 children with UAO symptoms were divided into three age groups (3-6, 7-10, 11-14 years).
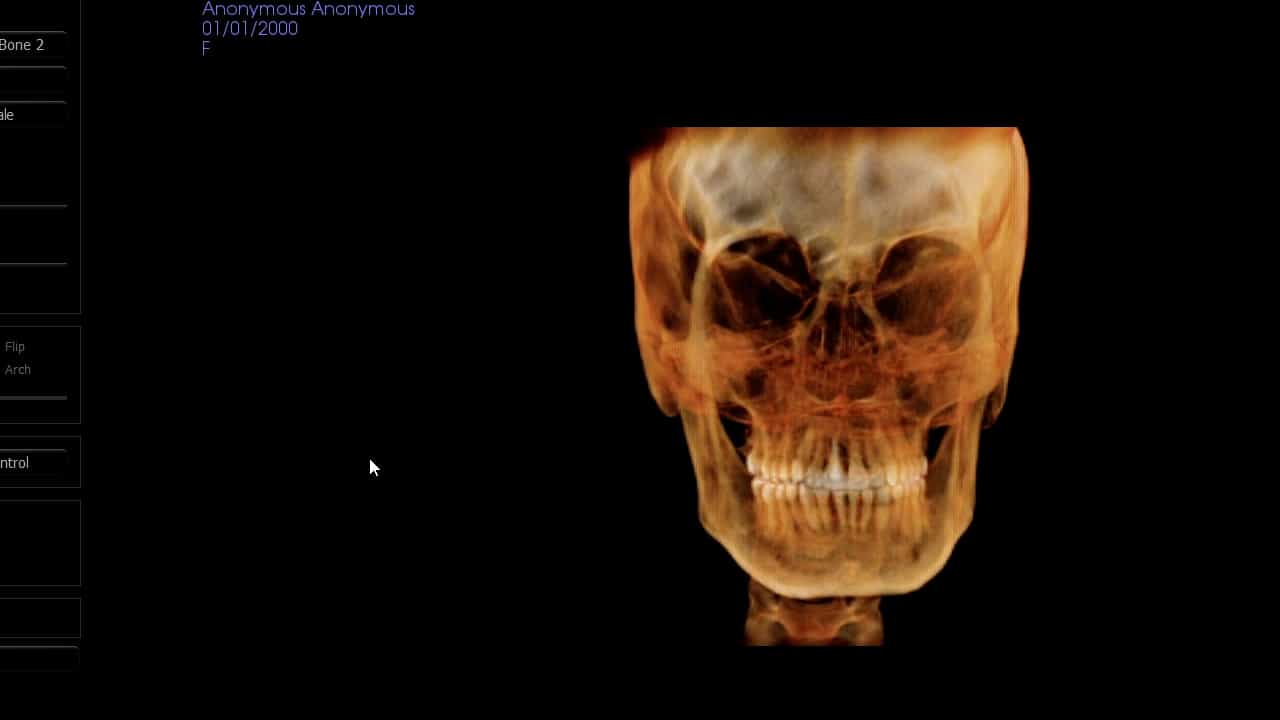
- Cone-beam computed tomography (CBCT) and cephalometric analysis measured 16 craniofacial parameters.
- OSA-18 questionnaire assessed symptom severity; correlation analyses were performed.
Main Results:
- Mouth breathing correlated with vertical and sagittal parameters in younger children (3-6 years).
- UAO symptoms showed varied correlations with craniofacial parameters across age groups (7-10 and 11-14 years).
- Anterior facial height correlated positively with all UAO symptoms in the 3-6 year group.
Conclusions:
- UAO symptoms are associated with altered craniofacial development in children, with significant age-related differences.
- The period from 3 to 10 years appears critical for UAO-associated craniofacial changes.
- Age-specific assessment and intervention strategies are essential for managing high-risk children.
Objective:
To investigate the association between symptoms of upper airway obstruction (UAO) and craniofacial development indicators in children aged 3-14 years, and to analyze specific differences among age groups.
Methods:
A total of 177 children presenting with UAO symptoms (e.g., nasal congestion, snoring, mouth breathing) were enrolled between April 2024 and April 2025. Participants were divided into three age groups: 3-6 years, 7-10 years, and 11-14 years. The OSA-18 questionnaire was completed by guardians to assess symptom severity. Cone-beam computed tomography (CBCT) was performed, and two-dimensional cephalometric analysis was conducted to measure 16 craniofacial parameters, including sagittal (∠SNA, ∠SNB, ∠ANB, ∠SNPog, ∠NP-FH), vertical (∠MP-SN, ∠FH-MP, Y-axis, anterior facial height, posterior facial height), dental (∠U1-SN, ∠U1-NA, ∠U1-L1, ∠L1-NB, ∠L1-MP), and mandibular body length parameters. Correlation analyses were conducted using Pearson's or Spearman's methods in SPSS 22.0.
Results:
3-6-year group: Mouth breathing scores correlated positively with ∠MP-SN, ∠FH-MP, Y-axis angle, anterior facial height, and posterior facial height (r = 0.296, 0.366, 0.233, 0.351, 0.278; P = 0.011, 0.001, 0.046, 0.002, 0.016). All UAO symptoms correlated positively with anterior facial height. 7-10-year group: Symptom duration correlated positively with ∠SNA and ∠U1-L1 (r = 0.256, 0.228; P = 0.021, 0.041) but negatively with ∠U1-SN (r = -0.278, P = 0.012). Apnea scores correlated negatively with ∠NP-FH (r = -0.257, P = 0.020). Choking/gasping scores correlated negatively with ∠SNB (r = -0.238, P = 0.033), while total OSA-18 scores correlated positively with ∠ANB (r = 0.246, P = 0.027). 11-14-year group: Apnea scores correlated positively with ∠L1-NB (r = 0.464, P = 0.030).
Conclusion:
UAO symptoms are correlated with altered craniofacial developmental parameters in children, with notable age-related differences. The period from 3 to 10 years may constitute a critical window of susceptibility to these UAO-associated craniofacial changes. Consistent with existing literature, tonsillar hypertrophy is the most likely primary etiology of UAO in children aged 3-6 years, while adenoid hypertrophy may predominate in those aged 7-10 years. The patterns of craniofacial parameters correlated with UAO symptoms vary distinctly across these age groups. Individualized assessment and intervention strategies tailored to age-specific symptom profiles are essential to enable early identification and targeted management of high-risk children.
Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:28
Physical Assessment of the Respiratory Tract I: Health History
Subjective Data
Subjective data provides vital information about the patient's health history and symptoms. This data is typically collected through interviews in which patients describe their experiences, symptoms, and concerns.
Health history and key...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...