Related Experiment Video
Updated: Jun 17, 2026
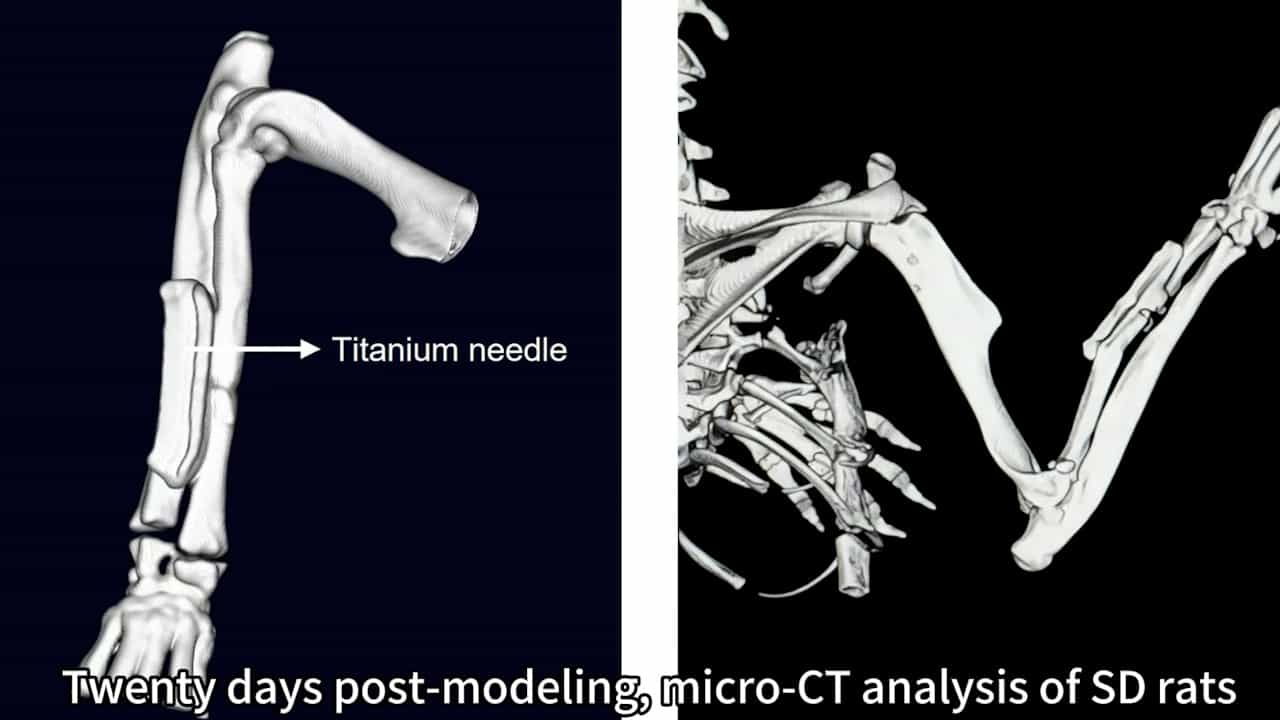

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
The Impact of Socioeconomic Disadvantage and Insurance on Delays in Fixation of Distal Radius Fractures
Mitchell R Koss1, Liam H Wong1, Thomas A Peterson1
1University of California, San Francisco, USA.

Background:
Delay in surgical fixation of distal radius fractures (DRFs) beyond 2 weeks is associated with worse patient-reported outcomes. Although socioeconomic disadvantage affects many orthopedic outcomes, its association with delayed DRF fixation is unclear. We evaluated whether neighborhood disadvantage is associated with surgical delay beyond 14 days.
Methods:
This retrospective study used deidentified electronic health records from multiple academic health systems to identify patients undergoing operative DRF fixation from 2012 to 2024. Multivariable logistic regression identified socioeconomic and demographic factors associated with delay beyond 14 days. Covariates included age, sex, area deprivation index (ADI), race, ethnicity, language, Medicare insurance, and Charlson Comorbidity Index (CCI).
Results:
The cohort included 6639 patients (median age 62 years; 64.7% female; 64.8% white; 90.4% English-speaking; 16.1% Medicare). Median time from diagnosis to surgery was 8 days (IQR 5-13), with 25.3% delayed beyond 14 days. Higher ADI (quartile 3: OR 1.59, 95% CI 1.24 to 1.81; quartile 4: OR 1.47, 95% CI 1.20 to 1.80), Spanish-speaking status (OR 1.48, 95% CI 1.08 to 2.02), higher CCI (OR 1.10, 95% CI 1.06 to 1.13), and Medicare insurance (OR 1.25, 95% CI 1.00 to 1.55) were independently associated with delay.
Conclusions:
Socioeconomic disadvantage, limited English proficiency, comorbidity burden, and Medicare insurance were independently associated with delayed DRF fixation. These findings highlight existing disparities in timely orthopedic care of DRFs and support targeted interventions to improve access.

