Related Experiment Video
Updated: Jun 29, 2026
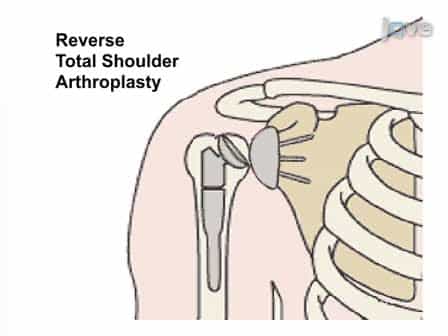

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Primary vs. revision total elbow arthroplasty: an updated analysis of short-term complications and associated factors
James R Satalich1, Matthew S Smith1, Sashrik Sribhashyam1
1Department of Orthopaedic Surgery, Virginia Commonwealth University, Richmond, VA, USA.

Background:
Total elbow arthroplasty (TEA) is an increasingly utilized intervention for a range of pathologies. While the current literature landscape has emphasized reimbursement and long-term outcomes, for example, contemporary comparative data on short-term adverse events between primary and revision TEA remain limited. Therefore, this study updates and expands upon such short-term findings using a large database.
Methods:
In this retrospective cohort study, patients undergoing primary or revision TEA were identified in the American College of Surgeons National Surgical Quality Improvement Program database (2014-2023). Cases with missing data or complex additional/concurrent procedures were excluded. The primary outcome was a composite of any adverse event (AAE), alongside other subgroupings. Statistics included chi-square or Fisher's exact tests, independent t-tests, exploratory multivariable logistic regressions with odds ratios (ORs), and threshold analyses.
Results:
A total of 583 patients underwent primary TEA (mean age = 66.4 ± 13.3; body mass index = 29.9 ± 7.2 kg/m2; 21.3% male) and 179 underwent revision TEA (age = 63.5 ± 12.8; body mass index = 29.9 ± 6.2 kg/m2; 43.6% male). AAE occurred in 8.8% of primary and 6.7% of revision cases (P = .385), with no significant differences in major (7.6% vs. 5.6%), minor (2.4% vs. 0.6%), overall infection (3.3% vs. 1.7%), or composite surgical site infection (2.6% vs. 0.6%) subgroupings. Mean operative time (160.6 ± 60.0 vs. 165.5 ± 88.6 minutes) and total length of stay (2.3 ± 3.3 vs. 1.9 ± 3.6 days) were also all similar between groups (each P > .05). In the primary TEA regression, operative time (OR = 1.007) was the only independent predictor of AAE after multiplicity correction, whereas in revision TEAs, chronic steroid use (OR = 11.124) was the sole predictor (both corrected P = .005). A covariate-adjusted operative time cut point of ∼263 minutes (95th percentile) was identified in primary TEAs, above which AAE increased significantly (7.6% vs. 30.0%; corrected P = .004).
Conclusion:
Across this contemporary 10-year national cohort, primary and revision TEAs appeared to show comparable short-term outcomes. These findings cautiously support focused perioperative counseling and suggest that prolonged operative time becomes clinically relevant only at the upper extremes, though incrementally longitudinal, prospective studies are needed for corroboration.
More Related Videos
 09:01
Treatment of Ankle Osteoarthritis with Total Ankle Replacement Through a Lateral Transfibular Approach
Published on: January 24, 2018
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022