Related Experiment Video
Updated: Jun 18, 2026
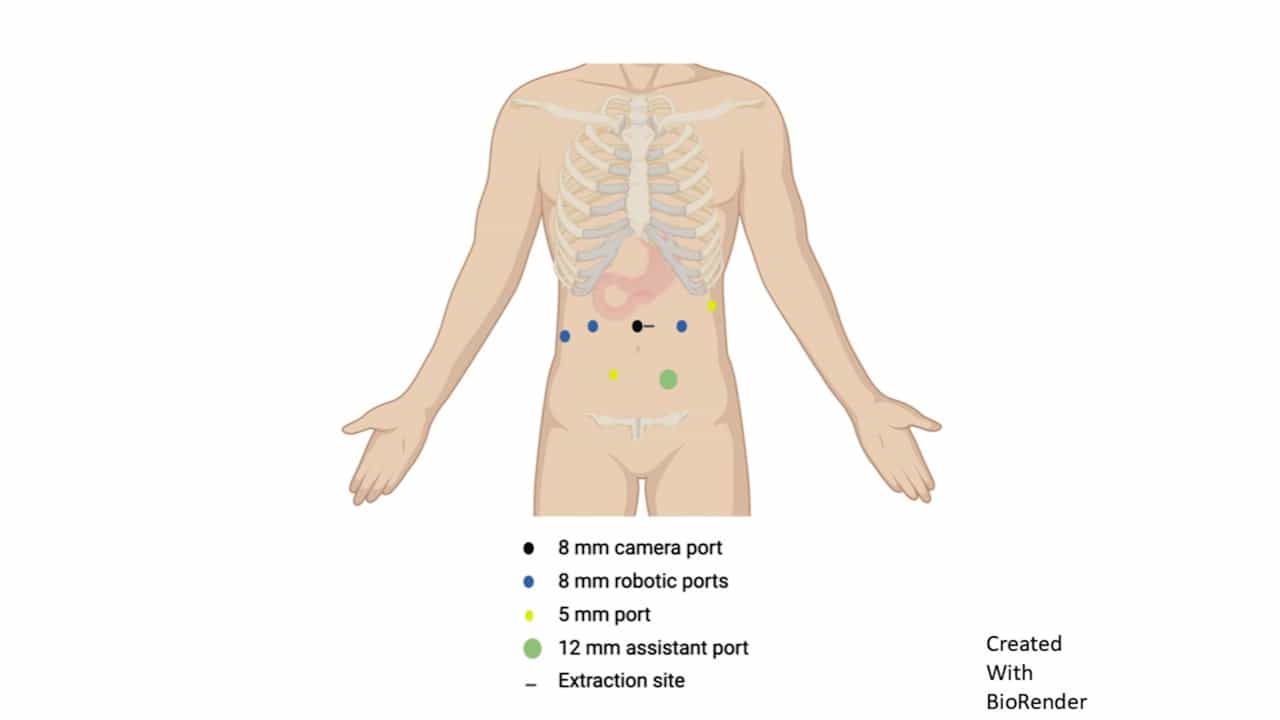

Robotic Duodenal Sleeve Resection for Gastrointestinal Stromal Tumor with Rare Exon 8 KIT Mutation Following Neoadjuvant Imatinib
Published on: April 3, 2026
Losartan-Induced Sprue-Like Enteropathy Presenting With Isolated Ileal Villous Atrophy: A Report of a Rare and
Carlos Berrocal1, Juanita Vasquez Villada1, Pablo Galindo Orrego2
1Internal Medicine, Universidad del Valle, Cali, COL.

Abstract:
Sprue-like enteropathy associated with angiotensin II receptor blockers (ARBs) is a rare cause of chronic diarrhea and malabsorption, typically characterized by villous atrophy and intraepithelial lymphocytosis mimicking celiac disease. Although olmesartan is the most frequently implicated agent, cases associated with other ARBs, including losartan, have increasingly been recognized. A 61-year-old woman with hypertension treated with losartan for three years presented with a three-month history of abdominal pain and chronic diarrhea. Upper endoscopy revealed a macroscopically and histologically normal duodenum. Colonoscopy demonstrated macroscopically normal ileal mucosa; however, ileal biopsies showed villous atrophy and marked intraepithelial lymphocytosis. Celiac serology was negative, infectious causes were excluded, and vitamin B12 deficiency was documented. In the setting of chronic exposure to losartan and after exclusion of alternative etiologies, ARB-associated sprue-like enteropathy was suspected. Losartan was discontinued and replaced with amlodipine, resulting in complete clinical resolution. This case highlights an atypical presentation of losartan-induced sprue-like enteropathy with isolated ileal involvement and a histologically normal duodenum. Clinicians should consider this entity in patients presenting with chronic diarrhea and seronegative villous atrophy, even in the absence of duodenal involvement.
Related Concept Videos
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:20
Inflammatory Bowel Disease IV: Clinical Manifestations
 01:26
Gastritis II: Pathophysiology
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...