Related Experiment Video
Updated: Jun 19, 2026
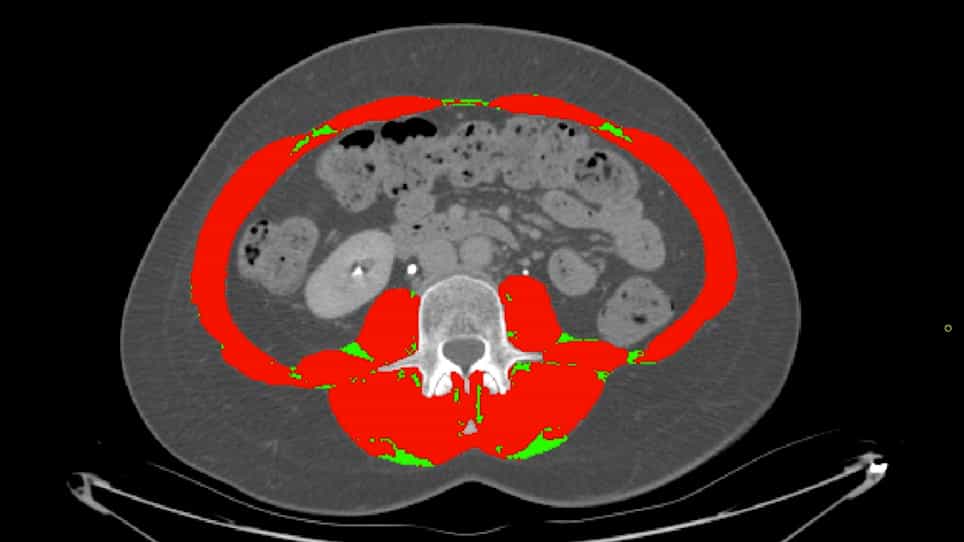

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Prevalence and longitudinal development of sarcopenic obesity in an Asian obese population: a large bioelectrical
Guo Hou Loo1, Farhana Raduan1, Zunaidah Abu Samah2
1Upper GI and Metabolic Surgery Unit, Department of Surgery, Faculty of Medicine, Universiti Kebangsaan Malaysia, Cheras, Malaysia.

Background:
Sarcopenic obesity (SO), the coexistence of excess adiposity and reduced relative muscle mass, has metabolic and functional implications. Data in Asian populations remain limited.
Objectives:
To determine SO prevalence using two diagnostic frameworks, identify predictors of SO while avoiding circular inference, and examine longitudinal reclassification in initially non-sarcopenic obese individuals.
Methods:
Retrospective cohort study of 2,410 adults with BMI ≥ 25 kg/m2 undergoing bioelectrical impedance analysis (BIA) at a Malaysian tertiary centre (2017-2025). SO was defined using AWGS 2019 skeletal muscle mass index (SMI) thresholds and an adapted ESPEN/EASO-based definition with sex-specific body fat percentage and population-derived lowest-quartile muscle-fat ratio (MFR) thresholds. Multivariable logistic regression, Kaplan-Meier and Cox proportional hazards analyses were applied to the longitudinal cohort.
Results:
SO prevalence was 0.12% (AWGS) and 25.02% (adapted ESPEN/EASO), with equivalent prevalence across sexes (females: 25.02%; males: 25.03%; p = 1.00). The SO group had significantly higher BMI, body fat percentage, and SMI. In multivariable analysis (MFR excluded to avoid circular inference), higher BMI (OR: 1.248; 95% CI: 1.204-1.304), male sex (OR: 1.757; 95% CI: 1.381-2.321), and older age (OR: 1.277; 95% CI: 1.136-1.435) were statistically associated with SO in this conditional model; these associations require cautious interpretation given conceptual overlap between BMI and the adiposity component of the definition. Of 742 initially non-sarcopenic individuals, 47 (6.3%) were reclassified during follow-up (6.5% at 6 months, 12.0% at 12 months); in Cox proportional hazards regression, baseline BMI was the only independent predictor of time to reclassification (HR: 1.098; 95% CI: 1.019-1.195).
Conclusion:
SO affects approximately one in four obese Malaysian adults under the present body composition-based criteria (sex-specific body fat percentage and population-derived lowest-quartile MFR thresholds); this estimate is contingent on the operational definition and is not an externally validated epidemiological prevalence. MFR and BMI are the most clinically informative metrics, but MFR must not be simultaneously used to define and predict SO. Longitudinal BIA monitoring is warranted in obese populations, as a measurable proportion is reclassified within 12 months.
Related Concept Videos
 01:24
Obesity
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution