Trauma Center Level and Mortality in Injured Patients with Shock or Multisystem Trauma
Related Experiment Video
Updated: Jun 20, 2026
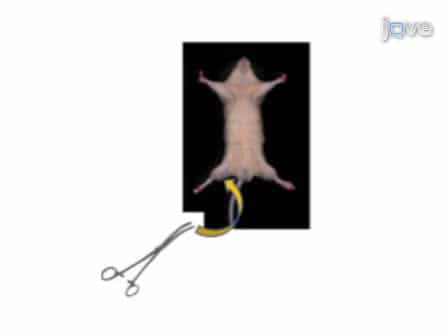
Pseudofracture: An Acute Peripheral Tissue Trauma Model
Published on: April 18, 2011
Christopher J McLaughlin1,2, Jamie Song1, Joseph A Kern1
1From the Division of Traumatology, Surgical Critical Care, and Emergency Surgery, Department of Surgery, Perelman School of Medicine, University of Pennsylvania, Philadelphia, PA (McLaughlin, Song, Kern, Seamon, Martin, Chreiman, Kim, Reilly, Kaufman).

Background:
Level I and Level II trauma centers share similar clinical verification standards, but differences in volume, subspecialty integration, and transfer patterns may affect outcomes for the highest-risk injured patients.
Study Design:
We performed a retrospective cohort study using the Pennsylvania Trauma Outcomes Study database from 1999 to 2023. Patients aged 16 years or older treated at established Level I or Level II trauma centers with an Injury Severity Score (ISS) higher than 9, transfer to a trauma center, or death at a trauma center were included. Patients treated at centers that changed level, Level III and IV centers, burns, age younger than 16 years, ISS less than 9, and transfers out were excluded from comparative outcome analyses. The primary endpoint was in-hospital mortality. Multivariable logistic regression adjusted for age, Glasgow Coma Scale, presenting vital signs, mechanism, Abbreviated Injury Score, ISS, transfer status, and comorbidities.
Results:
Among 363,470 patients, 247,800 (68.2%) were treated at Level I centers and 115,670 (31.8%) at Level II centers across 11 Level I and 16 Level II facilities. The proportion treated at Level II centers increased from 23.5% in 1999 to 45.2% in 2023. Level I centers treated younger, more severely injured patients and higher proportions transferred in, presenting in shock, or sustaining blunt multisystem or penetrating truncal injury. Overall mortality was 7.7%, with unadjusted mortality of 8.2% at Level I vs 6.9% at Level II centers. After adjustment, mortality did not differ overall. However, Level I centers had lower adjusted mortality among patients with blunt multisystem trauma and those presenting in shock; no adjusted mortality difference was observed for penetrating truncal injury, isolated traumatic brain injury, or ISS strata.
Conclusions:
In this mature statewide trauma system, Level I and Level II centers had similar adjusted overall mortality, but Level I centers demonstrated a survival advantage for shock and blunt multisystem trauma. These findings support targeted triage and early-transfer strategies for physiologically unstable and complex blunt-injury patients.
Related Concept Videos
 01:28
Traumatic Brain Injury l: Introduction
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:14
Spinal Cord Injury ll: Pathophysiology
 01:21
Cellular Injury II: Classification
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology