Related Experiment Video
Updated: Jun 21, 2026
Exploring Independent Effects of Follicle-Stimulating Hormone In Vivo in a Mouse Model
Published on: August 11, 2023
Antimüllerian hormone rebound and estradiol changes in the study of women's health across the nation
Laura M Bozzuto1, Kelly Acharya2, Bethelhem Shiferaw3
1Department of Obstetrics and Gynecology, University of Wisconsin School of Medicine and Public Health, Madison, Wisconsin; Department of Surgery, University of Colorado Anschutz Medical Campus, Aurora, Colorado.

Objective:
To characterize the prevalence of redetectable antimüllerian hormone (AMH) over the menopause transition and correlation with other ovarian hormones indicating rebound in ovarian function.
Design:
Multisite prospective observational cohort study.
Subjects:
Participants in the Study of Women's Health Across the Nation (SWAN) with an observed final menstrual period (FMP) and three or more AMH measurements with at least one AMH measurement below the lower limit of detection.
Exposure:
Age at FMP, oligomenorrhea, body mass index, and time to FMP from AMH limit of detection.
Main Outcome Measures:
The main outcome measures were AMH levels after becoming undetectable and estradiol (E2) change after undetectable AMH utilizing ultrasensitive assay. Secondary outcomes were follicle-stimulating hormone (FSH) and inhibin B hormone levels after the AMH limit of detection.
Results:
Of 1,558 participants with AMH data, 406 met the inclusion criteria. Of these, 220 (54.2%) had a subsequently detectable AMH after reaching the lower limit. Of women with AMH rebound, 107 (48.6%) also had a concurrent rise in E2. The AMH rebound was associated with younger age at the detectable limit of AMH (AMH+E2 48.5 years [SD 2.7], AMH only 49.9 [2.6], no rebound 51.7 [2.6]) lower body mass index (BMI) (AMH+E2 24.5 kg/m2 [interquartile range, IQR 21.6-30.9], AMH only 25.0 [22.4-31.8], no rebound 27.5 [IQR 23.5-34.6]), and a lower FSH at the AMH limit of detection (AMH+E2 28.6 mIU/mL [IQR 15.3-57.8], AMH only 29.8 [12.9-64.2], no rebound 62.5 [38.3-95.1]). There was no difference in the age at FMP (AMH+E2 52.2 years [SD 2.5], AMH only 52.3 [2.4], no rebound 52.8 [2.6]).
Conclusion:
Almost half of the women in the SWAN AMH study demonstrated AMH rebound; in half of these cases, AMH rebound was followed by a rise in E2, implying that AMH rebound is reflective of recrudescence of ovarian activity. Younger age at reaching undetectable AMH, lower BMI, and lower FSH levels were associated with this finding. Clinicians should be aware that transient AMH and ovarian hormone levels may vary after becoming undetectable, with implications for perimenopausal staging.


Related Concept Videos
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:28
Menopause
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 02:07
Oogenesis
 01:22
Target Cell Response to Hormones
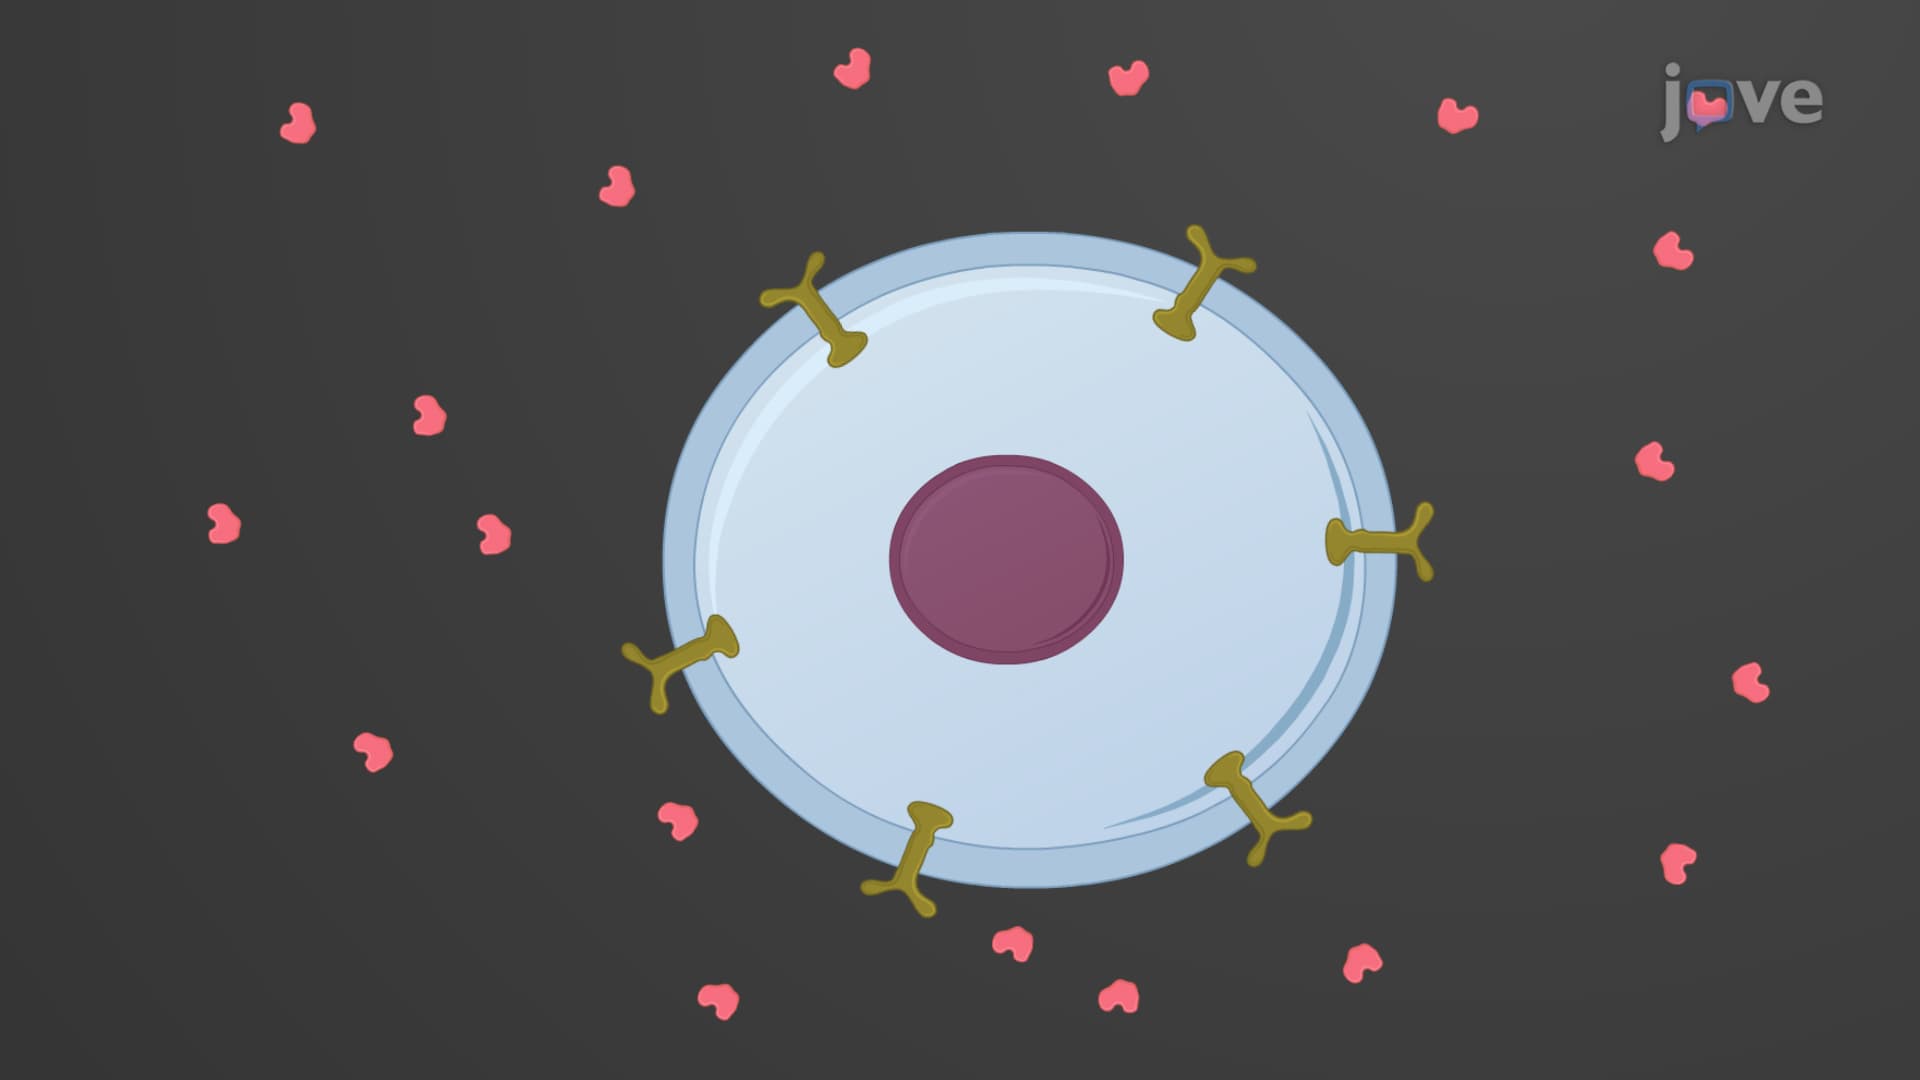
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...