Related Experiment Video
Updated: Jun 21, 2026
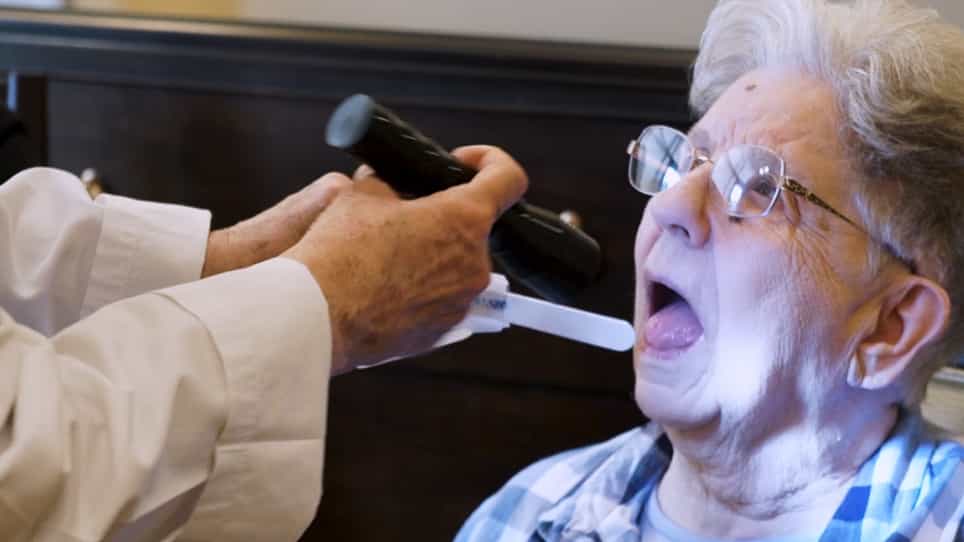
Oral Health Assessment by Lay Personnel for Older Adults
Published on: February 2, 2020
Understanding how to promote oral care 'mouth minutes' in care homes: qualitative study with utilisation of the COM-B
Karen Vinall-Collier1, Julia Csikar2, Kirsty Haunch3,4
1School of Dentistry, University of Leeds, Leeds, UK. K.A.Vinall@leeds.ac.uk.

Background:
Older adults are vulnerable to poor oral health due to physiological and cognitive changes, multiple medications, and dependence on carers. Despite national guidance, oral care in UK care homes remains inconsistent, and many staff report lacking the personal skills, organisational support, and confidence to deliver consistent oral care despite highlighting their commitment to deliver effective "mouth minutes" as part of daily routines. This study aims to examine care home and dental stakeholders' views on supporting residents' oral health, using the COM-B model to identify factors shaping staff oral-health-related behaviours.
Methods:
Focus groups were undertaken between June 2022 and November 2022 with the following 4 stakeholder groups to explore perspectives of supporting oral health maintenance in care home residents: (1) residents and relatives, (2) care home frontline workers, (3) care home managers and (4) external oral healthcare professionals (Oral HCPs) with care home experience. Framework analysis was undertaken at a semantic level and then matrices were mapped onto the COM-B model.
Results:
Fifty participants from three care homes (residential and nursing homes), and external oral HCPs in Great Britain took part: 11 residents, 6 relatives, 25 care home staff (managers and frontline workers) and 8 external oral HCPs. Mapped against the COM-B framework; Opportunity, particularly Physical Environment, Context, and Resources, was the most frequently coded construct. There was also alignment with Capability, especially Behavioural Regulation and Skills, and within Motivation, beliefs about Consequences and Capabilities.
Conclusions:
Access to external oral healthcare professionals, tailored training, and organisational support were pivotal to improving oral health in care homes. The study confirms that micro‑level interventions are insufficient, as structural barriers-including limited dental access, workload pressures, and inconsistent resources-continue to undermine practice. Care home staff emphasised condition‑specific training and structured communication; relatives sought guidance to support loved ones; and external oral HCPs highlighted working and recognition of oral health as part of wellbeing. Aligning intervention design with the COM‑B framework provides a pathway to address structural, motivational, and capability barriers as interacting influences on oral care behaviour in care homes. This study explains why existing interventions fail by illustrating how Capability, Opportunity, and Motivation intersect, advancing COM‑B from a categorisation tool to an implementation‑focused framework.
Related Concept Videos
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities
 01:26
Assessment of the Mouth
Mouth Inspection
The inspection begins with visually examining the mouth for symmetry, color, and size.
 01:19
Restorative Care
 01:24
Nursing Process for Patient and Caregiver Teaching II: Planning and Implementation
 01:25
Role of Communication in the Nursing Process II: Planning and Implementation
 01:21
Interdisciplinary Care: The Health Care Team-I
Physicians
The physician's primary responsibility is to diagnose illness and direct the medical or surgical treatment of the condition. The authority to admit patients to a healthcare agency or institution and practice care within that setting is granted to physicians by the healthcare agency or institution itself.